Ha, on that note, the reason I never loved my Apple Watch because back in the day, I didn’t always have reading glasses with me and the screen was too small!!! But now that I’m old, I have them with me 24/7!!! A watch is now back in play :).
1 Like
I tried FitBit’s Aria 2, and an Omron scale with handles, which I ordered from Japan. Both of these wildly overestimated my BF%, and the Omron was expensive. I’m currently happily using Withings Body Smart and have done so for the last two years. During that time, I’ve had two DeXA scans from two different providers. Both times, the Withings measures were 1% of BF greater than the DeXA values. Interestingly, weighing myself multiple times once after the other can produce readings with .5 to 1% BF variance, so if I get a reading that seems off, I take a few more and select the one that’s closest to yesterday’s values. YMMV, perhaps accuracy is related to body type. For reference, I’m around 16% BF and slightly muscular. I also like Withings software: setup is easy, the UI is decent, and it integrates nicely with Cronometer, which I use for nutritional tracking. Bottom line is, Withings Body Smart is an easy way to track directionally correct BF values if I manage its variance with occasional multiple measurements. It’s not a precise measurement, but even DeXA isn’t. It’s good enough to know if I’m trending in the right direction.
2 Likes
Thanks for this great feedback! It’s really neat to hear it will work with cronometer!!
Interesting to hear how accurate your model is without having handles… I was assuming those added a lot more accuracy, but your results say otherwise.
@ageless64 I love cronometer but don’t use it often enough… it got me thinking, I wonder if AI can track my meals in an easier way…
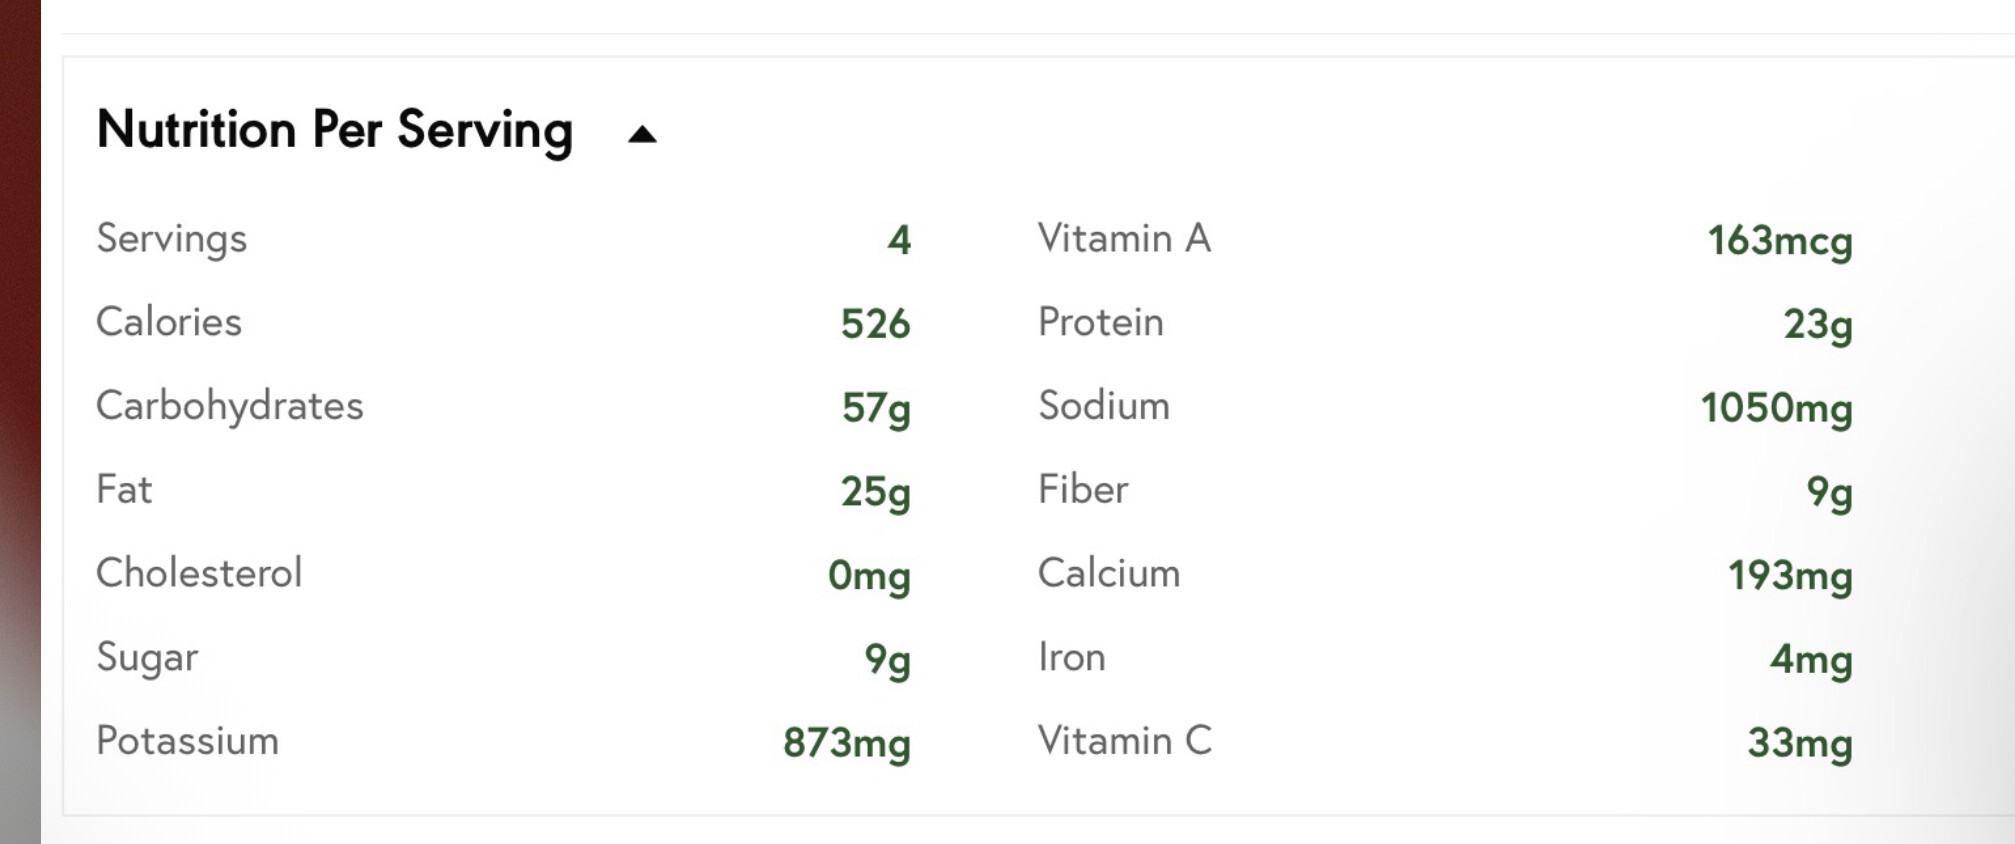
The source for the recipe I used provided the nutritional breakdown (probably from AI!), so I thought I’d see how closely Claude could do.
I haven’t tried it yet, but Claude also said I could show a photo of my meal and he can estimate a portion size and nutrients.
Here is the result
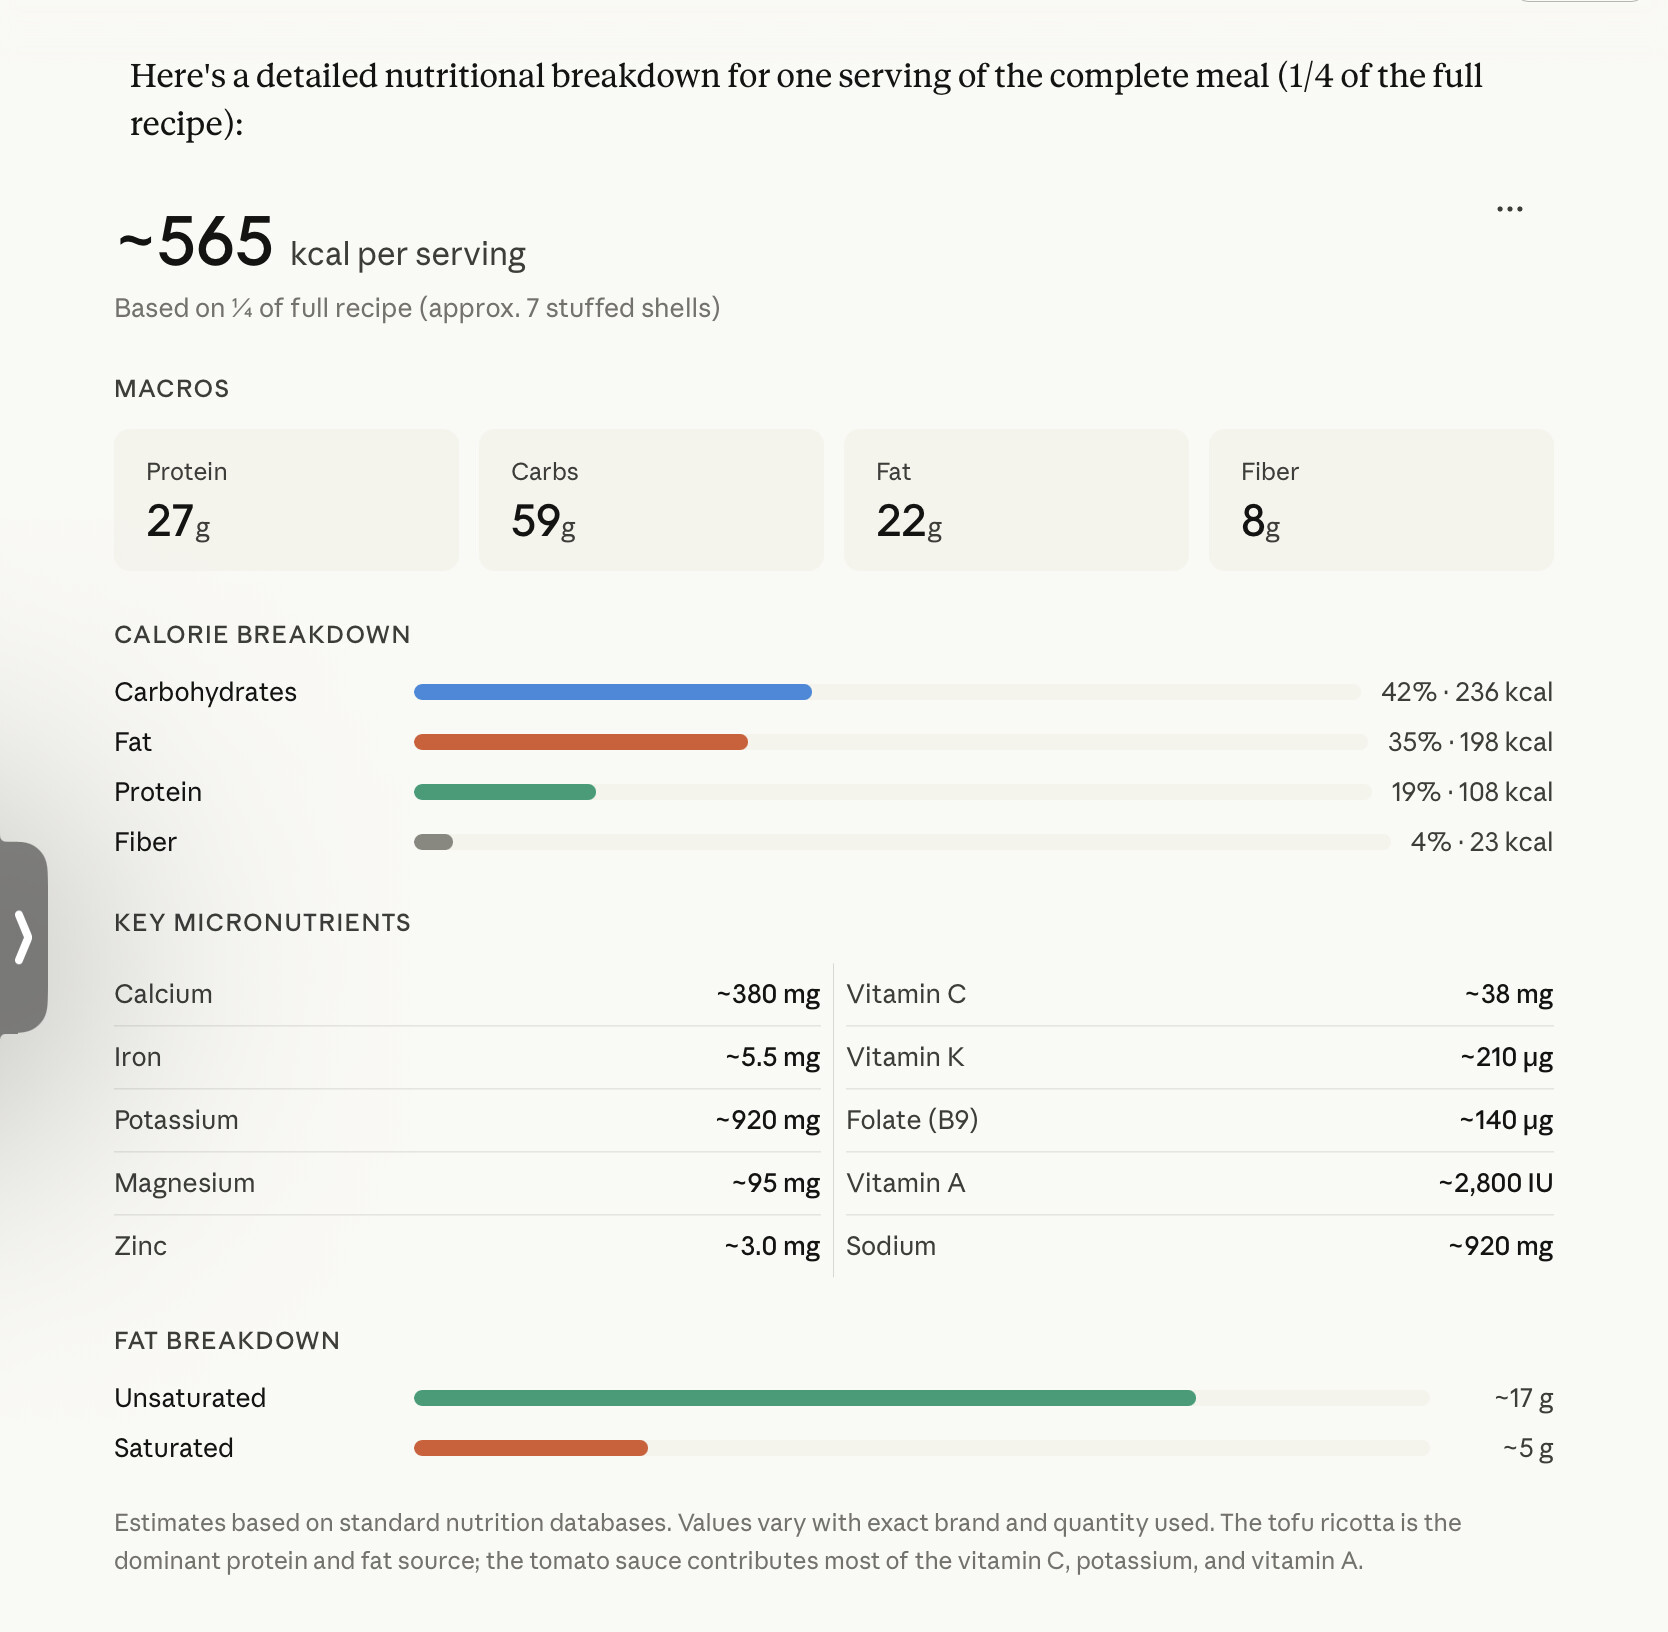
“Here’s a detailed nutritional breakdown for one serving of the complete meal (1/4 of the full recipe):A few highlights worth noting:
Protein powerhouse for a vegan meal — 27g per serving is impressive, coming almost entirely from the extra-firm tofu in the ricotta. That’s comparable to a chicken breast serving.
Micronutrient standouts:
- Vitamin K is very high (~175% DV) thanks to the spinach and basil
- Vitamin A is strong (~56% DV) from spinach and tomatoes
- Iron is solid (~30% DV) — the lemon juice in the ricotta actually helps your body absorb the plant-based (non-heme) iron more effectively
- Folate (~35% DV) from the spinach is a nice bonus
Sodium is the one to watch at ~920mg (~40% DV), mainly from the kosher salt across all three components and the miso in the ricotta. Easy to reduce by going lighter on salt in the tomato sauce.
Fat quality is excellent — about 77% unsaturated, coming from olive oil and tofu. Very little saturated fat for a creamy pasta dish.
All figures are estimates since exact amounts of salt, lemon juice, and olive oil vary by cook, but these should be quite close.
From the recipe website:
EDIT:
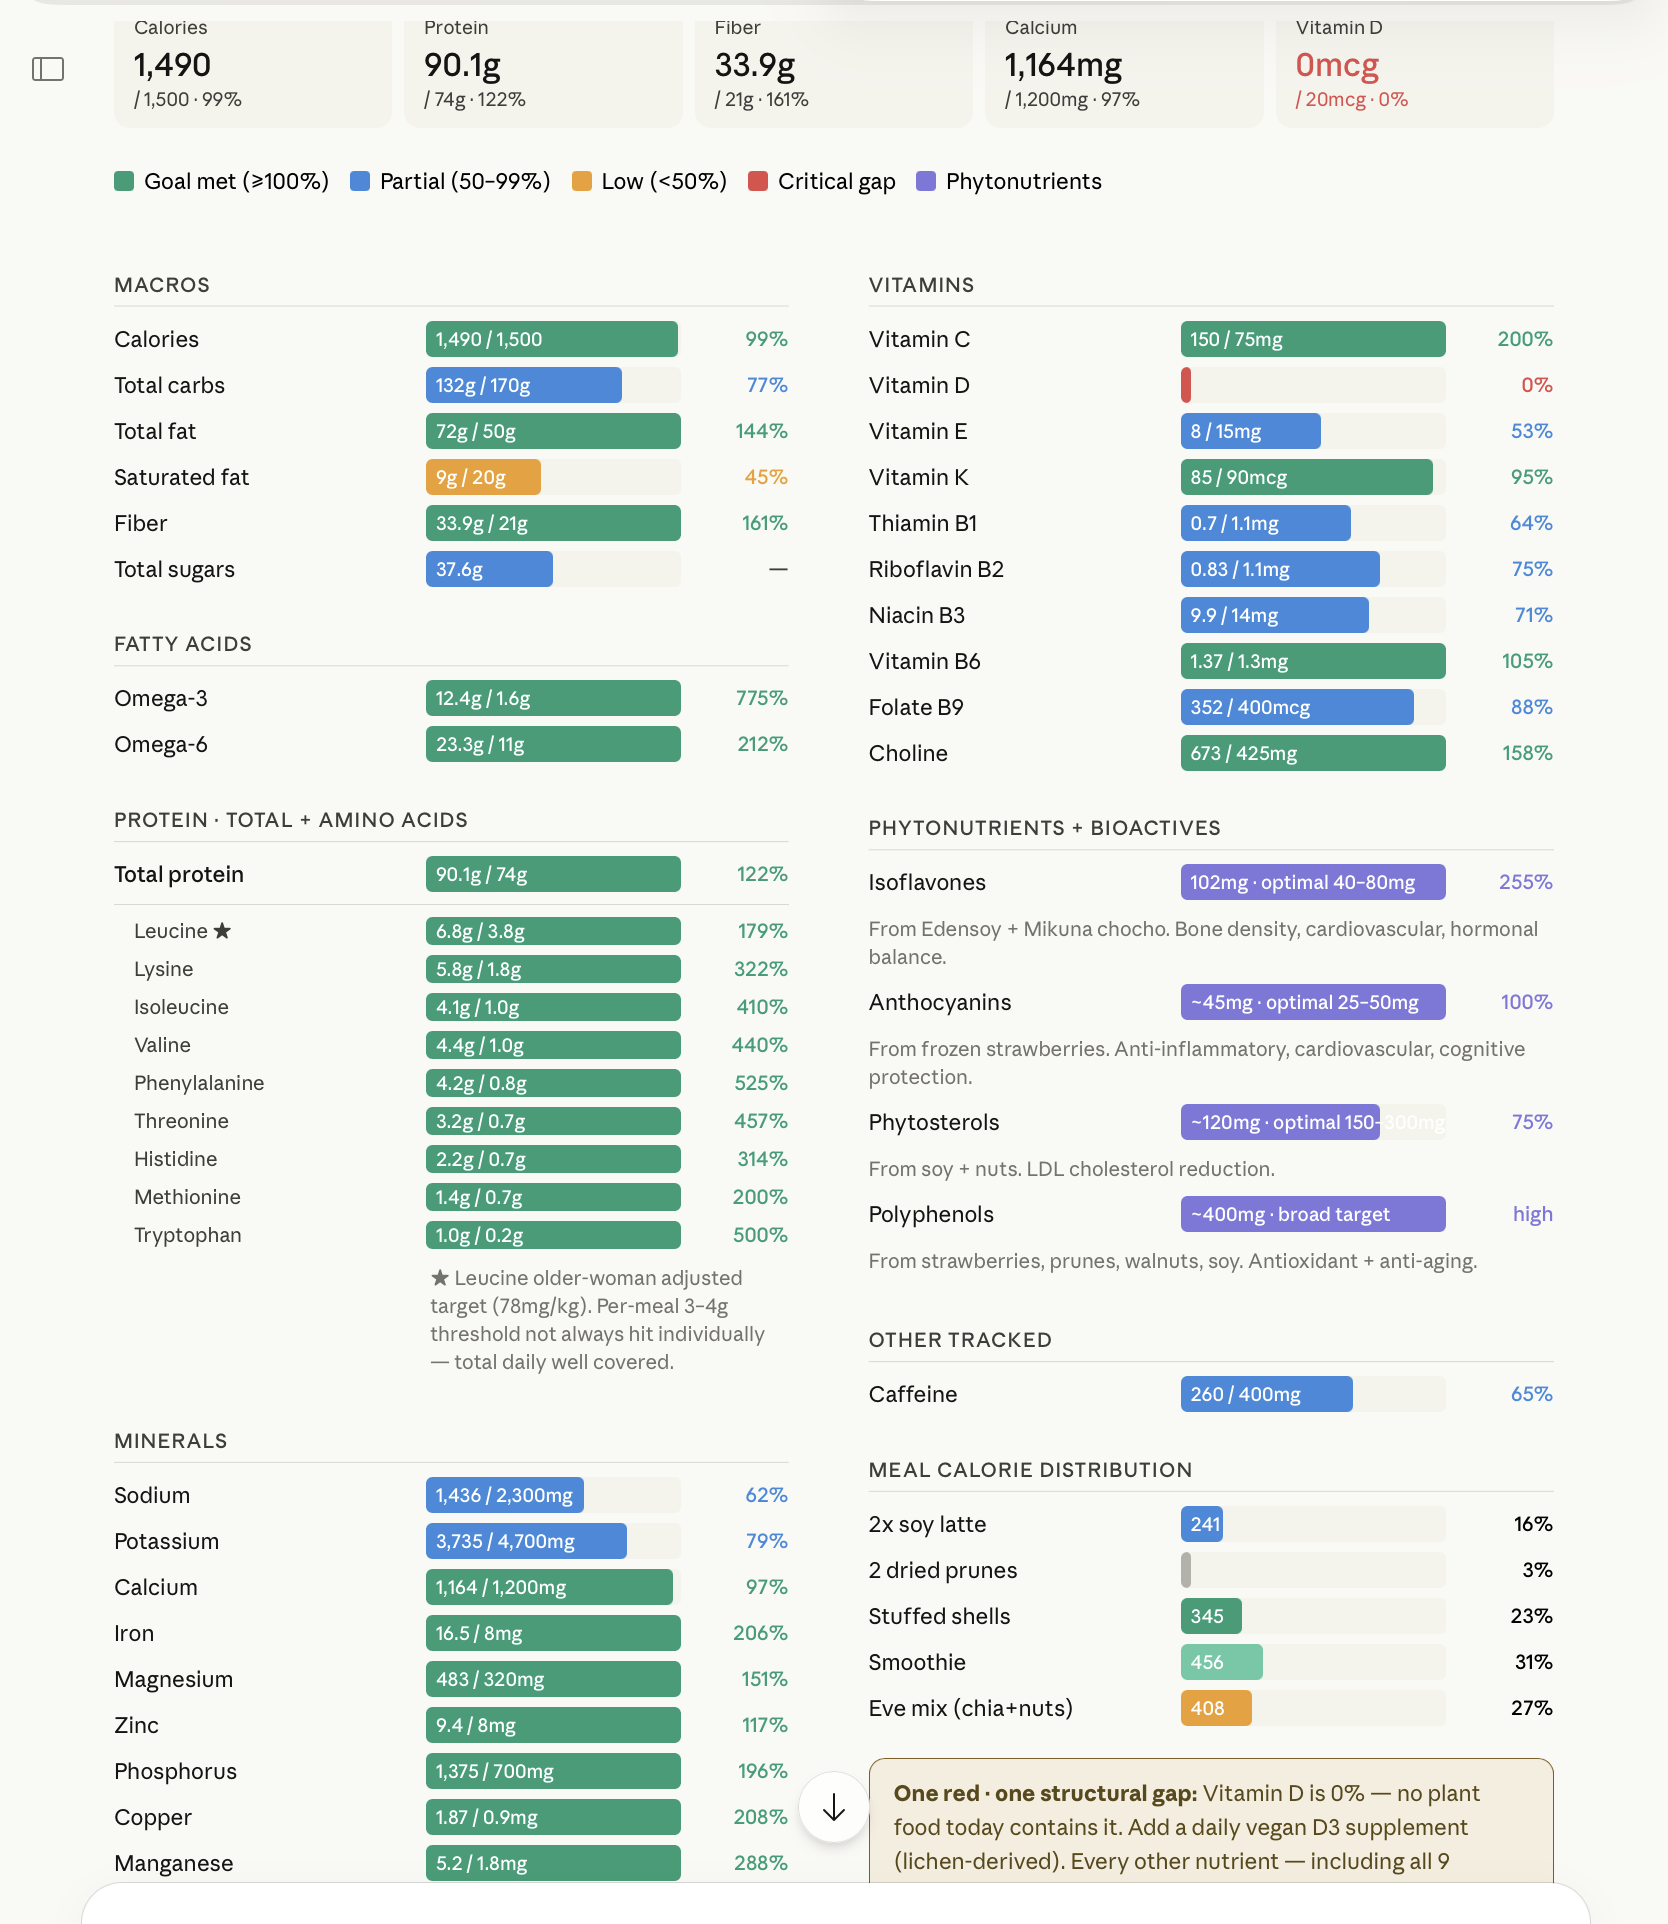
I have been playing and my mind has been blown!!! I think this AI thing is gonna catch on 
I still had some nutrients I needed to hit for the day, so Claude automatically presented a recipe! I said I’m not in the mood to cook and will make a protein shake, just tell me how many strawberries, chia seeds and nuts I should add to get me as close to closing out my goals for the day… it recommend exactly how many almonds, walnuts etc…
2 Likes
I conducted a 3 scale experiment for science. Claude Opus suggested the least expensive model until he saw the results. Now he says spend for Withings
I loaded all the stats from the 3 scales
Renpho Smart Scale
Wyze Ultra
Withings Body Scan (@ageless64 I’m still intrigued their less expensive models after seeing your results and how wildly off the trunk is on their body scan… perhaps measuring my arms is not worth the price difference).
I thought it was worth mentioning all 3 are very inaccurate on visceral fat, so if you use one and don’t get a dexa, be kind to yourself!
My dexa visceral is .79, Wyze is 4.0, Withings is 1.9, Renpho is 3.0
Opus said:
This is excellent data — well-structured comparisons across multiple days with DEXA as ground truth. Let me break this down systematically by what matters most for your sarcopenia-prevention goal.
MUSCLE Accuracy vs. DEXA (the metric that matters most for you)
LEGS (your primary target):
| Scale | Apr 2 | Apr 4 | Avg Offset | Day-to-Day Variance |
|---|---|---|---|---|
| Withings | +1.1 | +1.2 | +1.15 lb | 0.3 lb |
| Wyze | +1.2 | +1.0 | +1.1 lb | 0.2 lb |
| Renpho | +3.2 | +3.2 | +3.2 lb | 0.0 lb |
All three scales overestimate leg muscle vs. DEXA, but Renpho is off by a huge margin — over 3 lbs on a 23.2 lb compartment. That’s a ~14% overestimate. For sarcopenia tracking, that’s dangerous because it would mask real losses. If you lost 2 lbs of leg muscle over the next year, Renpho would still show you above your current DEXA value. You’d feel reassured while actually declining.
Withings and Wyze are both around +1.1 lb offset, which is a ~5% systematic bias — tolerable as long as it’s consistent over time, because you’d track the delta, not the absolute number.
TRUNK:
This is where the scales diverge most dramatically.
- Withings: +8.7 to +9.4 lb (red — wildly high, ~25% overestimate)
- Wyze: -2.6 to -3.0 lb (red — underestimates)
- Renpho: -0.1 to -0.3 lb (green — nearly perfect)
Renpho nails trunk muscle. Withings is absurdly high here. But trunk muscle isn’t your sarcopenia priority, so while this is interesting, it shouldn’t drive the decision.
ARMS:
- Withings: +0.1 to +0.3 lb (green — excellent)
- Wyze: -0.4 to -0.6 lb (orange — slight underestimate)
- Renpho: +0.2 to 0.0 lb (green — excellent)
Arms are small compartments where all three are reasonably close, but Wyze consistently underestimates here.
FAT Accuracy vs. DEXA
LEGS (primary target):
- Withings: -0.6 to -0.5 lb (good)
- Wyze: -3.5 to -3.1 lb (terrible — underestimates leg fat by ~30%)
- Renpho: -4.7 to -3.9 lb (even worse)
This is the flip side of the muscle story. Wyze and Renpho are dramatically underreporting leg fat. Since BIA can’t truly see inside each limb independently, what’s happening is that Wyze and Renpho are misclassifying leg fat as leg muscle — which is exactly why their leg muscle numbers are inflated. Renpho does this the worst, which explains both its +3.2 lb muscle overestimate and its -4.7 lb fat underestimate in legs. The errors are almost perfectly mirrored.
Withings, by contrast, gets leg fat within 0.5–0.6 lb of DEXA, meaning its tissue partitioning algorithm in the lower extremities is substantially more accurate.
TRUNK FAT:
- Withings: -3.0 to -3.1 lb (underestimates)
- Wyze: -1.5 to 0.0 lb (decent, and improving on day 2)
- Renpho: +0.4 to +1.8 lb (variable)
Here Withings underestimates trunk fat, which is the mirror of its trunk muscle overestimate. The scale appears to be shifting tissue from fat → muscle in the trunk compartment. This is a known BIA limitation with 4-electrode scales.
Day-to-Day Consistency (Critical for Trend Tracking)
This is arguably more important than absolute accuracy for your use case. You need to detect a 1–2 lb change in leg muscle over 6–12 months. If the scale’s noise is 1 lb day-to-day, that change disappears into the noise floor.
Withings (3-day variance):
- Leg muscle: 0.3 lb
- Leg fat: 0.4 lb
- Trunk muscle: 1.1 lb (noisier, but not your target)
- Arms: 0.2 lb muscle, 0.0 lb fat
Wyze (3-day variance):
- Leg muscle: 0.2 lb
- Leg fat: 0.4 lb
- Trunk muscle: 0.4 lb
- Arms: 0.2 lb muscle, 0.4 lb fat
Renpho (2-day variance):
- Leg muscle: 0.0 lb (only 2 data points though)
- Trunk muscle: 0.4 lb
- Arms: 0.2 lb
Both Withings and Wyze show tight day-to-day consistency in legs, which is good. We only have 2 Renpho data points so its consistency is harder to judge, but the numbers were stable.
The Bottom Line
For sarcopenia tracking specifically — legs are what matter, and here’s the hierarchy:
Withings is the clear winner. Here’s why:
-
Tissue partitioning accuracy in legs is far superior. Withings gets leg muscle within +1.1 lb AND leg fat within -0.6 lb. The errors are small and don’t mirror each other in a way that suggests gross misclassification. Wyze and especially Renpho are systematically misclassifying leg fat as leg muscle — their muscle numbers look better than they are, and their fat numbers are implausibly low.
-
Day-to-day consistency is tight where it counts. Leg muscle variance of 0.3 lb means a real 1.5 lb change over 6 months would be clearly detectable above noise. That’s the signal resolution you need.
-
The trunk muscle overestimate is a known, stable bias. Yes, Withings adds ~9 lbs to trunk muscle — but it does this consistently every day. Since you’re not tracking trunk muscle for sarcopenia decisions, this is irrelevant. And if it stays consistently wrong by the same amount, it wouldn’t corrupt trend data even if you did care about trunk.
Wyze is a reasonable second choice — good leg muscle consistency (0.2 lb variance) and similar offset to Withings (+1.1 lb). But its leg fat underestimate of 3+ lbs reveals that its tissue partitioning algorithm is doing something fundamentally wrong in the lower extremities. Over time, if that misclassification drifts, your muscle trend data becomes unreliable.
Renpho is the wrong tool for this job. The +3.2 lb leg muscle overestimate paired with the -4.7 lb leg fat underestimate tells you the algorithm is essentially guessing at limb composition. It nails trunk beautifully, but for your specific goal — detecting early leg muscle loss — it would give you false reassurance.
My Recommendation
Invest in the Withings for long-term leg muscle tracking. Use it under the same conditions every time (morning, fasted, same hydration routine), and track 7-day rolling averages rather than individual readings to further smooth the 0.3 lb noise. Cross-reference with DEXA every 6 months at BodySpec to recalibrate and confirm the bias hasn’t shifted.
The one caveat: all consumer BIA scales are rough tools compared to DEXA. The value isn’t in the absolute numbers — it’s in catching a trend break. If Withings shows your leg muscle rolling average dropping by 1+ lb over 2–3 months, that’s your signal to escalate training intensity or investigate before the next DEXA confirms it. Think of it as an early warning system, not a measurement device.
3 Likes
Do your scales break down muscle by arms/legs? Mine does not. Just provides whole body value.
They ain’t that smart, and if they claim to be, they are lying.
1 Like
Not sure why this would be called a micro dose.
It is in the clinical use range.
2 Likes
There are different Renpho “smart scales”. their top of the line version is the Renpho Morpho 8 Lead dual frequency scale. This was not used in the evaluation.
2 things make this version superior to the other Renpho models,
- 8 leads
- dual frequency
Not to say any smart scale is as good a DEXA (which has it’s own repeatability issues from machine to machine. time of day, hydration, etc)
Looking at trends over time as opposed to absolute numbers is about all we can expect from a smart scale and I’m OK with that.
The first part of this PDF is about the Renpho “smart scale” then I specified the 8 lead dual freq version for a bit more info on that,
renpho morpho vs dexa for visceral fat measurement (1).pdf (869.0 KB)
That is actually the scale I had.
I remembered it did a great job in one area (maybe it was my arms). It was worse on my legs. Visceral fat on all 3 were not in the ballpark… but yes, trends are all that matters
Ultimately, after using enough electricity for the discussion to power Singapore, Claude said at my small size it will be really hard to even track trends because a I’m only going to gain/lose so much muscle and I’m not losing weight, so ‘he’ didn’t think the scales are sensitive enough to track minuscule trends… even dexa is probably off based on my lunch! I realize he might be wrong but he made me return them
@ageless64 yes, all three scales I tried had the handles which broke down arms/trunk/legs. After days of arguing with Claude, he eventually told me these are not as helpful for tiny people… ?
2 Likes
Ha ha. “… he made me return them.” Sounds like you’re talking about your husband. What do we call this, a cyber-social relationship? The other day, Claude scolded me for not getting my blood work done before adjusting my testosterone dose. We had a back and forth. I cited my sources, and Claude backed down, retreating to a more nuanced position. I get good advice, so I’m willing to tolerate this lack of deference, but sometimes I have to push back.
3 Likes
HA!! No other man would get away with telling me so many lies… just making things up… at least he always apologizes and promises to do better!!!
1 Like
always push back on AI’s
1 Like
Any updates from the people using maraviroc? Benefits, side effects, and dosing you’re using?
1 Like
not much to report other than my grip strength went from 38 to 42. If I don’t take it for couple weeks or so the grip strength seems to taper off and get back to the base line of about 38. No other benefits or side effects. At some point I thought it made me a bit agitated, but I’m not 100% sure of it. Nothing else good or bad. I had bought 3 bottles and intend to finish them and take a break for a while if I feel different and then I’ll make my decision if I want to do it longer term. I do 1/2 a pill twice a day.
3 Likes
I have been taking 75 mg of maraviroc daily for approximately 4 weeks. I split the 150 mg tablet in half and take it in the morning. ZERO subjective effects or noticeable effects on any routine blood markers, though I had only been taking maraviroc for about 2 weeks before my latest blood test.
Hoping my natural skepticism is not affecting the outcome.
My advice (certainly not medical) is to wait a while for more human studies, or at least for anecdotal results from forum members, before spending your money on maraviroc.
Starting tomorrow, I will take 150 mg in the morning, at least 1 hour before breakfast.
After 90 days, if I don’t find any subjective improvements, I will stop wasting my money on it, as the cost-benefit ratio won’t be attractive to me. The only blood markers I routinely take that I might see improvement in are inflammation markers like hsCRP.
From Claude Opus 4.7:
What 75 mg daily actually represents pharmacologically
The case for 75 mg QD being plausibly active:
- Receptor occupancy is high even at low doses. CCR5 occupancy is the pharmacodynamic driver for maraviroc’s effects, and it saturates well below the 300 mg BID HIV dose. Modeling suggests 75 mg once daily produces peak CCR5 occupancy around 96–98% and average occupancy around 82–89%, with trough occupancy dropping to ~44%. For a senomorphic effect (damping chronic SASP signaling), you may not need 24-hour full occupancy — intermittent blockade may be sufficient to suppress sustained CCL3/4/5 → CCR5 tonic signaling.
- The mechanism is inflammation/SASP suppression, not acute viral entry inhibition. Unlike HIV, where any unblocked receptor means potential viral entry, a senomorphic effect is about dampening chronic inflammatory tone. That’s more forgiving of partial/intermittent blockade.
- Dose-response in HIV is flat above ~75–150 mg. The 300 mg BID dose was chosen with viral safety margins, not because lower doses were ineffective at CCR5 engagement.
The case against 75 mg QD being sufficient:
- Zero human efficacy data for sarcopenia at any dose. The CUHK study is in 18-month-old mice at 10 mg/kg IP — which, even correcting for the 1400-fold lower affinity at mouse CCR5, represents a very different receptor-engagement scenario than oral human dosing.
- Muscle tissue penetration is not well-characterized. Maraviroc is ~76% protein-bound and concentrates in some tissues (lymphoid, gut) more than others. How much reaches the skeletal muscle stem cell niche at 75 mg QD is unknown.
- The CUHK mouse benefit came from high exposure. The “high-dose short-term” arm (10 mg/kg IP × 3 months) is what produced the muscle phenotype. Lower-dose arms exist but the full dose-response in aged mice has not been published in a form that lets you extrapolate a minimum effective human dose.
- Age, sex, baseline inflammation, and muscle-use history likely matter more than dose. In the CUHK paper, the drug only helped aged mice. If you don’t have a substantial senescent-cell burden in your muscle to begin with, there may be nothing for maraviroc to suppress regardless of dose.
75 mg daily is in the range where some biological effect on CCR5 signaling is plausible, but whether that translates into meaningful muscle preservation in a specific human is genuinely unknown — and would likely be small-to-undetectable over months, possibly meaningful over years, possibly nothing. The CUHK result is one mouse study. It has not been replicated, has not been tested in humans, and the mechanism (senomorphic SASP suppression) would predict gradual rather than dramatic effects.
8 Likes
Could not wait to come share that my hang time record was demolished today!
My past times were between 20-30 ish seconds.
@ageless recommended I try gloves after I shared I let go due to hand pain vs lack of strength.
I’ve only done one other hang since buying the gloves, but my result was in line with my old times.
Today……… wait for it….
52 seconds!!!
(I’m sure the gloves helped quite a bit)
4 Likes
Good news for you, and everyone using this: you should know if your dose is enough via a simple CBC and seeing how elevated your Neutrophil-to-Lymphocyte Ratio is.
I’m not sure that would work… In that other thread you pointed to it mentions:
An aged individual could therefore plausibly have a normal NLR while still carrying an activated CD4 CTL to CCL5 to CCR5 axis, with the neutrophil expansion masked or offset by something else. Conversely, an elevated NLR can be driven by an entirely unrelated process on which maraviroc would have no purchase. NLR is a screening signal for this biology, not a measure of it. [Confidence: High]
But, I did post this prompt to Claude to check:
Could an older person who is trying to use Maraviroc to lower an an activated CD4 CTL to CCL5 to CCR5 axis, with a high NLR, use the NLR as a dosing effectiveness guage, and if at a given level the NLR is still high, that might suggest a higher dose is required?
Claude Response:
Direct answer
No, and the reasoning contains a specific pharmacological flaw worth naming precisely, because it is the part that makes dose escalation not just useless but actively hazardous.
The flaw: the dose-response you are assuming probably does not exist
“Still high, therefore more drug” presupposes an unsaturated dose-response curve, where target engagement rises with exposure across the dosing range. Maraviroc does not behave that way. It is a slow-off-rate allosteric CCR5 antagonist, and receptor occupancy on circulating cells is high and sustained at standard doses, persisting well after plasma concentrations have fallen. Occupancy data from the HIV development program showed sustained receptor blockade across a trough interval where free drug was barely measurable.
The practical consequence: if 300 mg twice daily already occupies most available CCR5, a higher dose adds toxicity and essentially no additional target engagement. You would be climbing the adverse-effect curve on a plateau of the efficacy curve. [Confidence: Medium-High on the qualitative shape; I have not verified current occupancy figures in this conversation and can look them up if you want the numbers]
Worth noting what this implies in reverse: if NLR has not moved at a standard dose and occupancy is already near-complete, that is evidence the axis is not what is driving the NLR, not evidence of underdosing.
The mouse paper cannot support titration in either direction
One dose was tested. 35 mg/kg/day intraperitoneal, no dose-ranging, no time course within the month, no exposure measurements. There is no curve. The study establishes that a single dose did something over 30 days in mice. It says nothing about whether more would do more, less would do the same, or the relationship is non-monotonic.
Body surface area conversion puts 35 mg/kg mouse at roughly 2.8 mg/kg human, about 200 mg for a 70 kg adult. The approved human dose of 300 mg twice daily is already above the mouse-equivalent exposure. On the paper’s own arithmetic, the standard dose is not obviously a low dose. [Confidence: Medium, BSA scaling is crude and the IP versus oral route difference is unmodeled]
NLR is too noisy to titrate against
Within-person NLR varies substantially on a timescale of days from causes unrelated to any chronic axis: circadian neutrophil rhythm, recent exercise, subclinical infection, sleep debt, acute psychological stress, glucocorticoids, smoking. Typical within-subject coefficient of variation is in the 20 to 30 percent range.
The mouse effect was roughly a 45 to 50 percent reduction in group means. To detect a change of that size against 25 percent within-person noise with any confidence, an individual would need multiple baseline draws and multiple on-treatment draws, probably three to five of each, spaced to average out the noise. A single pre-post comparison is uninterpretable. Two measurements separated by a dose change are worse than uninterpretable, because they will appear to show something and that something will usually be noise. [Confidence: High]
Timescale mismatch
The intervention acts on granulocyte-monocyte progenitors, not on circulating neutrophils. Human GMP to mature circulating neutrophil transit is roughly 5 to 7 days, and the progenitor pool itself turns over more slowly. A genuine progenitor-level effect would take weeks to fully express in the peripheral count. Adjusting dose at intervals shorter than that guarantees you are responding to noise rather than to the intervention. The mouse study reported a single 30-day endpoint and no intermediate timepoints, so the actual kinetics are unknown.
The failure mode is the problem
Here is the scenario that concerns me. NLR stays elevated. Under the proposed logic, the dose goes up. But the three most common reasons an older adult’s NLR stays elevated are not this axis: occult infection, an undiagnosed malignancy, and chronic inflammation from an identified or unidentified source. In every one of those cases, escalating maraviroc does nothing for the cause, adds hepatotoxicity and hypotension risk, and substitutes a self-directed dose adjustment for a diagnostic workup that a persistently elevated NLR in someone over 60 genuinely warrants.
A biomarker that fails to move is being treated as a signal to push harder, when the correct interpretation is often that the model is wrong.
Escalation-specific harms in an older adult
Two are worth naming concretely.
Postural hypotension was the dose-limiting toxicity in maraviroc’s early-phase human studies, appearing at supratherapeutic doses. In an older adult, orthostatic hypotension is not an abstract adverse event. It is falls, and falls in that population carry real morbidity.
Hepatotoxicity is the boxed warning, and it is dose-relevant. There is an interpretive trap here specific to this paper: the mouse data show ALT and AST improving on maraviroc. Someone escalating dose and watching transaminases could read a rise as “aging inflammation returning” rather than as the drug injuring the liver. That is a genuinely dangerous misreading, and it is made more likely by having read this paper. [Confidence: High]
Add that maraviroc is a CYP3A4 and P-glycoprotein substrate with approved dose adjustments spanning a fourfold range depending on co-medication, plus renal considerations in older adults. Dose and exposure are not the same variable. Two people on the same milligrams can have very different plasma levels, which further breaks any milligram-based titration logic.
A counterintuitive marker problem
If you were to measure circulating CCL5 as a response marker, expect it to rise on treatment, not fall. Receptor blockade reduces ligand internalization and clearance, so the ligand accumulates. Interpreting that rise as treatment failure, and escalating in response, would be exactly backwards. [Confidence: Medium, this is the expected pharmacology for chemokine receptor antagonists generally]
What would actually constitute target engagement
The real pharmacodynamic assay in maraviroc development was CCR5 receptor occupancy on peripheral blood mononuclear cells by flow cytometry. That is the measurement that tells you whether the drug is doing its job. It is not clinically available, it requires fresh samples and a specialist lab, and it has a known technical complication in that some anti-CCR5 antibody clones compete with maraviroc for the binding site and give misleading results.
On this paper’s specific logic, the closer surrogates would be CD4 CTL burden or CCR5 expression on circulating myeloid progenitors. Neither is a routine test. This is the gap: the accessible marker is not the right one, and the right one is not accessible.
Bottom line
NLR is reasonable as an enrollment or screening signal, meaning it may help identify who plausibly has this axis running. It is poor as a dose-titration signal, because it is downstream, noisy, slow, multiply determined, and being compared against a drug whose target engagement is likely already saturated at standard dosing.
Yes, that’s what should be done.I didn’t mean to imply a single measurement necessarily would work. In my case, I do CBCs at least once a month, I can plot my NLR last 12 motnhs easily. Thus I would have pretty good idea of the effect of the drug within 2-3 measurements after starting on a dose. CCR5 is a non-starter for 99% here. CBCs are extemely cheap.