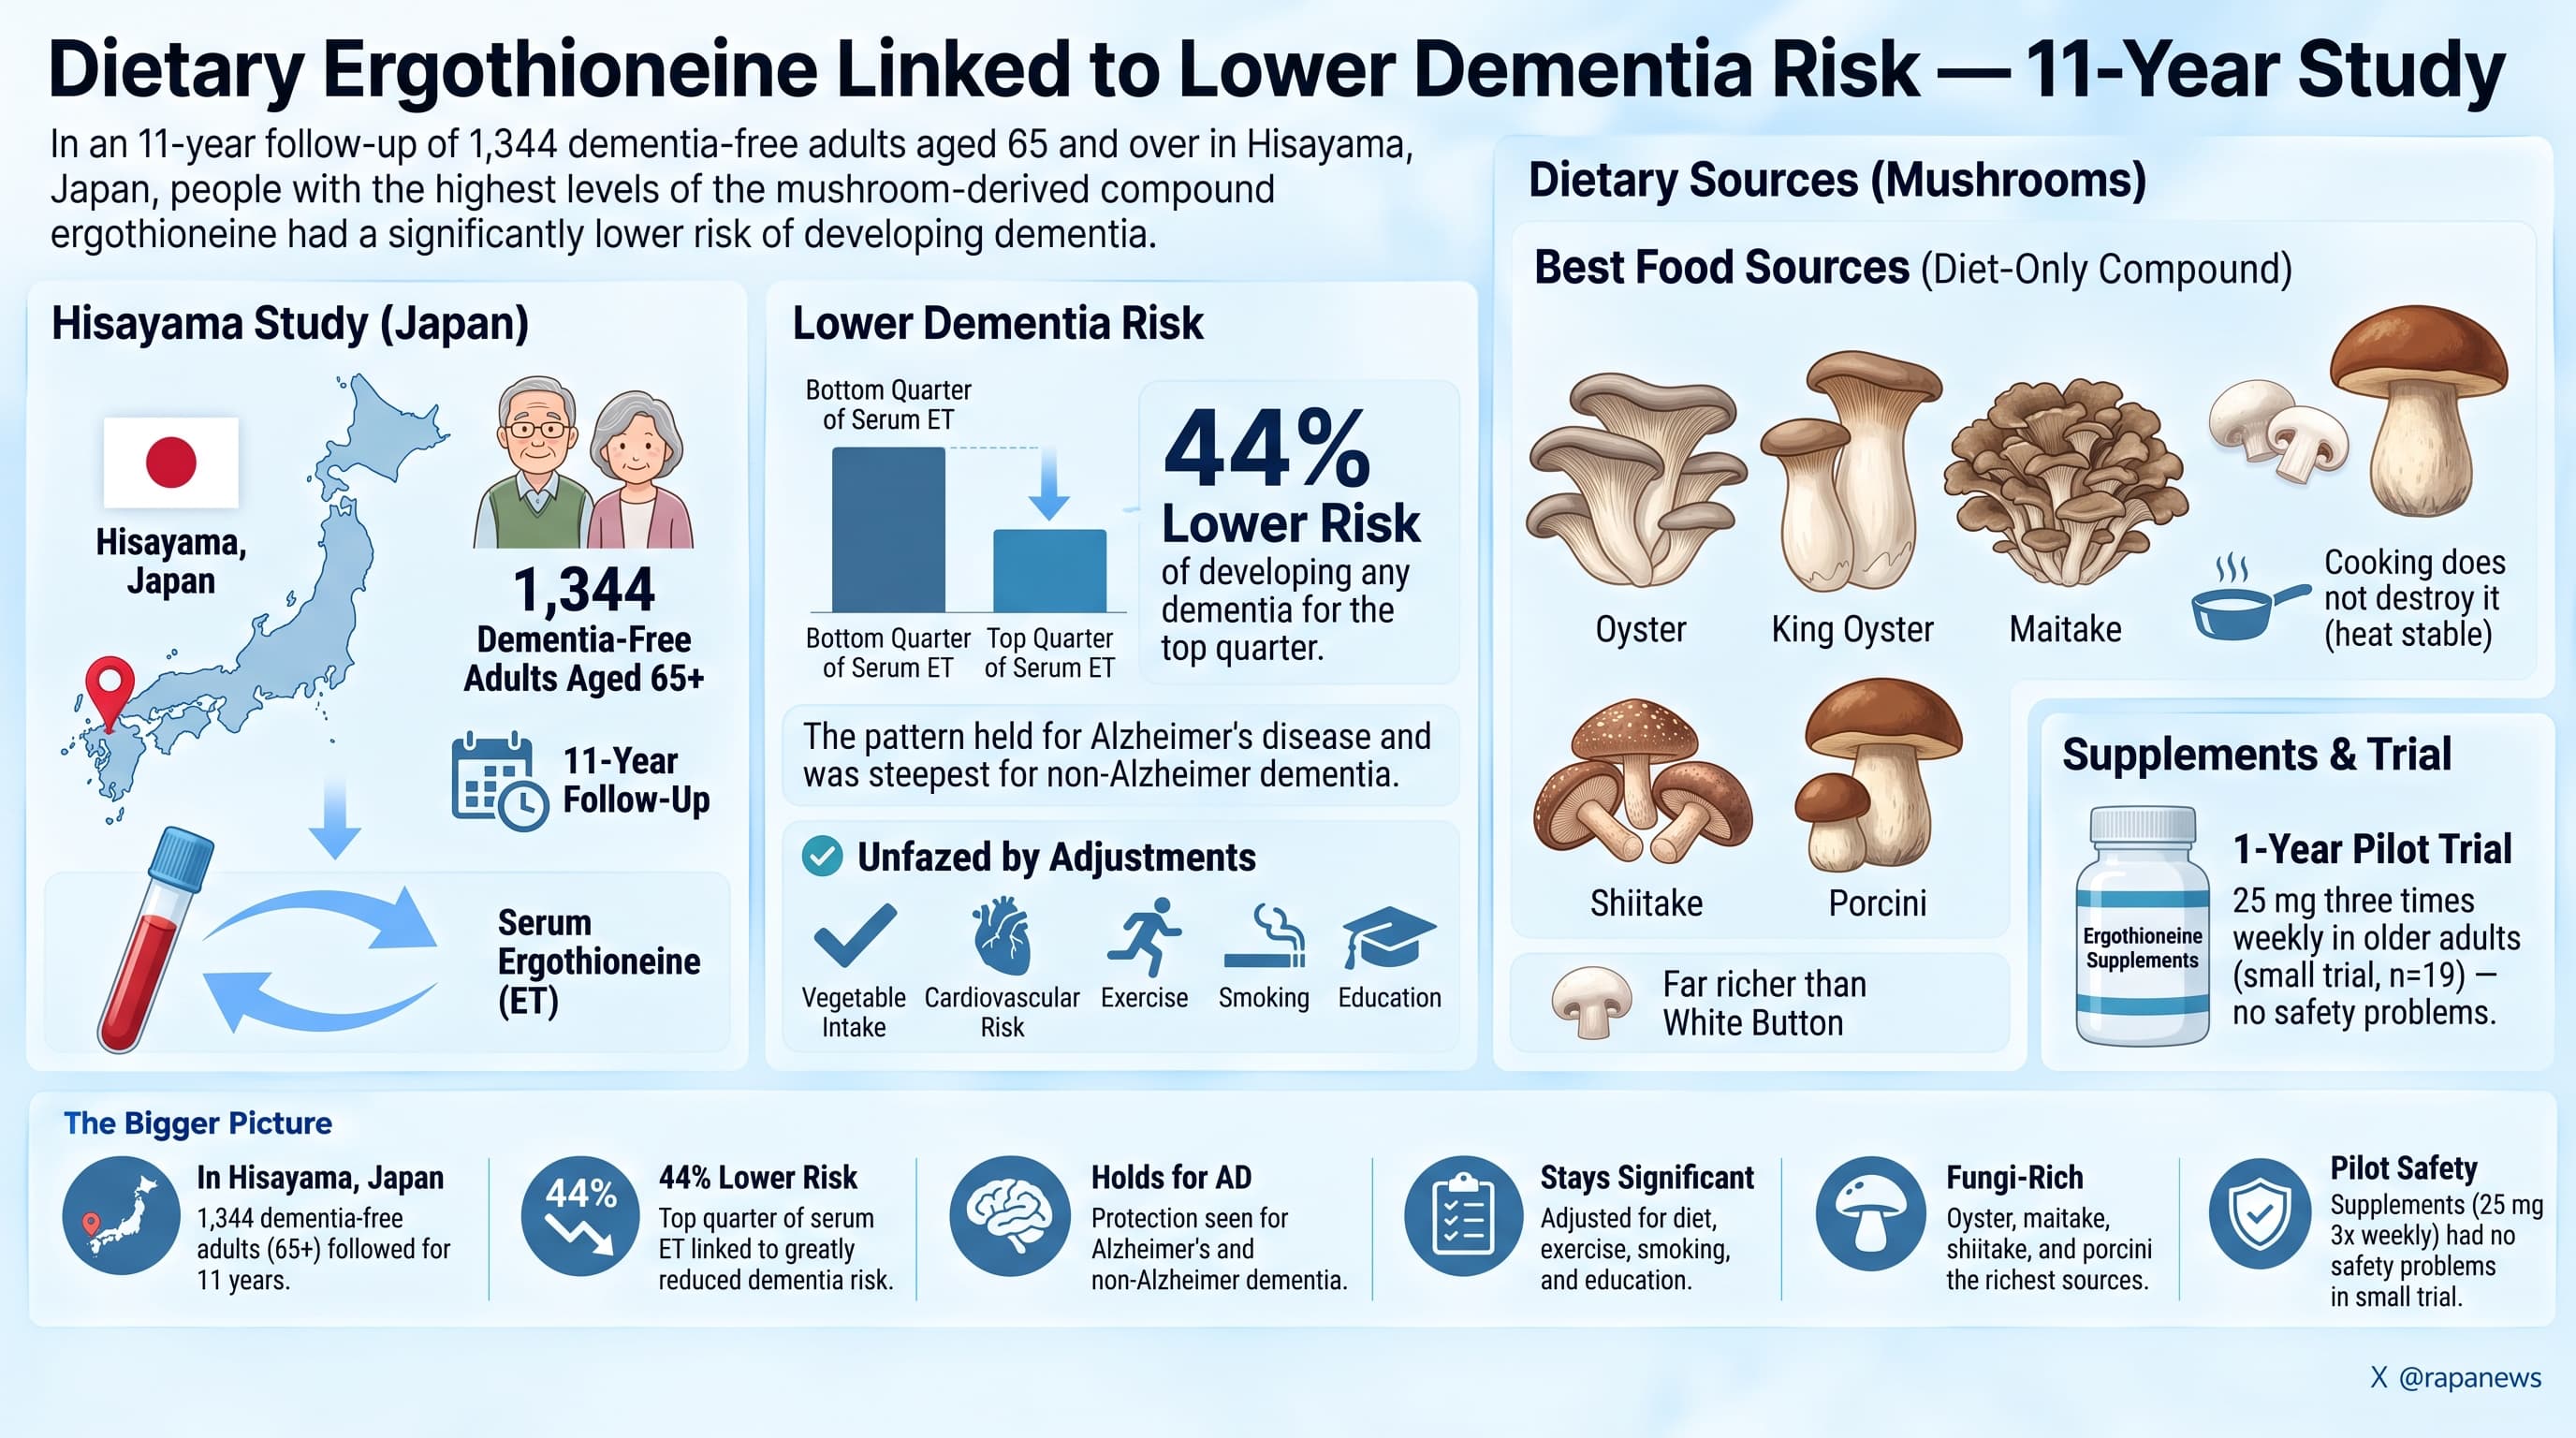
In a 11-year follow-up of 1,344 dementia-free adults aged 65 and over in Hisayama, Japan, people in the top quarter of serum ergothioneine had about 44% lower adjusted risk of developing any dementia than those in the bottom quarter. The pattern held for Alzheimer’s disease and was steepest, though statistically imprecise, for non-Alzheimer dementia. Adjusting for vegetable intake, cardiovascular risk factors, exercise, smoking and education did not erase the link. Ergothioneine is a dietary compound concentrated in mushrooms. Supplements are also available.
Ergothioneine is an odd molecule. Fungi and some soil bacteria make it, humans cannot, and yet we carry a dedicated transporter (OCTN1) that pulls it out of the gut and concentrates it in tissues under oxidative stress, including the brain. That evolutionary investment has made researchers suspect it does something important. A new analysis from the long-running Hisayama Study adds the strongest population-level evidence so far that it may matter for the aging brain.
The Hisayama Study has tracked the health of an entire Japanese town since 1961, with participation rates that most cohorts can only envy. In 2012 and 2013, researchers drew blood from 1,344 residents aged 65 and older who did not have dementia. A decade later, they thawed the frozen serum and measured ergothioneine using mass spectrometry. Over a median of 11.2 years, 273 people developed dementia: 201 with Alzheimer’s disease and 72 with other forms, mostly vascular.
The result was a clear gradient. Dementia appeared at a rate of about 31 cases per 1,000 person-years in the lowest ergothioneine quarter, falling to about 13 in the highest. After accounting for age, sex, blood pressure, diabetes, cholesterol, body weight, stroke history, smoking, alcohol, exercise, education and vegetable consumption, the top group still had a 44% lower risk. The relationship looked roughly linear, with no obvious threshold where benefit kicked in or plateaued.
The vegetable adjustment matters. Mushroom eaters tend to eat more vegetables, and vegetable intake itself predicts lower dementia risk in this same cohort. Here, high ergothioneine predicted lower risk whether people ate a lot of vegetables or not, while high vegetable intake without high ergothioneine produced only a weak, non-significant reduction. That points toward something specific about ergothioneine, or about the foods that supply it, rather than generic healthy eating.
Another detail strengthens the case slightly. Serum ergothioneine did not predict death from any cause. If high levels were simply a stamp of overall robustness, you might expect them to track with survival too.
The biology is plausible. Ergothioneine neutralizes several aggressive oxidants, binds metals that catalyze free radical damage, protects blood vessel lining in cell studies, and reduces amyloid plaques in Alzheimer’s mouse models. More recent work suggests it is not merely a passive antioxidant: it binds and switches on a mitochondrial enzyme involved in energy production.
But the limits are real. The biggest is reverse causation. Alzheimer’s brain changes begin 15 to 20 years before diagnosis, and early cognitive decline narrows diets and dulls appetite. People already on the path to dementia may simply eat fewer mushrooms. The researchers excluded cases diagnosed in the first two years, which barely touches that problem. The ergothioneine was measured once, from serum stored for a decade. Four authors work for Suntory, which also helped fund the study and ran the assays. And the cohort comes from one Japanese town with high mushroom consumption, so the absolute numbers may not transfer to Western populations.
What the study does is move ergothioneine from “interesting antioxidant” to “credible candidate worth a proper trial.” A small year-long pilot trial in people with mild cognitive impairment has already reported encouraging signals. A large randomized trial is now the obvious next step.
Actionable Insights
The practical message is modest but low-risk: eating ergothioneine-rich mushrooms regularly is a reasonable bet for brain aging, but the evidence does not yet prove it prevents dementia.
How big is the association? Over roughly 11 years, about 27 of every 100 people in the lowest ergothioneine group developed dementia. Applying the fully adjusted hazard ratio of 0.56 to that baseline suggests about 16 to 17 of every 100 would develop dementia at the highest levels. That is an absolute difference of about 11 people per 100, meaning roughly 9 people would need to have “high” rather than “low” levels for one fewer dementia case over a decade. This assumes the link is causal, which it may not be.
In statistical terms, this is a small-to-moderate effect, roughly comparable to the gap between regular exercisers and sedentary people in many dementia cohorts.
Best food sources: oyster, king oyster, maitake, shiitake and porcini mushrooms are far richer than white button mushrooms. Cooking does not appear to destroy much of it.
Supplements exist. A year-long pilot trial used 25 mg three times weekly in older adults without safety problems, but it involved only 19 people. This paper itself provides no safety data on supplementation: Safety Data Absent.
Context and Source
- Open Access Paper: Serum ergothioneine and risk of dementia in a general older Japanese population: the Hisayama Study, Published 2025 Dec.
- Institutions: Kyushu University Graduate School of Medical Sciences (Departments of Neuropsychiatry, Epidemiology and Public Health, and others), Fukuoka; Suntory Global Innovation Center, Kyoto
- Country: Japan
- Journal: Psychiatry and Clinical Neurosciences
- Impact evaluation: The impact score of this journal is 6.2, evaluated against a typical high-end range of 0 to 60+ for top general science (with leading psychiatry titles reaching roughly 20 to 60), therefore this is a Medium impact journal.
Related Reading:
- The Mushroom Molecule That May Rewrite Aging: Ergothioneine Emerges as a Multi-Target Geroprotector
- Why Your Antacids and Smoking Habit are Aging Your Brain, and Why Ergothioneine Might Save it
- Ergothioneine Extends Lifespan and Halts Cognitive Decay in Deficient Male Mice
- Mushrooms on My Mind, Ergothioneine , Erinacines, Hericenones, etc