First of all, without supplements I have a decent sleep so I am just perfecting it. I can notice the effects with just a simple Melissa tea (i let it steep for an hour or so). Right now I am experimenting with the lemon balm capsules with similar effects (7% concentrated, rosmarinic acid 35mg).
1 Like
I can comment on DORA and MagBark, N=1:
MagBark: at 200mg caused me a rash, which went away when I stopped. I’m staying clear of it for a while.
DORA (Dual orexin receptor antagonists) is a newer class of insomnia meds that work by blocking signals in the brain that stimulate wakefulness. I used Belsomra/suvorexant.
Damned sweet. One of the cleanest sleep aids I’ve ever used. And no sedation effects by morning, which with my clearance pathways makes it a rare treasure.
However:
-
Can cause next day mood-drop, esp if your genetics runs a tight ship on dopamine, as mine does. For me, 10mg was enough to make me flat and irritable the next day, and frankly, I’d rather be tired. (Claude: “Blocking orexin doesn’t just reduce wakefulness drive, it reduces the motivational and affective tone those projections support. Flat and irritable is consistent with dampened orexin-mediated NE and dopamine tone.”) I’ll probably stay to the lowest effective 5mg, if I use it at all.
-
Expensive, depending on your insurance. This is not a cheap ride. But if you’re willing to risk the flat/irritable, it can be an incredibly effective sleep aid for those for whom GABA-related interventions are useless.
1 Like
Maulik sells lemborexant fairly reasonably priced. I’ve not purchased any yet.
Trialling microdose occasional progesterone (3-6mg every 2-5 days) and it seem to be wildly effective and improving sleep. As long as no sexual side effects occur this seems quite effective.
Still tempted to get some lemborexant just to have on hand.
Magnolia bark is also quite effective for something natural and doesn’t really cause any side effects except sometimes next day tiredness.
2 Likes
Yes, that explains it pretty well for me, too. Unfortunately only the 10 mg dose works for me.
1 Like
Sympathies. Let me know if you find a solution to the next-day flat/irritable.
Same here. My issue with melatonin is the next-day low mood. If someone has a potential solution for that, I will be very grateful.
Forgive my bad memory, but I vaguely remember you saying you use lithium orotate to stabilize your mood. Has it stopped working for you?
I don’t necessarily have an answer for that as there are variations between individuals. Timing compared to the Ultradian cycle is important as it has effects (I think inhibitory) on CRH, ACTH and Cortisol.
This is hard as knowing the timing of your ultradian cycle is hard. You can tell from sleep cycles at night and guess from that using a frequency of say 90-110 minutes.
If people are up for this I can suggest some ideas. Ideally I need to know the timing of sleep cycles from a fitness tracker. Look for cycles at about 1 1/2 hours.
Then I need to know what size pills people have. I use 12mg, 20mg and 60mg pills and last night I took about 2.5g (which for those who want the figures in nano grams is 2,500,000,000 ng).
You might say even with 60mg pills that’s a lot of pills. Indeed it is although I took 300mg (15x20mg) when I started drinking earlier in the day.
Now I would not suggest anyone did exactly what I do as it could have unpredictable effects. I know what the effects are on me.
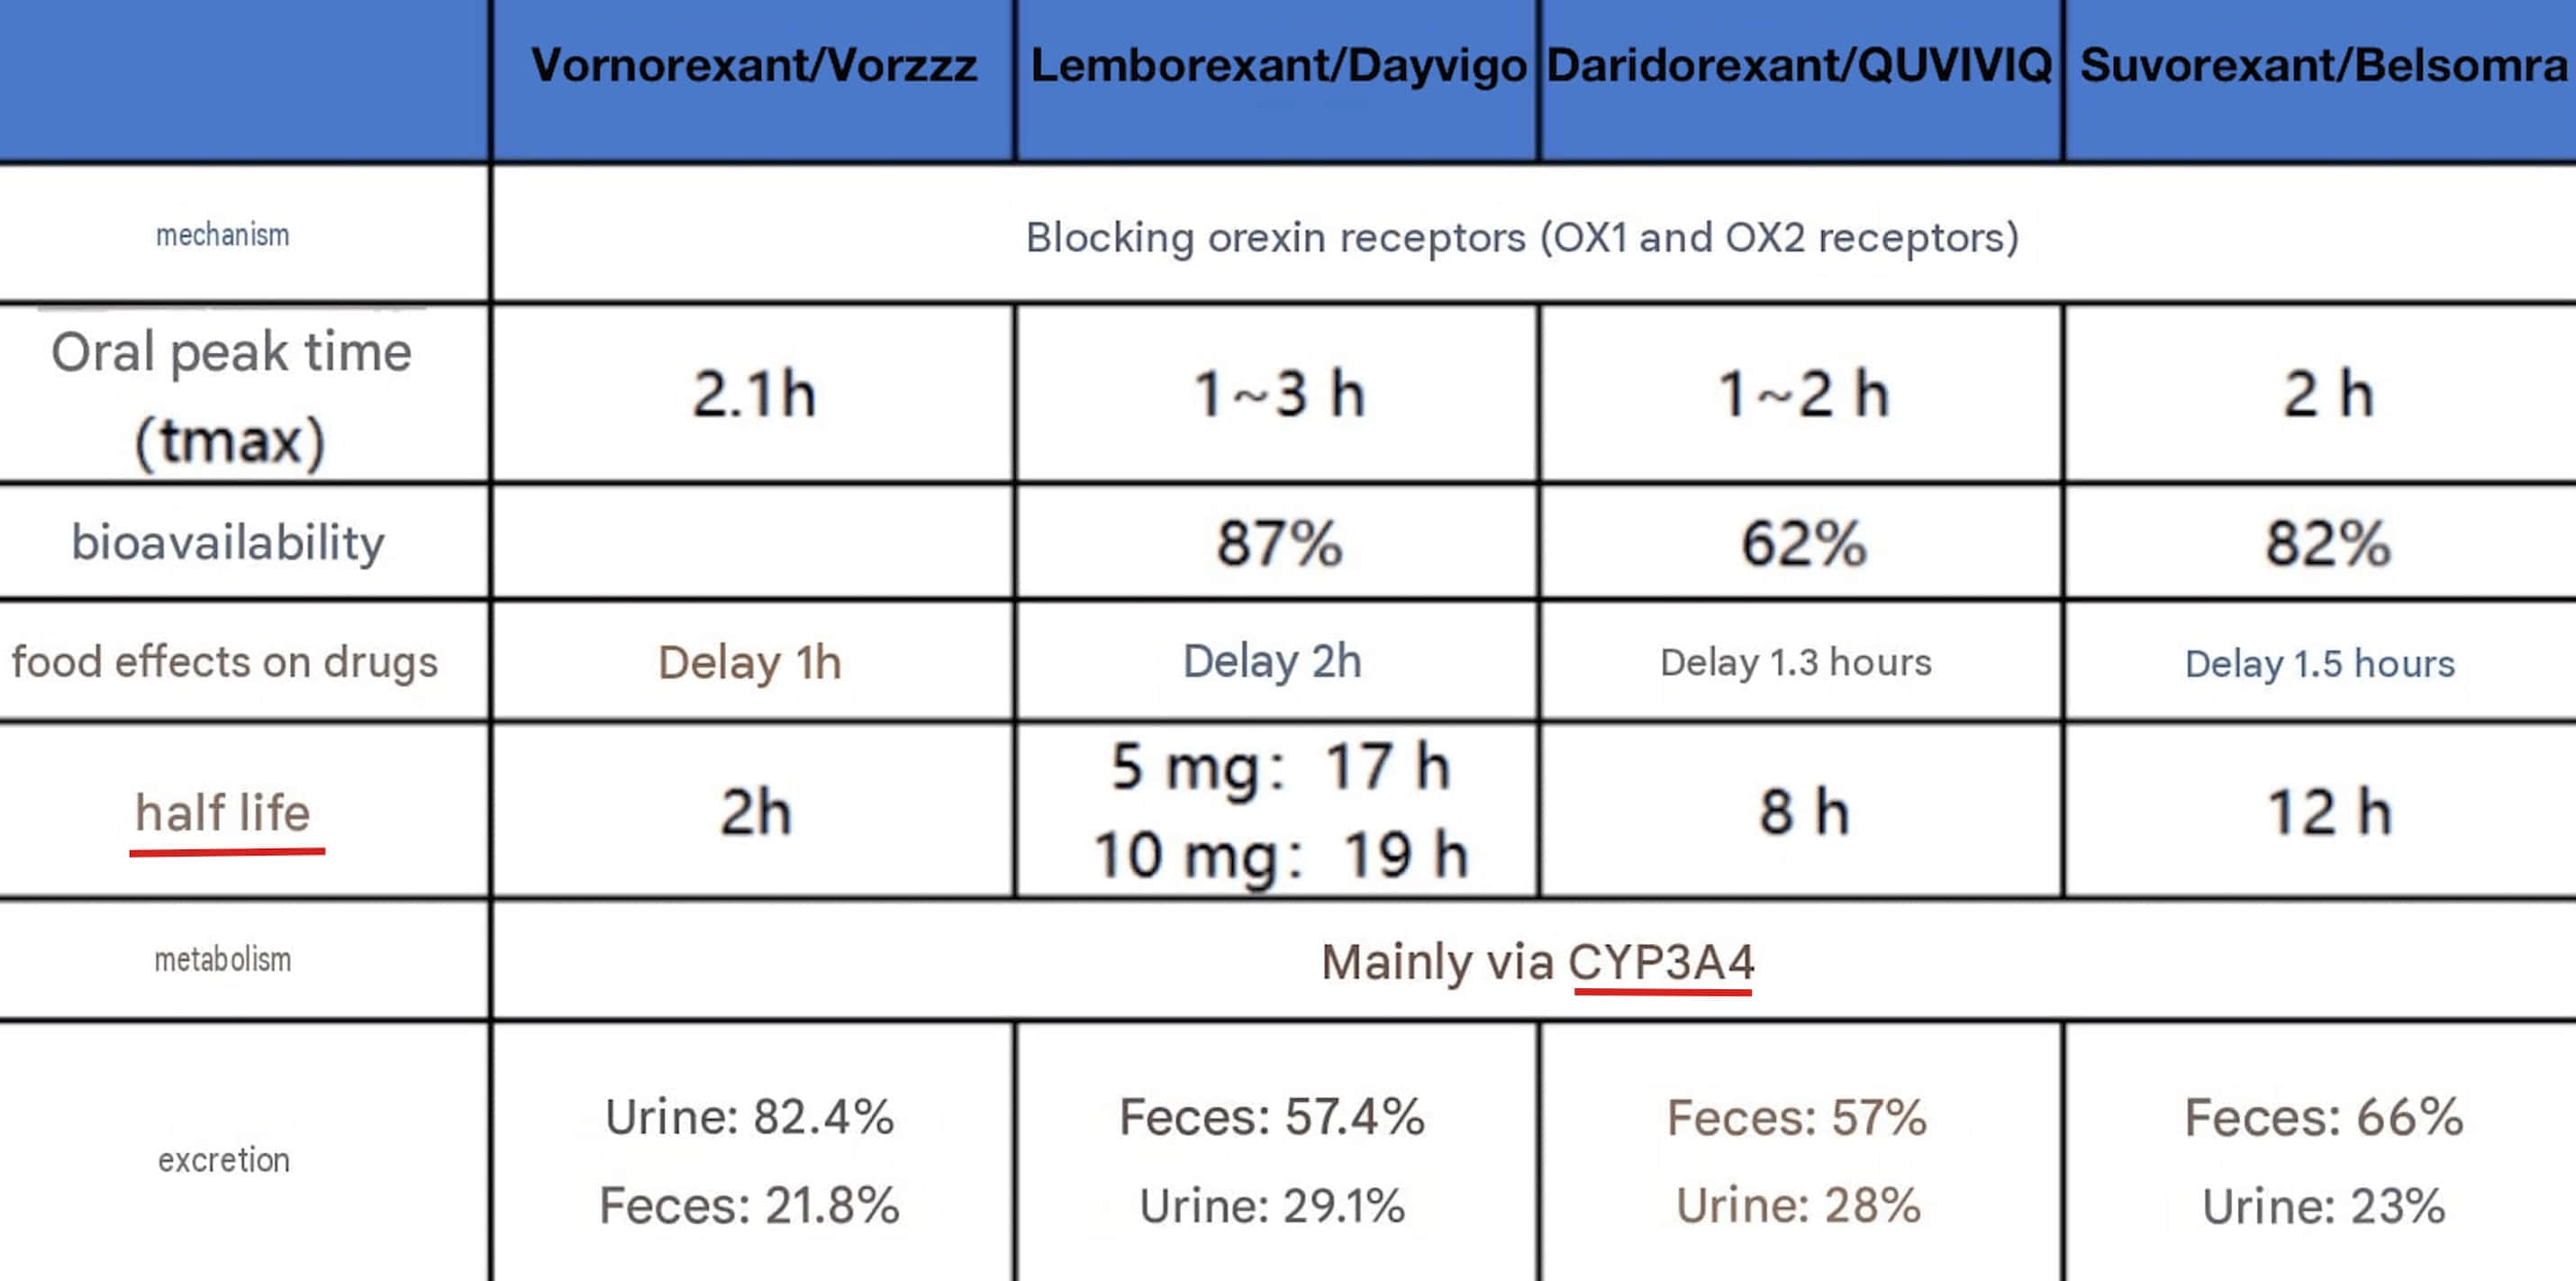
All 4 DORA medications exert hypnotic effects by blocking OX1 and OX2 receptors, with generally good oral absorption. Fasting administration leads to a faster peak concentration, whereas a high-fat diet delays the absorption peak. All are metabolized by the hepatic CYP3A4 enzyme and excreted via a dual fecal-urinary pathway. The core differences lie in their time to peak concentration, bioavailability, and half-life, which directly affect the onset speed and daytime residual effects. There is no absolute superiority or inferiority; they are simply suited for individuals with different sleep-wake schedule needs. Specific parameters are shown in Table.
1. Vornorexant/Vorzzz
- Pharmacokinetics: It has a short half-life of only 2 hours and the fastest metabolic clearance rate.
- Advantages: It leaves low residual drug concentrations in the body the morning after administration. Clinical studies have confirmed that 9 hours after dosing, it causes no significant functional interference with driving or precision tasks [9].
- Drawbacks: Its duration of action in the body is short. For individuals with frequent night awakenings or early morning awakenings, drug coverage is insufficient to stably maintain a full night’s sleep.
2. Lemborexant/Dayvigo
- Pharmacokinetics: It has the longest half-life (17 to 19 hours), providing drug coverage across the entire night’s sleep cycle with sustained suppression of night awakenings and early awakenings.
- Drawbacks: The long half-life presents a significant drawback: at high doses (10 mg), the risk of residual daytime somnolence and fatigue the following day is significantly increased, carrying a higher probability of adverse reaction exposure in elderly and constitutionally sensitive populations.
3. Daridorexant/QUVIVIQ
- Pharmacokinetics: With a half-life of 8 hours, it falls between short- and long-acting formulations, features rapid absorption, and has a relatively mild delayed effect from high-fat meals.
- Clinical Profile: Its moderate half-life balances nighttime sleep maintenance with daytime drug clearance, and the overall risk of residual somnolence is controllable. However, the efficacy of the low dose (25 mg) in extending total sleep time is limited.
4. Suvorexant/Belsomra
- Pharmacokinetics: It has a half-life of 12 hours with distinct long-acting characteristics, stably reducing night awakenings.
- Drawbacks: Its efficacy in improving sleep onset speed is weaker than the other three medications. The risk of daytime somnolence is at a medium-high level, making it unsuitable for individuals who require high levels of concentration during the daytime.
Reference: 长效睡不醒、短效难维持?4款DORA类失眠药临床如何选择?
I do not use lithium orotate to stabilize my mood, therefore it has not stopped working for me. 
1 Like
Seems like vornorexant or Daridorexant would be best for most people, and if somehting between the two in terms of half life were to come out it might be ideal for most.
1 Like
Fazamorexant half-life is 1.9 ~ 3.7 hours.
2 Likes
I was informed by Maulik today that he is no longer exporting to U.S. “too much paperwork and declaration”.
Any information on which exporters still export to U.S.?
REALLY!!!??? Shoot, I was just about to stock up on Maraviroc.
Ok, yeah, now I need other names as he is my go to guy. Sigh.
1 Like
Note from him today (9/23):
Hello Sir
Yes, shipping is ongoing
I ship to USA daily
Someone posted wrong
Will share details tomorrow morning
It’s near to midnight here
Thanks
Maulik
3 Likes
Lemborexant ameliorates tau-mediated sleep loss and neurodegeneration in males in a mouse model of tauopathy
2 Likes
Davigo
Most people will only need 5 mg, and some even split that in half.
Anecdotal reports from social media such as Reddit most report a clean sleep with no hangover effects in spite of its long half-life.
2 Likes
I’ve been taking Dayvigo 5 mg for about three months now. I did take Trazadone 50 mg for about a year, and it was hit and miss. Frankly, the CBTi did a better job than the Trazadone, but didn’t significantly improve my sleep. Overall, my sleep is much better with Dayvigo. I still seem to wake at 4:30 am, sometimes read for a few minutes, but I manage to fall back to sleep for another 60 to 90 minutes, and that’s where the Dayvigo is doing its job. In the past, I was up at 4:30 am and got my day (sort of) started. I now feel rested and generally much better - so far, I’m quite pleased.
6 Likes
Trazadone is primarily for reducing sleep onset time. I keep some by my bedside in case I inadvertently wake up and can’t go back to sleep.
I’m seeing anecdotal reports online of people with sleep apnea taking DORAs and having particularly good sleep. The best they’ve ever had. But I’ve seen no subsequent CPAP or sleep study data showing how it impacted AHI.
Has anyone with sleep apnea who uses CPAP or has taken a sleep study before and after taken these drugs and how has it impacted AHI?
1 Like