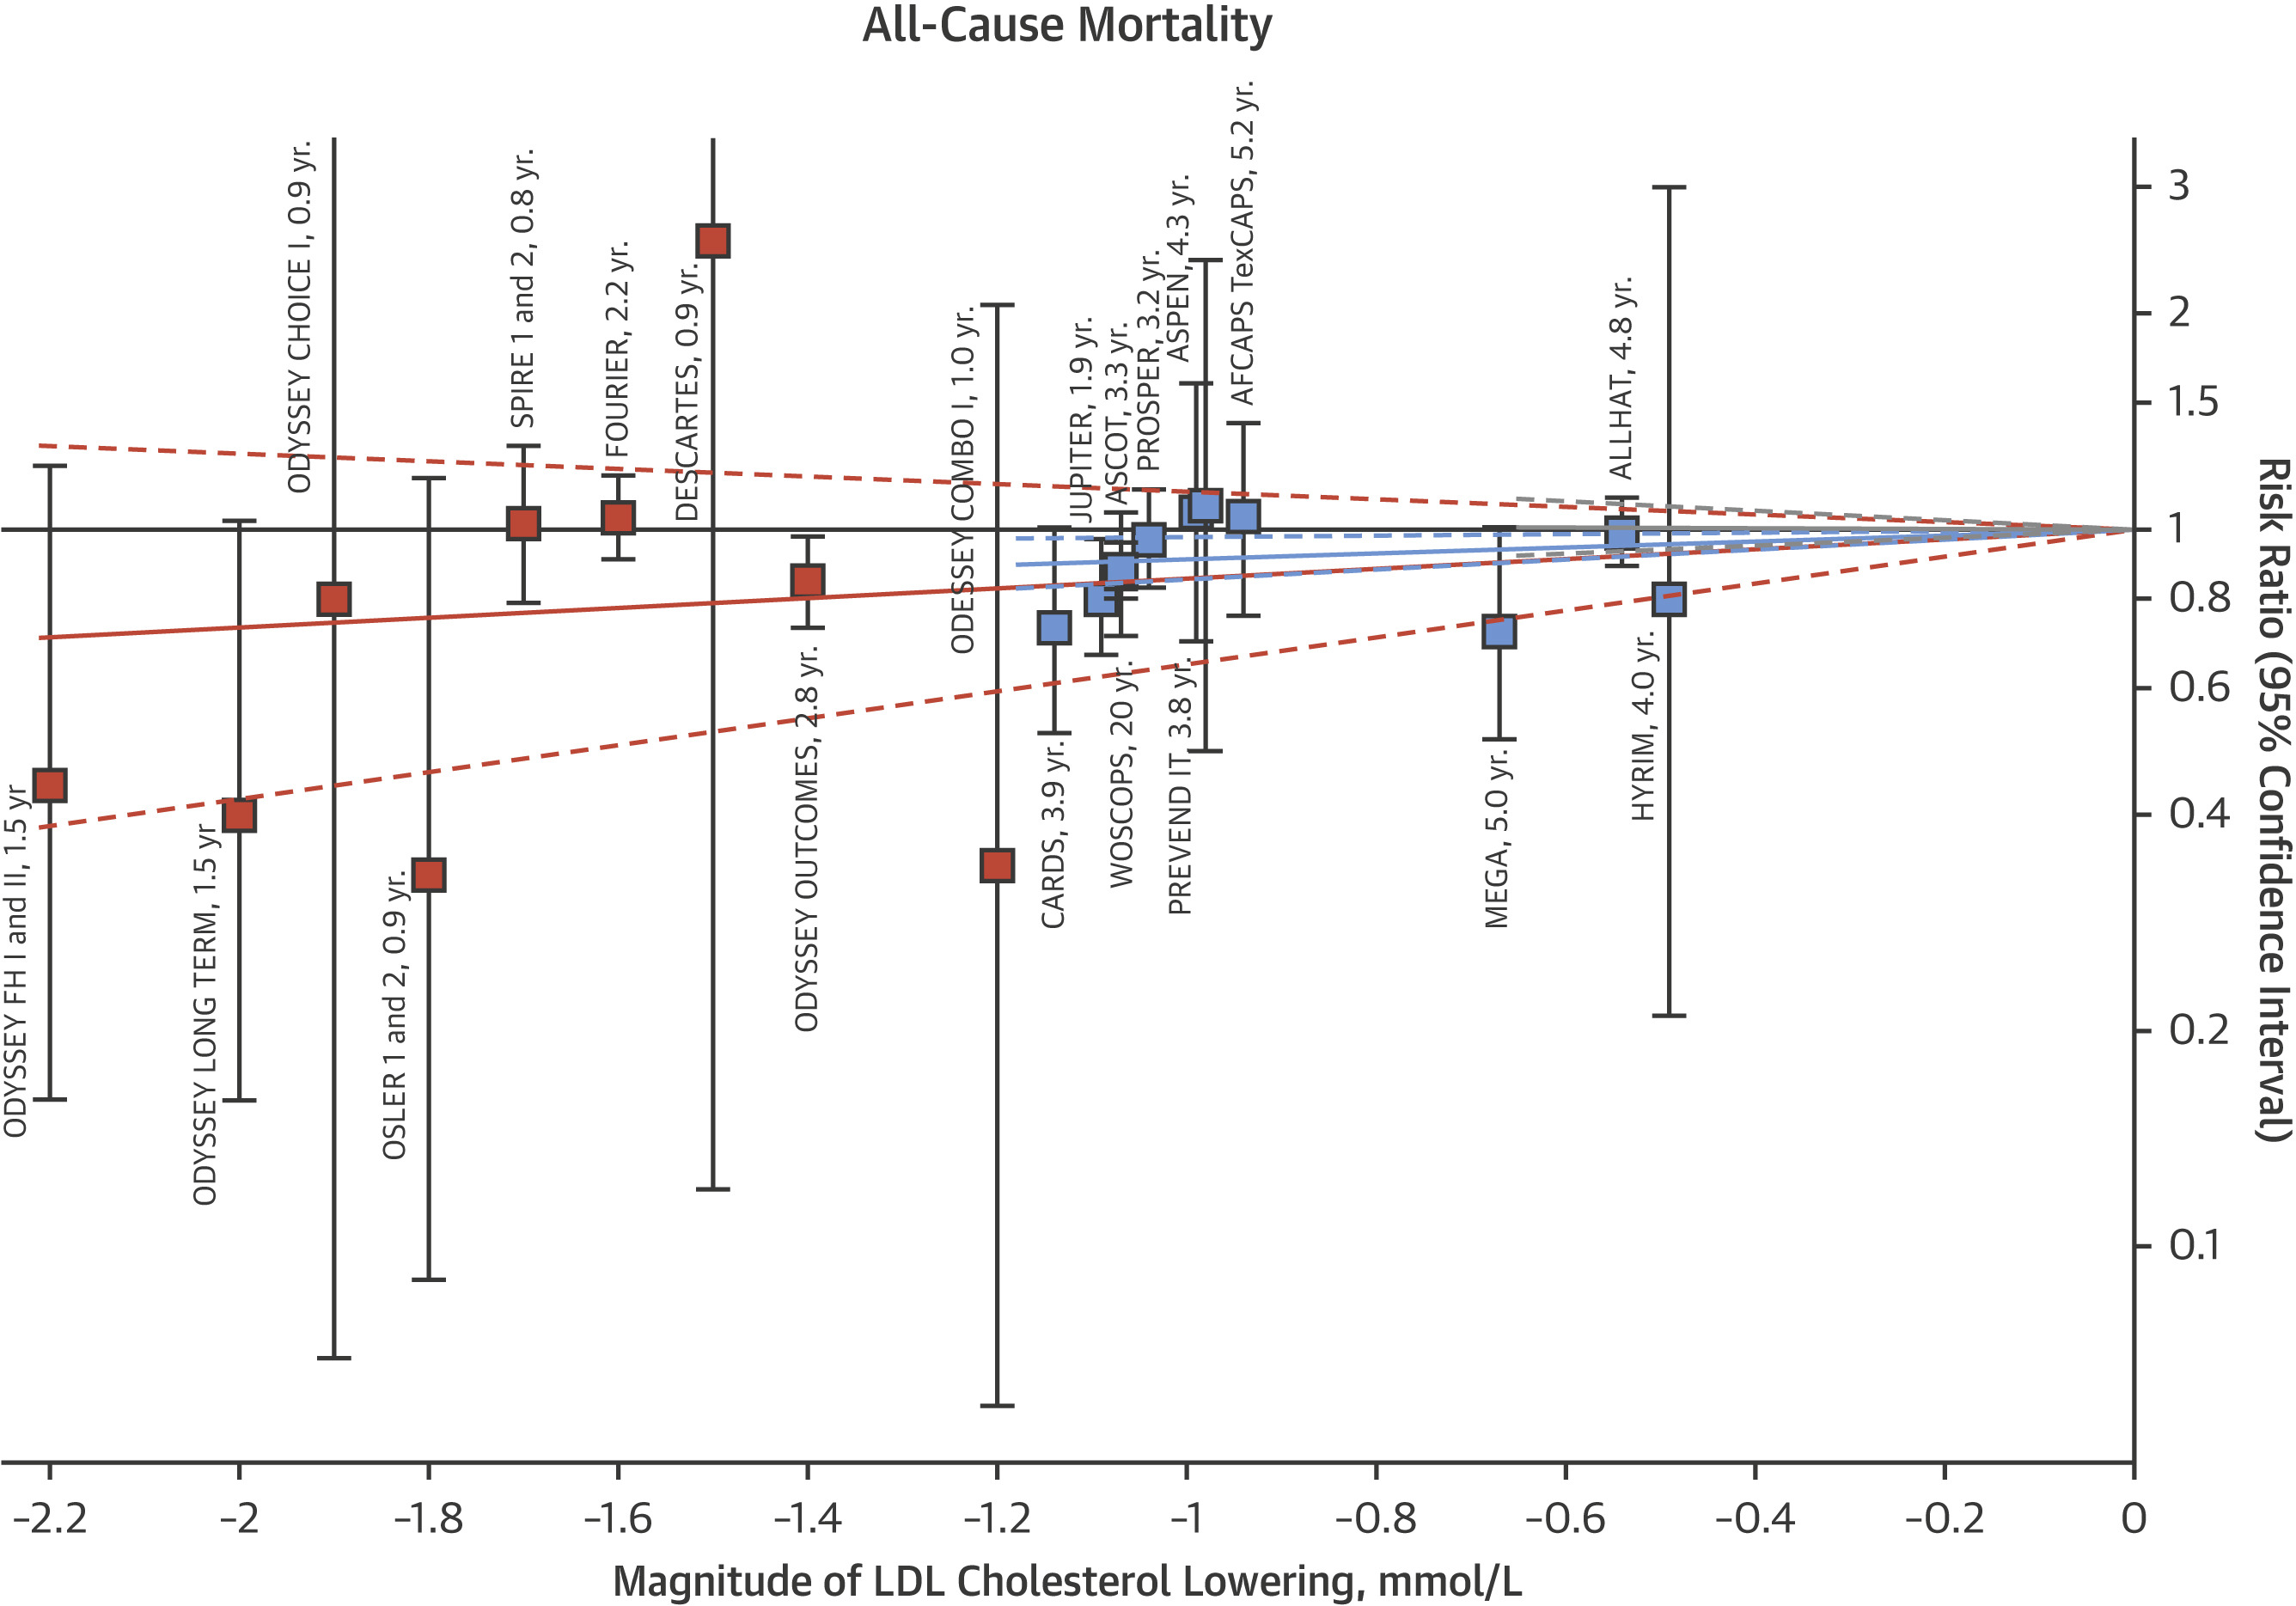
I encourage everyone to watch the Peter Attia/Layne Norton podcast linked above. Once done, I think you would find it difficult to embrace the myth that low LDL is problematic and reducing elevated LDL is not beneficial. The adverse effects of elevated LDL are cumulative and occur over a long period of time. It is an independent risk factor that is not offset by high HDL. Peter uses the example of investing at 4% rate of turn versus 6%. After three to five years (the length of most studies) the differences are very small. After 40 to 50 years the differences are staggering. This is not to say that some of the drugs designed to reduce LDL rather than via statins are not harmful. Some definitely are.
6 Likes
I also believe Peter was on Andrew Huberman’s podcast( or it might have been the podcast you linked, I dont remember) but he says that ApoB is necessary for atherosclerosis so the focus should be on lowering that more than anything.
4 Likes
This reminds me so much of our beliefs years ago about HDL cholesterol. It was believed to be highly protective, and the higher the better. In fact, we felt that if we developed a drug to significantly raise the levels and administer it young enough, we might be able to stop CAD altogether.
So we developed that drug and had to abort the study due to the significant cardiovascular mortality risks that ensued. It did raise HDL however, but people were having heart attacks.
Now we know that HDL is U shaped.
Those of us in the medical profession realize that we are frequently mistaken, that what we think we know for sure today is often shown to be false tomorrow.
Dramatic lowering of lipids hasn’t been clearly shown to have a favorable risk/ benefit profile, and until it does through multiple well designed and controlled studies, caution is in order.
This is particularly true for the otherwise low risk patient where the benefits are even less clear.
2 Likes
My HDL has always been very high. Last test- 147 mg/dl. I asked my cardiologist to comment and he said “Not to worry about it” and he did not see any increased risk of CAD. He is one of the best cardiologists in SF.
I have a very healthy diet with a lot of Chia seed, Fllax seed, Fish oil, Fish and nuts.
My Teriglicerides are very low at 32 and LDL- 75.
I agree with you, that we still don’t understand a lot.
3 Likes
Wow. Those are amazing numbers.
1 Like
My HDL is high also. That was one of the few items that inside tracker flagged for being outside the optimal range. But only 82 MG.
2 Likes
How long did it take before you we feeling the benefits? I do seem to have more energy and different sleep patterns, I am six weeks in on the clinical trial.
1 Like
Hi Patty for me it was within 2-3 weeks…I felt it in my heart… heavy… repairing and in my veins… they increased in size… like I just worked out.
Could hear my blood pulsating in my head.
End of week twelve euphoria and visceral fat started dissolving.
Sounds like you are on the real stuff.
Can’t wait for the euphoria and fat reduction!
1 Like
If rapa increases gene expression which i think it does then it should increase the basal metabolic rate. Hic!
2 Likes

5 Likes
Attia’s TLDW is that apo-b is what matters and we should do what we can to lower it.
2 Likes
I would note that FOURIER had a follow-up of about 2 years. As a reference point, statin mortality curves don’t begin to separate until 2 years. It’s usually really difficult to figure out the exact cause of death, so I’m not concerned about some post-hoc adjudication process finding fewer CV deaths in both arms to the point where it seems evolocumab looks worse than placebo for CV deaths.
I’d check out the FOURIER extension study - FOURIER-OLE, which had a follow-up of 5 years and showed a statistically significant reduction in all-cause mortality (HR 0.85, 95% CI 0.75-0.96) for evolocumab, lower risk of CV deaths, MIs, or stroke (HR 0.80, 95% CI 0.68-0.93), and if you stratify it out - a lower risk of CV death (HR 0.77, 95% CI 0.60-0.99).
I’d imagine if one adjudicates this, they’ll find it unlikely to reclassify whether someone died or not.
The all-cause mortality is really what matters and there’s suggestive evidence that evolocumab is significant at reducing death, while the reanalysis on the 2-year mark is probably not significant.
Note that the study authors of the reanalysis of 2-year FOURIER themselves said the CV mortality was nonsignificantly increased. This is right around where we would expect no mortality benefit.
Faced with long-term reduction of all-cause mortality which appears to be replicated in a variety of clinical situations among many clinical trials for all PCSK9 inhibitors, I’d take more stock at least for those who are indicated, even with the uncertainty for all the possible functions for PCSK9.
https://www.ahajournals.org/doi/10.1161/CIRCULATIONAHA.122.061620
6 Likes
Yeah HDL seems to be one of those things where as more time passes, the less I seem to know. HDL seems to be a mixed bag - some sub-particles may be “good” and we recently discovered some may be “bad”.
That being said, I wouldn’t quickly conclude tinkering with the HDL side of things will never yield results. You may want to look into ApoA1-Milano - the peeps who had it naturally had “low HDL” but it appeared to be more efficient at cholesterol efflux.
Still waiting on AEGIS-II phase 3 results, AEGIS-I phase 2b showed infusing plasma-derived apolipoprotein A-1 enhanced cholesterol efflux and reduced atheroma volume enough to the point where they felt it was worth betting on phase 3.
5 Likes
All cause mortality doesn’t only matter even if it’s important. It probably is there, just it wasn’t a long enough study duration. Or enough participants. Heart attacks lower quality of life and healthspan, which is why you can’t dismiss a study just because it couldn’t measure ACM benefit. But like I said it is often because of practical reasons you cant find a difference. It costs a lot to run long studies and/or with many participants.
That said it was brought up in the article I linked earlier that focusing on all cause mortality would bypass this adjudication process debate. You only measure amount of deaths in both arms and no rogue doctors can start making their own conclusions unblinded who died by what.
I saw that follow up study with ACM benefit but I didn’t understand why they didn’t have a p-value so I didn’t bring it up. Do you know why? And why we can be certain about the result?
2 Likes
very cool that a lot of folks could just take one dose and lower one’s LDL forever…clinical trials underway now…
Reported in the highly respected JAMA.
Meta analysis of 11 randomized controlled trials of over 65,000 people show no total mortality benefit for statin usage in primary prevention even in those with intermediate to high risk, except for those with known CVD.
I see no need for the person with an elevated LDL from rapamycin, free of underlying CVD, to take statins to prevent a primary cardiovascular event. My position hasn’t changed.
2 Likes
You cannot say it had no total mortality benefit if it wasn’t statistically significant.
You cannot say anything about a result if it was not statistically significant.
You do realize that significant means “statistical significance”, not “significant” as it’s commonly used?
“show no total mortality benefit” does not mean there wasn’t a mortality benefit.
Absence of evidence does not mean evidence of absence.
4 Likes
I’m aware of those distinctions.