Here, again, is my favorite YouTube Doctor who is a real doctor talking about peptides. He talks at the speed I like with the enthusiasm I like, and I wish he was my doctor. Now, on a day to day basis I’m sure he isn’t this animated, but it’s the right approach for a presentation on Youtube.
If you like him you’ll find that he also has a wide variety of other videos related to peptides, SARMS, etc. I think you will like him!

Executive Summary
The reviewed presentation provides a critical deconstruction of viral claims regarding peptide therapeutics, evaluating biomedical evidence against public commentary. The primary thesis demonstrates that categorical dismissals of peptide pharmaceuticals conflate foundational molecular biology with regulatory, sourcing, and clinical trial realities. Categorizing peptides as an untested or intrinsically hazardous class ignores over a century of translational medicine, beginning with the extraction of insulin in 1921 through modern GLP-1 and dual GIP/GLP-1 receptor agonists validated in high-powered randomized controlled trials (RCTs). The presenter contextualizes the structural taxonomy of peptides—defined biochemically as polymers of two to approximately fifty amino acids linked by amide bonds—differentiating them from large macromolecular biologics such as 150 kDa monoclonal antibodies.
Addressing the hypothesis that pentadecapeptide BPC-157 inevitably precipitates occult oncogenesis through pro-angiogenic activity, the commentary bifurcates vascular biology into physiological versus pathological angiogenesis. While physiological neo-vascularization operates under homeostatic, self-limiting feedback loops mediated by vascular endothelial growth factor receptor 2 (VEGFR2) and endothelial nitric oxide synthase (eNOS), pathological tumor angiogenesis exhibits disorganized, hyperpermeable vascular architecture driven by sustained oncogenic signaling. Drawing an equivalency between pro-angiogenic tissue repair and oncogenesis disregards shared mechanistic pathways present in standard-of-care modalities, such as resistance exercise, hyperbaric oxygen therapy, and postmenopausal hormone replacement therapy.
Furthermore, regulatory claims concerning the United States Food and Drug Administration (FDA) terminating clinical evaluations of BPC-157 due to catastrophic toxicity are historically inaccurate. BPC-157 has never been evaluated under an FDA Investigational New Drug (IND) application; early Phase I/II evaluations were initiated offshore by European commercial entities and halted due to corporate acquisitions rather than agency-mandated safety terminations. However, the literature on BPC-157 exhibits a substantial translational gap: published preclinical data originates predominantly from a single academic laboratory, and prospective human safety cohorts remain absent. The primary clinical risk surrounding unapproved peptides stems not from inherent structural toxicity, but from unregulated gray-market sourcing, where non-compliant manufacturing produces variability in chemical purity, inaccurate active pharmaceutical ingredient (API) concentrations, and potential endotoxin contamination.
Insight Bullets
- A peptide is structurally defined as an oligomer composed of two to fifty amino acids joined by covalent peptide bonds.
- Categorical assertions that peptides lack clinical validation overlook the century-long clinical history of therapeutic peptides, starting with insulin in 1921.
- The landmark DCCT Trial (1993) validated intensive peptide therapy by demonstrating that tight insulin regulation significantly mitigates microvascular diabetic complications across 1,441 participants.
- Recombinant GLP-1 receptor agonists are synthetic peptides backed by large-scale randomized cardiovascular outcome trials.
- The SELECT Trial (Lincoff et al., 2023) established that the peptide semaglutide reduces major adverse cardiovascular events (MACE) by 20% in over 17,000 non-diabetic patients.
- The STEP 1 Trial (Wilding et al., 2021) proved the clinical efficacy of weekly 2.4 mg semaglutide in reducing total body weight in human randomized cohorts.
- Dual incretin mimetic peptides, such as tirzepatide developed by Eli Lilly and Company, have demonstrated glycemic and metabolic efficacy across the extensive SURPASS and SURMOUNT clinical programs.
- Synthetic peptide therapeutics have received regulatory clearance across oncology, endocrinology, and gastroenterology, including octreotide, leuprolide, teriparatide, abaloparatide, and linaclotide.
- Glycopeptide antibiotics, including vancomycin, serve as critical agents in hospital inpatient settings.
- Captopril, the first orally active angiotensin-converting enzyme inhibitor, was engineered from peptide fragments isolated from pit viper venom.
- Physiological angiogenesis represents an organized, self-limiting biological response to tissue hypoxemia and mechanical injury regulated by VEGF, FGF, and eNOS signaling.
- Pathological angiogenesis, first conceptualized by Folkman (1971), involves deregulated, highly permeable neo-vasculature driven by tumor-derived autocrine and paracrine signals.
- Physical exercise, hyperbaric oxygen therapy, and estrogen replacement therapy stimulate physiological angiogenic pathways without demonstrating causative oncogenic induction.
- Body Protection Compound 157 (BPC-157) is a synthetic 15-amino-acid sequence derived from human gastric juice protein.
- In vitro and animal studies indicate that BPC-157 modulates early growth response protein-1 (Egr-1) and VEGFR2 phosphorylation to accelerate soft tissue repair.
- Preclinical rodent models demonstrated no spontaneous malignant transformation following systemic BPC-157 administration, with select models showing protective effects against tumor-induced muscle wasting.
- The assertion that the FDA halted BPC-157 clinical trials due to acute human lethality is contradicted by global clinical trial registries.
- Early clinical evaluations of BPC-157 were initiated in Europe by pharmaceutical developer Pliva and discontinued following corporate acquisitions rather than regulatory safety actions.
- An exploratory Mexican Phase I safety trial in 42 healthy volunteers conducted by Pharmacotherapia remains unverified and unpublished in peer-reviewed literature.
- Over 80% of peer-reviewed preclinical literature on BPC-157 originates from a single research group at the University of Zagreb led by Dr. Predrag Sikirić, leaving a clear need for independent laboratory replication.
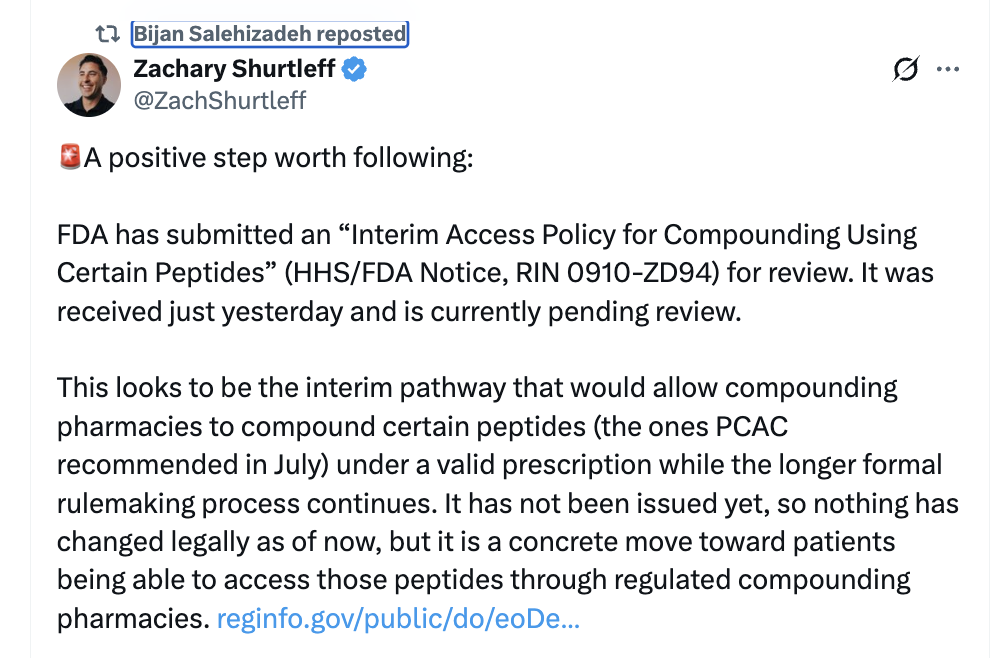
- The FDA removed BPC-157 from its Category 2 compounding review list in April 2026 after the underlying safety challenge nominations were formally withdrawn.
- Monoclonal antibodies such as aducanumab, lecanemab, and donanemab are 150 kDa multi-domain immunoglobulins, not low-molecular-weight peptides.
- As detailed in the Clarity AD Trial (van Dyck et al., 2023), clinical safety signals associated with anti-amyloid monoclonal antibodies involve amyloid-related imaging abnormalities (ARIA), not peptide-mediated toxicity.
- Synthetic melanocortin analog Melanotan II was halted by Clinuvel Pharmaceuticals during early development due to systemic blood pressure elevation and involuntary erectile stimulation rather than trial fatalities.
- Gray-market peptide sourcing introduces documented clinical hazards, including inaccurate API dosages, degradant byproducts, and bacterial endotoxin contamination.
- Market restrictions on regulated compounding pharmacies divert patient demand into unmonitored gray-market supply chains lacking cGMP compliance.
- Peptides and conjugated biologics represent one of the fastest-growing therapeutic pipelines across modern biotechnology.
Adversarial Claims & Evidence Table
| Claim from Video | Speaker’s Evidence | Scientific Reality (Current Data) | Evidence Grade (A-E) | Verdict |
|---|---|---|---|---|
| “Not one human randomized control trial has ever been done on peptides.” | Cited historical trials: insulin DCCT trial (1,441 patients), semaglutide trials (SUSTAIN-6, SELECT, STEP 1), and tirzepatide programs. | Extensive peptide drugs hold global regulatory approvals supported by phase 3 human RCTs. See the DCCT Trial (1993) and SELECT Trial (Lincoff et al., 2023). | Level A | Unsupported (Claim refuted) |
| “BPC-157 causes cancer via untargeted vascularization.” | Argued Folkman hypothesis differentiates physiological from pathological angiogenesis; cited pre-clinical animal models showing lack of oncogenesis. | BPC-157 activates VEGFR2 pathways in vitro, but there are zero peer-reviewed human or animal studies demonstrating tumor initiation. The oncogenic risk remains an unverified theoretical concern (Sikirić et al., 2014). | Level D | Speculative |
| “The FDA shut down BPC-157 trials because the drug was too dangerous.” | Noted BPC-157 was never registered under a US IND; early European trials stalled due to corporate mergers (Pliva), not regulatory bans. | Clinical trial registries show no US FDA-directed trial terminations for BPC-157. The compound never progressed through formal US regulatory review pipelines (Emerging Use of BPC-157, 2025). | Level E | Unsupported (Claim refuted) |
| “Melanotan II caused a death in a Phase 2 clinical trial.” | Stated Clinuvel halted development due to systemic blood pressure elevation and off-target melanocortin-mediated sustained penile erections. | Phase 1/2 melanotan studies observed transient mean arterial pressure increases and prolonged erections via central MC4R stimulation; no clinical trial fatalities are documented in published literature (Hadley et al., 2000). | Level B | Unsupported (Claim refuted) |
| “IV anti-amyloid Alzheimer’s drugs are peptides.” | Clarified aducanumab and lecanemab are ~150 kDa monoclonal antibodies (~1,300 amino acids), structurally distinct from small peptides. | Monoclonal antibodies are complex tetrameric immunoglobulins produced via mammalian cell culture, distinct from chemically synthesized short-chain peptides (van Dyck et al., 2023). | Level A | Unsupported (Claim refuted) |
| “FDA removed BPC-157 from Category 2 due to lack of supported safety risk data.” | Stated nominations were withdrawn by original nominators on April 22, 2026, leading to removal from active Category 2 restrictions. | FDA compounding lists confirm removal of BPC-157 from Category 2 following nominator withdrawal, though it remains unapproved for standard 503A compounding without an official USP monograph (FDA Compounding Update, 2026). | Level C | Strong Support |
| “Gray-market peptide products carry high contamination and dosage failure risks.” | Cited independent analytical laboratory testing showing high rates of incorrect concentration and impurity in unregulated peptides. | Chemical analyses of research-chemical peptide products regularly demonstrate variable API concentration, missed reconstitution targets, and presence of bacterial endotoxins (McGuire et al., 2025). | Level C | Strong Support |
Actionable Protocol (Prioritized)
High Confidence Tier (Level A/B Evidence)
| Domain | Clinical Action | Dosing / Target | Primary Endpoint |
|---|---|---|---|
| Metabolic Optimization | Subcutaneous GLP-1 receptor agonist administration (SELECT, 2023) | Semaglutide titrated to 2.4 mg SQ weekly or Tirzepatide titrated to 5–15 mg SQ weekly | Reduction in Major Adverse Cardiovascular Events (MACE), reduction in HbA1c, and sustained weight loss |
| Endocrine Regulation | Recombinant Parathyroid Hormone Fragment [1-34] administration (Neer et al., 2001) | Teriparatide 20 mcg SQ daily | Significant increase in bone mineral density (BMD) and reduction in vertebral fracture risk |
| Physiological Angiogenesis | Structured resistance and aerobic cardiovascular exercise protocol | ≥150 minutes zone 2 aerobic base + 3 weekly resistance sessions | Optimized capillary density, microvascular blood flow, and endogenous VEGF/eNOS activation |
Experimental Tier (Level C/D Evidence - High Safety Margin)
- Pentadecapeptide BPC-157 Protocol Evaluation: Preclinical data suggests dosing of 250–500 mcg administered subcutaneously once or twice daily targeting localized soft-tissue repair. Mechanistically acts by upregulating VEGFR2 phosphorylation, modulating FAK-paxillin signaling, and stimulating fibroblast proliferation. Clinical monitoring mandates baseline metabolic panels, inflammatory biomarkers (hs-CRP), and complete avoidance in individuals with active malignancies or high genetic oncogenic risk.
- Thymosin Beta-4 / TB-500 Repair Assessment: Investigational tissue regeneration protocols describe administration of 2.0–5.0 mg subcutaneously weekly in split doses. Operates via G-actin sequestration, accelerating keratinocyte and endothelial cell migration to ischemic tissue sites. Clinical monitoring requires continuous hepatic and renal metabolic evaluation due to an absence of long-term human safety cohorts.
- Melanocortin Receptor Agonist (PT-141 / Bremelanotide): Subcutaneous administration of 1.75 mg as needed for hypoactive sexual desire disorder via central melanocortin-4 receptor (MC4R) activation. Bypasses peripheral vasculature while avoiding the pigmentary stimulation of Melanotan II. Clinical monitoring requires intermittent ambulatory blood pressure surveillance due to documented transient post-injection pressor responses.
Red Flag Zone (Debunked, High-Risk, or Contraindicated)
Unregulated Gray-Market “Research Chemical” Peptides: Completely contraindicated for human parenteral use. Independent mass spectrometry profiling of unverified online peptide vendors reveals high rates of API mislabeling, variable vial dosages, chemical degradation, and endotoxin contamination. Administering non-sterile, non-cGMP peptides introduces severe risks of aseptic abscess formation, systemic septicemia, and immunogenic anti-drug antibody responses.
Unmonitored Melanotan II Utilization: Highly discouraged due to broad, unselective melanocortin receptor (MC1R, MC3R, MC4R, MC5R) activation. Clinical risks include uncontrolled systemic hypertension, renal injury secondary to rhabdomyolysis, dysplastic nevus progression, and prolonged, refractory priapism requiring urgent urological decompression.
Produced by Gemini 2.5 Pro