Mike Lustgarten Video Series

People, let me know what you prefer when it comes to video transcripts and paper analyses (see above examples):

Do you prefer:

  • Transcription with moderate skepticism
  • Transcript with extremely high skepticism

0 voters

I think it would be interesting if you fed the critique I posted to your ai and see what the response is. Please post response here if you do.

Here is the Gemini Flash 3.5 Enhanced Thinking mode analysis of your previous post here: Mike Lustgarten Video Series - #30 by none

What LLM and version were you using (free or paid)?

Peer-Review and Biotech Intelligence Report: Evaluation of the Third-Party Critique

I. Executive Summary

This report provides an objective peer-review and biotech analysis of a third-party evaluation that critiqued our prior immunometabolic analysis of the conversation between Dr. Dan Winer and Dr. Mike Lustgarten. Operating as an elite analyst for a high-impact medical journal, the objective is to determine the scientific validity of the third-party critique, isolate verified clinical facts, and establish an accurate therapeutic protocol.

The third-party evaluator performs a vital corrective function by identifying a major translational gap: the over-extrapolation of animal data into human longevity prescriptions. The critique correctly challenges several highly speculative clinical protocols that lack human dose-finding evidence, such as utilizing functional mushrooms to directly repair the intestinal wall via NAD+ upregulation, or treating the combination of 2,000 IU Vitamin D and 1 g Omega-3 as a clinically validated anti-aging prescription. It accurately classifies the recommended mega-dosing of cruciferous vegetables and unvalidated indole-to-indoxyl sulfate diagnostic ratios as speculative or unsupported by human randomized controlled trials (RCTs). Furthermore, the critique appropriately tempers the alarmist rhetoric often found in longevity media, replacing directives like “absolute elimination” of food additives with a more nuanced understanding of inter-individual microbiome heterogeneity.

However, the third-party review fails as a definitive adversarial audit due to a severe failure in basic data verification. The evaluator incorrectly labels the claim of a 35% lifespan extension from mature B-cell ablation as a “potentially hallucinated or seriously distorted claim.” This accusation is completely false. A review of the raw transcript reveals that Dr. Winer explicitly cites a 35% lifespan extension observed in his laboratory’s female B-cell-deficient mice. More critically, this pre-clinical breakthrough was formally published by Winer’s group in January 2026 (Science Immunology), demonstrating that B-cell deletion preserves naive CD4+ T-cell pools and extends median mammalian lifespan by 36%. While the third-party evaluator is correct that broad B-cell depletion cannot be safely used as a human lifestyle intervention, falsely dismissing an explicit transcript statement and published study as an AI hallucination severely undermines their credibility. Ultimately, the scientific reality lies between the two analyses: the molecular pathways linking gut dysbiosis to systemic inflammaging are robustly mapped, but translating these pathways into clinical protocols remains limited by a lack of human clinical trials and complex baseline microbiome variations, as demonstrated by recent April 2026 human RCT data on emulsifiers.


II. Insight Bullets

  • The third-party critique provides a necessary clinical correction by separating broad public health consensus from unvalidated mechanistic longevity protocols.
  • Modifying baseline variables like ultra-processed foods, processed meat, and exercise is validated by extensive human cohort studies rather than narrow gut-immune pathways alone.
  • The critique highlights a major translational gap in longevity reporting: treating highly controlled animal findings as established human facts.
  • There is a complete lack of human dose-finding trials supporting the daily ingestion of 250–500 grams of cruciferous vegetables to induce protective IL-22 tissue repair.
  • The third-party reviewer correctly flags the “indole-to-indoxyl-sulfate ratio” as an unvalidated clinical biomarker for monitoring intestinal oxygen tension or short-chain fatty acid (SCFA) concentrations.
  • No human clinical trials validate the claim that functional mushrooms directly repair the intestinal wall through the upregulation of host NAD+ synthesis.
  • Combining 2,000 IU of Vitamin D and 1 gram of Omega-3 fatty acids lacks definitive Level A systematic review data showing it acts as a validated anti-aging prescription.
  • The critique correctly challenges alarmist language such as “destruction” and “absolute elimination” regarding minor adjustments to dietary additives.
  • The reviewer’s accusation that the “35% lifespan extension from mature B-cell ablation” is an AI hallucination is factually incorrect and represents a failure to audit the raw video transcript.
  • Dr. Winer explicitly stated at timestamp that his lab’s female B-cell-deficient mice exhibited a 35% increased lifespan, which was one of the largest extensions he had ever observed.
  • The 35% longevity metric is fully verified by peer-reviewed literature published by Dr. Winer’s group in Science Immunology in January 2026.
  • The January 2026 UHN study confirmed that mice lacking B cells displayed significant improvements in healthspan and median lifespan by protecting naive CD4+ T cells from immunosenescence.
  • The 2026 study discovered that B-cell intrinsic insulin receptor signaling promotes adaptive CD4+ T-cell decay via major histocompatibility complex class II (MHC-II) pathways.
  • Despite the pre-clinical accuracy of the B-cell data, the third-party reviewer is correct that treating broad B-cell depletion as a safe “calorie-restriction mimetic” in humans is highly misleading and presents severe safety risks.
  • The third-party critique accurately positions the avoidance of carboxymethyl cellulose (CMC) and polysorbate-80 as “plausible but unproven” for reducing systemic human inflammation.
  • A breakthrough double-blind human RCT published in Clinical Gastroenterology and Hepatology in April 2026 demonstrated that dietary emulsifiers (CMC, P80) lower essential gut metabolites like short-chain fatty acids.
  • The April 2026 human RCT confirmed that despite reducing fecal SCFAs, emulsifiers did not increase markers of intestinal or systemic inflammation (fecal calprotectin, CRP, or serum proteomic cytokines) over 4 weeks in healthy adults.
  • The critique correctly implies that individual additive sensitivity is non-uniform, as demonstrated by 2026 evidence showing highly heterogeneous host responses to dietary emulsifiers based on baseline microbiome variations.
  • Replacing dietary sucrose with artificial sweeteners like sucralose drives significant taxonomic shifts primarily in diabetic sub-cohorts rather than universally across all healthy individuals.
  • The reviewer is correct that synthetic azo food dyes like Red 40 induce IL-23-mediated colitis almost exclusively in genetically engineered, immunologically vulnerable mouse models, creating a stark translational gap.
  • Food-grade titanium dioxide (E171) nanoparticle pathobiology is robustly validated for causing microflora dysbiosis and mucus layer degradation, supporting its clinical exclusion despite a lack of direct human longevity data.
  • The third-party analysis correctly notes that increasing dietary fiber does not universally generate multi-fold increases in human fecal SCFAs or plasma levels due to baseline human microflora heterogeneity.
  • Human data from 2025-2026 reveal a “personalization bottleneck” where baseline microbiome profiles determine an individual’s capacity to convert prebiotic inputs into protective volatile fatty acids.
  • The critique properly challenges the rigid recommendation that inulin should “never be used unless the rest of the diet is corrected,” noting it ignores individualized nutritional ecology.
  • Preclinical alerts linking prebiotic fiber to liver cancer are highly restricted to specific dysbiotic, cholestatic mouse models and lack human cohort corroboration.
  • The critique is correct that D-lactate cannot be categorized as an “established human metabolic toxin requiring clinical intervention” during normal chronological aging.
  • Elevated D-lactate pathobiology remains clinically verified primarily in short-bowel syndrome and acute metabolic acidosis, not standard human longevity optimization.
  • The reviewer exposes the systemic error of converting statistical or observational associations into definitive causal statements within longevity marketing.
  • The critique confirms that individual avoidance of specific food additives is highly unlikely to alter the trajectory of systemic biological aging on its own.
  • The critique validates the primary scientific backbone of the original text regarding intestinal immune-metabolic interactions and epithelial physiology.
  • The review underscores that mechanistic plausibility does not equal clinical efficacy, a foundational rule of high-impact medical peer review.
  • The critique highlights the necessity of using clear evidence grading scales (Level A through E) to protect patients from unvalidated therapeutic prescriptions.
  • The third-party evaluation serves as an essential corrective lens, enforcing clinical realism onto highly complex, pre-clinical immunometabolic geroscience pathways.
  • True clinical advancement requires moving past single-variable animal diets and utilizing human multi-omic testing to map immune responses to specific dietary patterns.
  • While lifestyle and dietary adjustments optimize healthspan parameters, they do not mirror the extreme longevity extensions achieved through target-specific gene deletions in laboratory animals.

III. Adversarial Claims & Evidence Table

Claim from Video / Original Post Third-Party’s Critique Scientific Reality & Live Search Verification (2022-2026) Evidence Grade (A-E) Verdict
Mature B-cell ablation drives a 35% to 36% increase in median mammalian lifespan. Claims this is a “potentially hallucinated or seriously distorted claim” by the AI. Critique is completely incorrect. Dr. Winer explicitly cites this from his lab’s data. A landmark January 2026 study from Winer’s group at UHN (UHN Research, 2026; Khan et al., 2026) verified that B cell-deficient mouse models show preserved naive CD4+ T-cell pools, reduced frailty, and a 36% median lifespan increase. Level D (Pre-clinical; Translational Gap for humans) Strong Support (as a pre-clinical fact; the third-party critique failed to verify the transcript and primary literature).
Measuring the indole-to-indoxyl-sulfate ratio serves as a validated clinical marker for gut hypoxia and SCFA production. Classifies this as unsupported and misleading for human application. Critique is correct. While intestinal epithelial cells consume luminal oxygen via mitochondrial beta-oxidation of SCFAs, the use of serum or fecal indole-to-indoxyl-sulfate ratios to quantify this specific process is a non-validated mechanistic hypothesis. Source unverified in live search as a clinical diagnostic standard. Level E (Expert Hypothesis / Speculation) Unsupported (as an established human diagnostic biomarker).
Dietary D-lactate is an established human metabolic toxin requiring clinical intervention to prevent aging. Argues that D-lactate is not an established human metabolic toxin in general aging cohorts. Critique is correct. High concentrations of microbially derived D-lactate induce mitochondrial ROS and hepatic Kupffer cell activation in specific obese murine models. However, in human clinical medicine, D-lactic acidosis is a recognized pathology restricted to short-bowel syndrome, not a validated biomarker for standard chronological aging. Source unverified in live search as a universal aging biomarker. Level C / Level D (Human Observational + Pre-clinical) Speculative (Translational Gap; its role as a universal aging toxin is an over-extrapolation).
Functional mushrooms upregulate host NAD+ and directly repair the intestinal wall. Classifies this intervention as unsupported and misleading. Critique is correct. While specific dietary mushrooms contain nicotinic acid (an NAD+ precursor) and polyamines (spermidine) that support cell proliferation, direct human RCT data demonstrating that mushroom ingestion repairs the gut barrier via explicit NAD+ upregulation are non-existent. Source unverified in live search for human clinical trials matching this specific mechanism. Level E (Expert Opinion / Mechanistic Plausibility) Unsupported (for the specific clinical claim).
Combining 2,000 IU Vitamin D and 1 g Omega-3 is a validated anti-aging prescription that slows biological clocks. Rejects this as a proven, validated anti-aging prescription. Critique is correct. While secondary analyses of large-scale trials (such as the VITAL or DO-HEALTH studies) note nominal improvements in specific DNA methylation clocks or localized immune markers when lifestyle factors are optimized, there is no Level A meta-analysis validating this specific combination as a human anti-aging prescription (VITAL Substudy, 2024). Level B (Human RCT with mixed endpoints) Plausible (for minor biomarker modulation, but Speculative as a validated clinical anti-aging therapy).
Dietary Emulsifiers (CMC, P80) trigger direct human intestinal and systemic inflammation. Implies that absolute elimination based on acute inflammatory tracking is unproven in healthy humans. Critique is correct. A robust double-blind human RCT published in April 2026 (Wellens et al., 2026) demonstrated that while CMC and P80 significantly lowered fecal short-chain fatty acids, they did not elevate markers of intestinal or systemic inflammation (fecal calprotectin, C-reactive protein, or serum proteomic cytokines) over 4 weeks in healthy human adults. Level B (Human RCT) Plausible (for SCFA reduction), but Unsupported (for acute inflammatory activation in healthy cohorts over short timelines).

IV. Actionable Protocol (Prioritized)

1. High Confidence Tier (Backed by Level A/B Evidence)

  • Epidemiological Dietary Baseline: Prioritize a diet focused on minimally processed, whole foods while restricting heavy intake of ultra-processed meats. This reduces the systemic exposure to advanced glycation end-products (AGEs) and preserves baseline metabolic homeostasis.
  • Regular Physical Exercise: Implement a structured cardiovascular and resistance training protocol (such as high-intensity interval training or rucking) to lower systemic insulin resistance, improve VO2 max, and naturally optimize colonic transit time.
  • Controlled Omega-3 & Vitamin D Co-Ingestion: Supplement with 1,000 mg/day of high-purity EPA/DHA and 1,000–2,000 IU/day of Vitamin D3 to support general immune function. Maintain serum 25(OH)D levels between 40–60 ng/mL through annual clinical blood chemistry monitoring. Do not treat this combination as a guaranteed lifespan-extension therapy.

2. Experimental Tier (Backed by Level C/D Evidence; High Safety Margin)

  • Whole-Food Soluble Fiber Integration: Target 25–35 grams of soluble fiber daily (utilizing whole foods like oats, chicory, and legumes) to provide substrates for microbial SCFA production, titrated slowly based on individual gastrointestinal tolerance.
  • Cruciferous AhR Agonist Consumption: Incorporate standard dietary portions (100–200 grams daily) of broccoli, Brussels sprouts, or cabbage to introduce indole-3-carbinol, supporting localized Aryl Hydrocarbon Receptor (AhR) pathways and mucosal repair.
  • Additive and Nanoparticle Risk Mitigation: Minimize exposure to food items containing titanium dioxide (E171), carboxymethyl cellulose (CMC), and polysorbate 80. This protects the intestinal mucus layer and prevents alterations in microbial community structures, even if these additives have not been proven to directly drive systemic human inflammaging.

3. Red Flag Zone (Debunked, Destructive, or Safety Data Absent)

  • Therapeutic B-Cell Ablation Banned: Do not attempt clinical translation of mature B-cell depletion protocols (such as off-label anti-CD20 therapies) for longevity purposes. While pre-clinical μMT models show a 36% lifespan expansion, human systemic B-cell ablation causes severe, potentially fatal immunodeficiency.
  • Avoidance of Isolated High-Dose Inulin Megadosing: Avoid adding massive quantities of isolated inulin powder into a highly processed, dysbiotic diet. In specific murine models, isolated inulin loading in the presence of uncorrected dysbiosis can induce severe cholestasis and early-onset liver lesions.
  • Elimination of Vitamin D Megadosing: Exclude unmonitored Vitamin D3 bolus dosing exceeding 10,000 IU/day. Excessive intake can cause hypercalcemia and paradoxically induce localized epithelial cell toxicity, damaging the intestinal wall.

V. Technical Mechanism Breakdown

The third-party review forces a refinement of the validated molecular mechanisms. The following three pathways represent the intersection of pre-clinical geroscience and clinical reality:

1. B-Cell Intrinsic Insulin Signaling and AdaptiveCD4+ T-Cell Immunosenescence

The molecular mechanism underlying Dr. Winer’s 2026 UHN publication details how the adaptive immune system regulates biological aging parameters. Chronological aging drives an increase in insulin receptor (InsR) responsiveness specifically within host B lymphocytes. Upon activation by circulating insulin and glucose, InsR stimulates downstream phosphatidylinositol 3-kinase (PI3K), Akt, and mechanistic target of rapamycin (mTOR) pathways.

This signaling cascade induces hypermetabolism and drives the clonal expansion of age-associated B cells (ABCs), characterized by the expression of CD11c and the transcription factor T-bet. These ABCs exhibit high levels of Major Histocompatibility Complex class II (MHC-II) molecules. ABCs chronically present self-antigens via MHC-II to naive CD4+ helper T cells, driving continuous T-cell activation, cell-cycle exhaustion, and surface PD-1 expression. This process depletes the naive T-cell pool and causes clonal restriction of the T-cell receptor (TCR) repertoire. Removing this B-cell axis preserves a youthful, highly diverse TCR repertoire, extending median lifespan by 36% in pre-clinical models.

2. Emulsifier-Induced SCFA Suppression vs. Inflammatory Activation

As demonstrated by the April 2026 double-blind human RCT, the introduction of industrial emulsifiers like carboxymethyl cellulose (CMC) and polysorbate 80 (P80) disrupts host-microbe metabolic interactions without immediately triggering classic inflammatory tissue responses. Ingested emulsifiers alter the physical state of the intestinal lumen, shifting microflora metabolic processing away from carbohydrate fermentation.

This leads to a uniform down-regulation of genes responsible for synthesis of volatile short-chain fatty acids, resulting in a measurable drop in fecal acetate, butyrate, and propionate concentrations. In pre-clinical murine models, this reduction quickly compromises epithelial barrier integrity, triggering an influx of pro-inflammatory cytokines. However, human clinical reality shows a temporal and threshold gap: in healthy adult cohorts, a 4-week reduction in fecal SCFAs does not stimulate leukocyte recruitment, alter fecal calprotectin, or elevate serum proteomic inflammatory biomarkers, proving that metabolic changes precede measurable clinical tissue inflammation.

3. The Macrophage Glycolytic Bottleneck and Succinate-HIF-1α Locking

In environments characterized by high circulating free saturated fatty acids and glucose, host innate immune cells undergo a metabolic shift toward aerobic glycolysis. This accelerated glycolytic influx creates a distinct bottleneck within the mitochondrial tricarboxylic acid (TCA) cycle. The enzyme succinate dehydrogenase becomes overwhelmed, leading to a accumulation of intracellular succinate.

Excess cytosolic succinate functions as a competitive inhibitor of prolyl hydroxylase domain (PHD) enzymes. Under normal conditions, PHD enzymes hydroxylate Hypoxia-Inducible Factor 1-alpha (HIF-1α) to mark it for rapid proteasomal destruction. By blocking PHD activity, accumulated succinate stabilizes and locks HIF-1α in an active state. Stable HIF-1α moves to the nucleus and binds directly to the promoter region of the IL1B gene, driving continuous transcription and translation of pro-inflammatory IL-1β, which systematically jams downstream tyrosine phosphorylation of peripheral insulin receptors.

1 Like

Chatgpt 5.5, $20/month.

I won’t post any more critiques, promise.

Both prompts are great! The more adversarial and skeptical the better + possible actions is nice also.
It would be cool if someone could upload them to Youtube with an AI voice over.
Or some AI character really giving it a go esp if it’s a failing grade.
Dr. (whoever) or random grifter vs Gemini AI w/ 100% skepticism.

It’s not a problem… it’s a good discussion to have.

Where exactly to dial in the skepticism is a tough problem for all of us, and one I’m still grappling with; too skeptical and all that you’ll be doing is exercising and eating “healthy” for the next 20 to 30 years until long term, human double blind, placebo-controlled studies are done on all our favorite compounds. But too open to new compounds and you’ll have a stack of 200 daily supplements and drugs at a cost of $1,000s per month.

It’s easy to be critical and negative - and dismiss the entire longevity field as overzealous commercialism and hype. Our goal here is to parse out the junk and identify the highest probability therapeutic approaches… and its not an easy task (and everyone will likely have a slightly different opinion, given their risk/reward profile, age, income, etc.).

We’re also all just figuring out how to manage these LLMs so that they reduce the error rates… as they progress quickly. And it’s interesting to have a different LLM’s perspective. I’m currently using both Google Gemini and Claude paid versions. It’s interesting to get the perspective of CGPT now. Below is my analytical, high skepticism prompt for analyzing video transcripts. If you get anything significantly different on CGPT from what I get on Gemini or Claude, please let us know.

Video Transcript Analysis Prompt (Higher skepticism/more analytical):

2 Likes

Vascular Control Of Aging And Regeneration (Featuring Anjali Kusumbe, PhD)

I. Executive Summary

Vascular and lymphatic networks within the skeletal system are not merely passive conduits for nutrient transport, but active microenvironments that govern organ development, hematopoiesis, and structural remodeling through angiocrine and lymphangiocrine signaling. Dr. Anjali Kusumbe’s research group has revolutionized skeletal biology by introducing an ultra-fast, 3.5-day tissue-clearing and immunolabeling technique coupled with high-resolution 3D light-sheet microscopy. This methodology has successfully overturned the classic medical dogma that bone tissue completely lacks an internal lymphatic network, revealing instead a dense system of LYVE1+ and PROX1+ lymphatic endothelial cells penetrating deep within human and murine cortical bone and marrow spaces.

Following fracture or genotoxic injury, these lymphatic networks rapidly expand via IL-6 and VEGF-C/VEGFR-3 signaling pathways to secrete CXCL12. This lymphangiocrine cascade triggers the activation of Myh11+ CXCR4+ pericytes, driving their differentiation into functional bone-forming osteoblasts while simultaneously coordinating hematopoietic stem cell regeneration. Chronological aging compromises this axis; aged lymphatic endothelial cells exhibit an intrinsic senescent phenotype, losing their proliferative capacity and failing to initiate homeostatic repair pathways after injury.

Furthermore, multi-omic analyses—including single-cell RNA sequencing and unbiased proteomics—directly challenge previous high-profile hypotheses asserting that the skull bone marrow is a resilient vascular reservoir that expands during senescence. Dr. Kusumbe demonstrates that previous findings were the artifactual product of non-cleared, depth-limited confocal imaging, confirming that the calvarium experiences profound age-related endothelial and mesenchymal depletion, chronic inflammation, DNA replication stress, and telomeric down-regulation.

Crucially, skeletal aging is highly compartmentalized; distinct bones follow entirely unique aging trajectories. While the calvarium displays a fragile, degenerating phenotype, proteomic profiles show that the vertebrae are relatively protected, maintaining superior mitochondrial activity and lower genotoxic stress markers during advanced age. Therapeutic attempts to rescue skeletal aging using non-specific growth factors like VEGF carry high risks of systemic hypervascularization or pathological bone osteolysis. Reversing age-dependent skeletal decline requires the identification of organ-specific vascular molecular keys to selectively drive bone angiogenesis and lymphangiogenesis. Lifestyle interventions, such as high-impact loading and resistance exercise, promote transient bone mineral density via mechanical fluid shear stress, but cannot halt or reverse the autonomous cellular senescence occurring within the specialized bone vascular niche.
II. Insight Bullets

  1. Active Role of the Skeletal Vasculature: Blood and lymphatic networks in bone extend beyond structural transport tubes; endothelial cells and pericytes dictate organ development, stem cell maintenance, tissue repair, and inflammation resolution.
  2. Mechanisms of Angiocrine Signaling: Endothelial cells actively regulate the fate, proliferation, and behavior of neighboring hematopoietic and skeletal stem cells through specialized juxtacrine and paracrine cross-talk.
  3. The Capillary Stem Cell Niche: Micro-capillaries within the bone marrow build essential physical niches that protect and sustain blood-forming hematopoietic stem cells and bone-forming skeletal stem cells.
  4. Skeletal Lineage Commitment: Skeletal stem cells nested adjacent to specialized microvessels undergo lineage-specific differentiation into chondrocytes (cartilage), osteoblasts (bone), and adipocytes (fat).
  5. Age-Related Loss of Bone Plasticity: Although bone exhibits high remodeling and fracture-healing capacities in youth, chronological aging drives severe functional declines, increasing the incidence of non-reunion fractures and bone marrow transplantation failures.
  6. Flaws in Traditional Histological Decalcification: Conventional bone imaging is heavily restricted because harsh, acidic decalcification protocols structurally alter tissues and destroy antibody binding sites, rendering high-resolution immunolabeling impossible.
  7. Development of Rapid Tissue Clearing: Dr. Kusumbe’s lab engineered an ultra-fast, 3.5-day clearing and less harsh decalcification protocol that preserves antibody integrity and renders opaque mammalian bone entirely transparent.
  8. Shift to 3D Light-Sheet Paradigms: Intact, cleared skeletal tissues are mapped using 3D light-sheet microscopy, completely bypassing the strict physical depth limitations and spatial distortions of standard 2D sectioning and confocal imaging.
  9. Validation in Human Biopsies: The 3.5-day clearing and high-resolution immunolabeling methodology is fully translatable to human medicine, successfully visualizing the complex 3D microarchitecture of human bone biopsies.
  10. Overturning Anatomical Dogma: High-resolution 3D maps conclusively disprove the long-held medical consensus that bone is an isolated organ devoid of an intrinsic lymphatic vascular system.
  11. Identification of Deep Bone Lymphatics: Intact imaging identifies distinct tubular networks expressing Lymphatic Vessel Endothelial Hyaluronan Receptor 1 (LYVE1) penetrating through the cortical bone shell deep into the marrow cavity Biswas, Chen et al., 2023.
  12. Exclusion of Macrophage Artifacts: True lymphatic identity within bone marrow was confirmed by combining LYVE1 markers with specific macrophage-excluding antibodies to prevent false-positive structural mapping.
  13. Genetic Confirmation of Lymphatic Endothelium: Cross-referencing public single-cell transcriptomic databases verifies that bone marrow lymphatic endothelial cells express canonical lymphatic identity markers, including Flt4 (VEGFR3) and Prox1.
  14. The Regulatory Role of PROX1: Prospero Homeobox 1 (PROX1) operates as the master transcription factor within the bone marrow vascular niche, dictating the identity and functional differentiation of the lymphatic lineage.
  15. Genotoxic and Mechanical Stress Responses: Exposing skeletal tissue to radiation injury or physical fractures triggers an immediate, rapid proliferative expansion of localized bone lymphatic vessels.
  16. The Lymphangiocrine Signaling Cascade: Upon injury activation, proliferating lymphatic endothelial cells upregulate and secrete high concentrations of C-X-C Motif Chemokine Ligand 12 (CXCL12), a key homeostatic cytokine required for niche recovery.
  17. Dual Functional Support of CXCL12: Lymphangiocrine-derived CXCL12 concurrently drives the cellular regeneration of hematopoietic stem cell pools and accelerates structural bone healing.
  18. Pericyte Activation and Recruitment: Secreted CXCL12 binds to CXCR4 receptors on mature Myh11+ perivascular pericytes, forcing their rapid expansion and subsequent differentiation into osteoblasts to replace damaged bone.
  19. Intrinsic Senescence of Aged Lymphatics: In chronologically aged organisms, lymphatic endothelial cells enter a profound state of cellular senescence, completely losing their ability to proliferate or secrete CXCL12 in response to fracture or radiation stress.
  20. Debunking the Resilient Skull Paradigm: Dr. Kusumbe’s multi-laboratory data directly refutes a previous high-profile study asserting that the skull bone marrow vasculature uniquely expands with age and remains a resilient, aging-protected hematopoietic reservoir.
  21. Identification of Confocal Optical Artifacts: The disputed “resilient skull” model was shown to suffer from significant optical artifacts, including the false localization of the cell-surface marker endomucin inside cell nuclei due to depth limitations of non-cleared confocal microscopy.
  22. The Fragile Trajectory of Calvarial Aging: True 3D tracking using cleared tissue and single-cell RNA-seq proves that calvarial (skull) bone marrow undergoes aggressive age-related vascular, mesenchymal, and osteoprogenitor cell depletion.
  23. Proteomic Signatures of Skull Degeneration: Unbiased proteomic profiling reveals that the aged calvarium experiences severe DNA replication stress, negative regulation of telomere maintenance, diminished mitochondrial respiration, and a pro-inflammatory secretory shift.
  24. Compartmentalization of Skeletal Decay: Skeletal aging is not a uniform, systemic process; different bones across the body age along entirely separate cellular trajectories and at highly variable rates.
  25. Vertebral Protection from Aging Hallmarks: Comparative proteomics demonstrates that the vertebrae (vertebral red bone marrow) are relatively protected from age-induced degeneration, retaining significantly higher mitochondrial activity and lower genotoxic stress profiles than the skull or long bones.
  26. Emergency Organ-Specific Immune Delivery: Cranial and thoracic bone marrows act as highly compartmentalized, localized emergency response centers; for example, the skull marrow rapidly delivers specialized immune cells directly to the brain during a stroke, while the sternum responds to myocardial infarction.
  27. Intra-Skull Structural Heterogeneity: The calvarium (skull cap) exhibits completely different vascular properties and accelerated aging dynamics compared to the mandible (jawbone).
  28. Mechanical Preservation of Jaw Density: The continuous high mechanical load of chewing provides a unique osteogenic stimulus that selectively preserves jawbone density during aging, an effect completely missing in the non-weightbearing upper skull.
  29. Cosmetic Implications of Osteodegeneration: The physical development of facial sagging and altered structural appearance during human aging is fundamentally driven by deep age-dependent facial bone thinning and bone mass loss.
  30. The Danger of Non-Specific Angiogenic Therapeutics: Systemic administration of generalized growth factors like Vascular Endothelial Growth Factor (VEGF) is clinically dangerous, carrying high safety risks of inducing multi-organ pathological vascularization, tumor promotion, or localized bone degradation.
  31. The Pathological Pericyte-to-Fibroblast Transition: Age-induced senescence of the bone endothelium disrupts critical cell-surface survival interactions with adjacent pericytes, causing pericytes to aberrantly differentiate into fibroblasts.
  32. Marrow Fibrosis Induction: The uncontrolled transition of pericytes into a fibroblastic state represents the core molecular driver behind age-associated bone marrow fibrosis and subsequent skeletal failure.
  33. The Theoretical Anti-Microbial Defense Debate: A current geroscience hypothesis considers whether the pericyte-to-fibroblast transition represents an evolutionary trade-off, where fibroblasts multiply to execute localized anti-microbial defense against rising systemic pathogen burdens at the cost of chronic tissue fibrosis.
  34. The Search for Bone-Specific Vascular Keys: Current translational research is focused on sequencing comprehensive organ-specific vascular atlases to isolate unique endothelial molecular targets, allowing clinicians to selectively stimulate bone vascular regeneration without altering systemic circulation.
  35. The Ceiling Effect of Lifestyle Interventions: While resistance exercise and high-impact mechanical loading successfully trigger fluid shear stress and transiently increase bone mineral density in human trials, these interventions are insufficient to halt or reverse the autonomous cellular senescence of the deep vascular and lymphatic niches.
  36. Critical Knowledge Gaps in Geroscience: Extensive experimental data is currently lacking regarding isolated mitochondrial respiratory kinetics and comprehensive metabolomic profiles across distinct regional skeletal beds, highlighting a major barrier to designing targeted longevity compounds.

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Evidence)

  • Indication: Maximizing localized bone mineral density (BMD) and stimulating mechanical fluid shear stress pathways to support skeletal geometry.
  • Protocol Parameters: Execution of high-load dynamic resistance training combined with short-duration high-impact loading (e.g., progressive heavy weightlifting or sprint training). Human clinical trials and meta-analyses establish that high adherence to structured mechanical loading protocols yields statistically superior bone preservation compared to low-intensity or non-weightbearing exercise Shojaa et al., 2020; Wei et al., 2023.
  • Translational Nuance: This protocol successfully optimizes the mechanical axes of bone modeling and upregulates generalized osteogenic growth factors at loaded sites (e.g., femur, tibia, lumbar spine). However, it operates under a clear physiological ceiling: mechanical loading cannot arrest or reverse the intrinsic, genetically programmed cellular senescence occurring within the endothelial and lymphatic microenvironments of the bone marrow niche [Gruber et al. - Source unverified in live search].
1 Like

HDL Was 28, Now It’s Optimal: How I Did It

I. Executive Summary

Mike Lustgarten’s quantitative tracking workflow challenges traditional, reductionist models of lipid panel interpretation. Rather than viewing high-density lipoprotein cholesterol (HDL-C) through the outdated clinical lens of “higher is inherently better,” large-scale epidemiological dataset analysis involving 15.8 million individuals demonstrates a strict, non-linear U-shaped relationship with all-cause mortality hazards. Systemic risk elevates significantly when serum HDL-C concentrations drop below 50 mg/dL or ascend above 69 mg/dL, establishing an optimal survival nadir precisely bounded between 50 and 69 mg/dL.

To manipulate and stabilize this biomarker within its optimal metabolic window, Lustgarten deployed a longitudinal, N=1 quantitative tracking protocol encompassing 73 sequential blood tests across an 11-year timeline. By pairing precise digital kitchen-scale measurements of 99% of all solid and liquid food intake with specific blood draw dates, he calculated mathematical rolling-average exposure intervals to isolate true biological drivers from baseline statistical noise.

The analytical results demonstrate that circulating HDL-C is not an unmodifiable, genetically predetermined metric but a highly dynamic variable responsive to distinct metabolic inputs. A univariate analysis identified waking body weight as the dominant negative physiological driver, explaining 56% of total phenotypic HDL-C variance independently (r = -0.75, p = 2e-13). Total daily caloric intake was also identified as a significant negative correlate (r = -0.44, p < 0.05). When these parameters are combined into an ordinary least squares multivariate linear regression model alongside specific dietary inputs, a four-variable matrix—comprising daily caloric intake, waking body weight, saturated fatty acid (SFA) load, and raw ginger consumption—explains 81% of absolute HDL-C variance (Adjusted R-squared = 0.81, Significance F = 2e-17).

By applying these individual beta coefficients against a static intercept of 165.9, this architecture transitions biomarker tracking from passive, retrospective observation into active predictive forecasting. This personalized optimization protocol successfully shifted a pathological baseline average of 36 mg/dL (with a clinical nadir of 28 mg/dL) up to a regulated, survival-optimized average of 58 mg/dL.

II. Insight Bullets

  • Non-Linear All-Cause Mortality Curve: High-density lipoprotein cholesterol (HDL-C) displays a distinct U-shaped correlation with all-cause mortality risk, refuting historical linear assumptions.
  • The Survival Nadir: Absolute hazard ratios for all-cause mortality reach their lowest statistical threshold within a strict serum concentration window of 50 to 69 mg/dL.
  • High-End Cardiovascular Risk: Serum HDL-C values exceeding 70 mg/dL are independently associated with an elevated risk of mortality in both male and female cohorts.
  • Low-End Hazard Escalation: Dips in circulating HDL-C below 50 mg/dL trigger a linear increase in all-cause mortality hazards.
  • Chronological Biomarker Atrophy: Large longitudinal tracking datasets confirm that baseline circulating HDL-C levels typically undergo a steady decline as a function of physiological aging.
  • Malleability of Lipid Profiles: Serial N=1 clinical evidence proves that low baseline HDL-C is highly responsive to lifestyle modifications, demonstrating a shift from 28 mg/dL to 77 mg/dL.
  • High-Frequency Testing Imperative: Separating genuine physiological signals from background analytical noise in personalized medicine requires high-frequency testing (often requiring 20 or more blood panels).
  • Rolling Average Exposure Alignment: Calculating accurate nutritional correlations requires computing the strict mathematical mean of dietary metrics over the exact timeframe between blood draws.
  • Confounding in Two-Sample T-Tests: While a two-sample t-test can compare brief tracking blocks, it introduces high multi-variable confounding when isolating single nutrient drivers.
  • Whole-Food Analytical Superiority: Tracking whole, intact foods as distinct variables represents a less reductionist and more accurate strategy than tracking isolated macronutrients alone.
  • Mass-Based Tracking Compliance: Achieving high-fidelity dietary correlation datasets requires precise mass measurements of up to 99% of all solid and liquid intake via digital scale logging.
  • Body Weight Dominance: Waking body mass acts as the primary univariate predictor of circulating HDL-C levels, dictating 56% of total phenotypic variance.
  • Negative Body Weight Correlation: Lower overall body mass measurements are strongly correlated with elevated serum HDL-C concentrations (r = -0.75, p = 2e-13).
  • Caloric Intake Suppression: Total daily energy intake displays a distinct negative correlation with circulating HDL-C values (r = -0.44, p < 0.05).
  • Bivariate Explanatory Capacity: Merging total caloric intake and body mass into a bivariate linear regression architecture accounts for 60% of absolute HDL-C phenotypic variance.
  • Ordinary Least Squares (OLS) Predictive Forecasting: Utilizing localized beta coefficients derived from long-term OLS models enables precise forecasting of upcoming blood panel values.
  • Saturated Fatty Acid Beta Coefficients: Saturated fatty acid (SFA) intake displays a positive beta coefficient relationship with serum HDL-C when integrated into a multivariate framework.
  • Ginger as a Bioactive Modulator: Daily intake of raw ginger exhibits a highly distinct positive association with circulating HDL-C levels.
  • The Four-Variable Optimization Matrix: Combining total calories, body weight, saturated fatty acids, and ginger maps 81% of total HDL-C variance (Adjusted R-squared = 0.81).
  • Statistical Power of N=1 Architecture: High-frequency testing within a single individual provides exceptional statistical power (Significance F = 2e-17) for personalized longevity protocols.
  • Large Cohort Validation: The U-shaped HDL-C risk curve is validated by large-scale epidemiological data evaluating 15.8 million adult individuals.
  • Reference Range Distinctions: Traditional laboratory reference ranges reflect basic population medians rather than survival-optimized clinical targets.
  • Data-Driven Behavioral Guidance: Maintaining precise tracking infrastructure converts behavioral and nutritional choices from guesswork into real-time empirical adjustments.
  • Integration of Macro and Micronutrients: Concurrent tracking of macro- and micronutrients along with whole food identity yields the highest signal-to-noise ratio for health optimization.
  • Dynamic Response Over Time: Longevity biomarkers remain fluid metrics that can be systematically re-engineered through targeted metabolic switches.

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Evidence)

  • Avoid Targeting Supranormal HDL-C via Therapeutics: Large-scale human randomized controlled trials (RCTs) evaluating CETP inhibitors demonstrate that pharmacologically forcing HDL-C to supranormal levels (>70 mg/dL) fails to lower cardiovascular events and can increase absolute mortality (Lincoff et al., 2017).
  • Maintain Serum HDL-C Inside the 50-69 mg/dL Target Range: Massive multi-million individual prospective cohort studies confirm that the optimal serum HDL-C range to minimize all-cause mortality hazards is strictly between 50 and 69 mg/dL (Shin et al., 2021).

Experimental Tier (Level C/D Evidence)

  • Personalized N=1 OLS Linear Regression Modeling: Deploy continuous software-assisted diet tracking (weighing ≥99% of foods) alongside localized spreadsheets to calculate individual beta coefficients across multiple serial blood draws (minimum 3 to 20 panels) to isolate individual phenotypic drivers.
  • Caloric Restriction and Body Mass Optimization: In individuals tracking low baseline HDL-C, intentional weight loss via modest caloric restriction can be used as a primary lever to elevate HDL-C, leveraging a proven negative biological correlation (r = -0.75).
  • Targeted Saturated Fatty Acid and Ginger Modulation: For individuals mimicking the Lustgarten protocol, combining a steady saturated fatty acid intake (e.g., ~19g/day) with a specific daily dose of raw or powdered ginger (~7g/day) can be explored to optimize the four-variable regression model, provided total LDL-C and ApoB metrics are carefully co-monitored.

Red Flag Zone (Safety Data Absent / Debunked)

  • Blind Supplementation of Saturated Fatty Acids: Elevating saturated fatty acid (SFA) intake to raise HDL-C without tracking ApoB or LDL-C is a major cardiovascular risk. Robust meta-analyses of RCTs prove that replacing SFAs with polyunsaturated fatty acids (PUFAs) lowers true clinical coronary heart disease events, independent of changes to HDL-C (Mozaffarian et al., 2010).

Critical Nutrients For Brain Health: Tommy Wood, MD, PhD

I. Executive Summary

The analyzed discourse outlines a rigorous, data-driven framework linking specific micronutrient status and multi-nutrient metabolic interactions to long-term neurodegeneration and dementia risk. Rather than evaluating dietary or supplemental variables in isolation, the evidence establishes a multi-nutrient synergistic paradigm. Epidemiological meta-analyses firmly demonstrate that isolated vitamin D deficiency and chronic anemia (compromised hemoglobin status) independently and significantly elevate the risk for all-cause dementia and Alzheimer’s disease. When multiple subclinical nutrient deficiencies coexist, they stack to exponentially accelerate neurodegenerative risk.

A primary focus is the metabolic interplay between B-complex vitamins (B12, folate, B6, and riboflavin) and long-chain omega-3 fatty acids (specifically docosahexaenoic acid, or DHA) within the structural methylation pathway. Elevated plasma total homocysteine (tHcy)—a precise functional biomarker of impaired methylation and B-vitamin insufficiency—directly correlates with accelerated brain atrophy and cognitive decline. While randomized controlled trials (RCTs) like the landmark VITACOG study demonstrate that high-dose B-vitamin supplementation slows whole-brain and regional gray matter atrophy in individuals with elevated baseline homocysteine (>13 µmol/L), this therapeutic efficacy is entirely conditional upon baseline omega-3 fatty acid status.

Mechanistically, the incorporation of DHA into neuronal membrane phospholipids is an active biochemical process requiring sequential phosphatidylethanolamine methylation, which is strictly dependent on adequate B-vitamin cofactors. If circulating omega-3 levels are inadequate, B-vitamin administration fails to mitigate structural brain shrinkage or slow cognitive deterioration. This critical dynamic nutrient co-dependency has been replicated across multiple independent clinical trials, including the OmegAD and B-PROOF studies. These findings highlight that mono-nutrient supplementation strategies in the presence of uncorrected co-deficiencies are clinically ineffective, mandating a comprehensive protocol that targets both methylation pathways and structural lipid pools simultaneously to preserve parenchymal brain volume and halt cognitive decline.

II. Insight Bullets

  1. Multi-Nutrient Dementia Association: Long-term dementia risk is heavily driven by baseline status of a distinct cluster of micronutrients: folate, vitamin B12, omega-3 fatty acids, vitamin D, zinc, iron, and choline.
  2. Vitamin D Deficiency Thresholds: Epidemiological meta-analyses establish that serum 25-hydroxyvitamin D [25(OH)D] levels below 50 nmol/L significantly correlate with an increased risk of developing Alzheimer’s disease and all-cause dementia [PMC4522102].
  3. Anemia-Induced Neurodegeneration Risk: Chronic anemia, characterized by low hemoglobin concentrations, independently elevates the risk of all-cause dementia by approximately 39% to 56% across major longitudinal cohorts [PubMed, 37102212].
  4. Cerebral Hypoxia Mechanism: The pathophysiology of anemia-driven cognitive decline is primarily mediated by chronic cerebral hypoxia and oxidative stress, which accelerate white matter hyperintensities and cortical atrophy [PMC13090852].
  5. Synergistic Nutrient Deficiencies: Nutrient deficiencies do not operate in silos; accumulating multiple marginal deficiencies creates a compounding, non-linear acceleration of late-life cognitive impairment risk.
  6. Homocysteine as a Methylation Biomarker: Plasma total homocysteine (tHcy) serves as a sensitive functional indicator of B-vitamin insufficiency (B12, folate, B6, and riboflavin/B2), mapping directly onto systemic methylation status [Life Extension, Source Verified].
  7. B-Vitamin Insufficiency Atrophy: Inadequate levels of vitamin B12 and folate cause structural hyperhomocysteinemia, which directly correlates with accelerated global brain parenchymal atrophy.
  8. The VITACOG Intervention Protocol: The randomized controlled VITACOG trial demonstrated that targeted, high-dose B-vitamin therapy effectively lowers plasma homocysteine by roughly 30% over a 2-year period [PubMed, 21780182].
  9. Homocysteine Stratification Floor: The structural brain-saving benefits of B-vitamin supplementation are highly selective, presenting primarily in individuals with a baseline total homocysteine concentration above 11.3 to 13 µmol/L [PLOS One, Source Verified].
  10. Regional Gray Matter Preservation: High-dose B-vitamin administration in hyperhomocysteinemic subjects slows regional gray matter atrophy by up to 86% in critical regions vulnerable to Alzheimer’s pathology, including the hippocampus.
  11. The Core Omega-3/B-Vitamin Interaction: B-vitamin therapy possesses an absolute therapeutic ceiling: it fails to reduce the rate of brain atrophy or slow cognitive decline in patients with low baseline omega-3 fatty acid levels [Food for the Brain, Source Verified].
  12. DHA Dependent Atrophy Mitigation: The slowing of structural brain shrinkage via homocysteine-lowering therapy is highly correlated with plasma docosahexaenoic acid (DHA) status, requiring high-tier baseline omega-3 concentrations to manifest.
  13. The OmegAD Trial Replication: Data from the OmegAD trial confirmed this direct dependency, proving that omega-3 polyunsaturated fatty acid supplementation yields cognitive benefits strictly in individuals with low or normalized baseline homocysteine levels.
  14. The B-PROOF Trial Confirmation: Post-hoc analysis of the 2-year randomized B-PROOF trial reinforced that the protective effect of folic acid and vitamin B12 on global cognition is entirely dependent on high baseline plasma DHA tertiles [Research@WUR, Source Verified].
  15. Neuronal Phospholipid Synthesis: Mechanistically, DHA must bind to phospholipids via active methylation to be incorporated into neuronal membranes, a process that is entirely bottlenecked by B-vitamin availability.
  16. Failed Mono-Nutrient Supplementation Trials: The strict biochemical co-dependence of structural lipids and methylation cofactors explains why solo omega-3 or isolated B-vitamin clinical trials frequently generate neutral or highly inconsistent outcomes.
  17. Iron Deficiency Neurotransmitter Impairment: Beyond oxygen transportation, inadequate iron status impairs core central nervous system functions by disrupting rate-limiting iron-dependent enzymes essential for neurotransmitter synthesis [PMC8231247].
  18. Alzheimer’s Blood Biomarker Correlation: Anemia in older adults correlates cross-sectionally with elevated serum levels of neurodegenerative biomarkers, including phosphorylated tau 217 (p-tau217), neurofilament light chain (NfL), and glial fibrillary acidic protein (GFAP) [PubMed, 41996117].
  19. Compounded Biomarker Risk: The coexistence of baseline anemia and elevated neurodegenerative blood biomarkers (such as NfL) increases the hazard ratio for incident dementia to an extreme 3.64-fold.
  20. Optimal Methylation Targets: To optimize structural neural membrane integrity, clinical targets must aim for a high omega-3 index alongside a low total homocysteine baseline, ideally below 11 µmol/L, with an ultimate longevity target near 7–8 µmol/L.

IV. Actionable Protocol

High Confidence Tier (Level A/B Evidence)

  • Dual-Nutrient Methylation Co-Optimization Strategy: Never supplement high-dose B-vitamins or long-chain omega-3 fatty acids in isolation without verifying the adequacy of the opposing nutrient. To slow brain atrophy and preserve cognitive function, maintain a plasma total homocysteine level below 11 µmol/L (optimally 7–8 µmol/L) using targeted B-complex factors (methylfolate, methyl-B12, B6) only when paired with an optimized Omega-3 Index (preferably above 8%) or high-dose DHA/EPA administration [PubMed, 21780182; J Alzheimers Dis, 2019].
  • Vitamin D Adequacy Baseline: Maintain serum 25-hydroxyvitamin D [25(OH)D] concentrations safely above 50 nmol/L (optimally 75–125 nmol/L) via calibrated cholecalciferol supplementation and controlled UV exposure to avoid the 21% elevated risk threshold for Alzheimer’s disease pathology [PMC4522102].

Experimental Tier (Level C/D Evidence)

  • Comprehensive Micronutrient Stacking Audit: Periodically audit and correct borderline deficiencies in zinc, choline, riboflavin (B2), and iron to prevent cumulative, multi-nutrient synergistic escalation of dementia risk. Ensure choline intake meets or exceeds optimal thresholds to support the cytidine 5’-diphosphocholine (CDP-choline) pathway for structural phosphatidylcholine synthesis alongside the B-vitamin-dependent methylation pathway [Life Extension, Source Verified].

Red Flag Zone (Debunked or Safety Data Absent Claims)

  • **Isolated High-Homocysteine B-Vitamin Supplementation (Debunked/Therapeutically Ineffective):**Administering high-dose folic acid and vitamin B12 to lower elevated homocysteine in patients with uncorrected, low omega-3/DHA status is clinically debunked. Data from the VITACOG and B-PROOF trials conclusively show a complete absence of structural or cognitive benefit from B-vitamins when structural lipid pools are depleted [Research@WUR, Source Verified].
  • Permissive Management of Subclinical Anemia (High Risk): Treating subclinical anemia or borderline-low hemoglobin concentrations in older adults as a benign aging variant is dangerous. Longitudinal data link low hemoglobin directly to accelerated cerebral cortical shrinkage, white matter hyperintensities, elevated p-tau217, and a 1.39-fold to 1.66-fold jump in incident dementia risk [PubMed, 37102212].

AI And The Future Of Healthspan

I. Executive Summary

This discussion between Dr. Nathan Price (Professor and Co-Director of the Center for Human Healthspan at the Buck Institute for Research on Aging), Dr. Sher Zhang (Co-founder of Healthspan Horizons), and host Dr. Mike Lustgarten examines the transition from reactive sickness care to proactive “Scientific Wellness.” The core thesis asserts that healthspan optimization is fundamentally a computational systems biology problem. While late-stage medical interventions fail because extensive tissue damage has already occurred—exemplified by hundreds of billions of dollars spent on late-stage Alzheimer’s disease therapies with minimal clinical efficacy—up to 45% of dementias are preventable via early multidomain lifestyle interventions (Kivipelto et al., 2015).

Price introduces the “Modifiable Gap” framework, which integrates whole-genome sequencing and polygenic risk scores (PRS) with longitudinal multiomic profiling (metabolomics, proteomics, clinical chemistry, and gut microbiome). The framework establishes that an individual’s genetic architecture defines a baseline prediction floor or ceiling for specific biomarkers (e.g., LDL cholesterol, fasting insulin). The distance between a patient’s measured phenotype and their polygenic prediction represents the modifiable window accessible via lifestyle intervention. Individuals with low polygenic risk for elevated LDL cholesterol show high responsiveness to dietary and lifestyle changes, whereas those in high polygenic risk quintiles demonstrate zero statistically significant lifestyle-driven reduction, requiring targeted pharmacology (Wainberg et al., 2020).

The speakers present longitudinal data from over 3,500 deeply phenotyped individuals demonstrating that healthspan metrics are quantifiable and modifiable. Gut microbiome composition diverges with healthy aging after age 50, characterized by a depletion of core Bacteroides taxa; retaining high Bacteroides dominance into extreme old age predicts decreased 4-year survival (Wilmanski et al., 2021). Furthermore, gut metagenomic profiles fermenting complex carbohydrates into short-chain fatty acids (SCFAs/butyrate) independently predict dietary weight loss success (Diener et al., 2021). To translate these complex interactions into clinical utility, the Buck Institute developed Compass AI—an N-of-1 health intelligence platform utilizing federated AI models, Mahalanobis distance metrics across high-dimensional omic spaces, and environmental exposome tracking. This system quantifies systemic physiological entropy and calculates personalized trade-offs, balancing disease risk mitigation against potential metabolic or endocrine side effects.

II. Insight Bullets

  1. Quantitative Definition of Aging: Aging is defined mathematically as the exponential increase in all-cause mortality hazard over time (Gompertz law), contrasting with inanimate objects (e.g., incandescent lightbulbs) that exhibit constant failure rates.
  2. Economic Pivot toward Healthspan: Economic projections forecast a $2 trillion expenditure shift from end-stage disease management toward proactive health preservation and healthspan extension by 2040.
  3. Preventability of Dementia: Data from the multidomain FINGER trial demonstrate that systematic interventions in diet, exercise, cognitive training, and vascular risk monitoring significantly preserve executive function and prevent up to 45% of non-genetically driven dementias (Kivipelto et al., 2015).
  4. Irreversibility of Late-Stage Neurodegeneration: Late-stage Alzheimer’s drug development yields minimal return on investment because small molecules cannot reconstruct lost neuronal networks; primary intervention must occur decades earlier to maintain cellular energetic health.
  5. Lifespan Heritability: Genomic architecture accounts for an estimated 15% to 50% of human lifespan variance, yet genetic risk profiling remains virtually unutilized in standard primary care medicine.
  6. Contextual Biomarker Interpretation via PRS: Standard clinical biomarkers exhibit differential risk stratification based on genetic context; for example, LDL cholesterol levels show zero correlation with coronary artery disease (CAD) outcomes in individuals with low CAD polygenic risk, but exhibit strong linear predictive power in those with high polygenic risk (Wainberg et al., 2020).
  7. The Modifiable Gap Concept: The numerical delta between a measured blood biomarker and its polygenic risk prediction defines the “modifiable gap”—the specific boundary within which lifestyle and environmental modifications can alter that biomarker.
  8. Differential Lifestyle Responsiveness: Individuals in the lowest genetic risk quintiles for elevated LDL cholesterol achieve significant reductions through lifestyle interventions, whereas those in high polygenic risk quintiles exhibit zero statistically significant lifestyle-driven reduction.
  9. Refinement of Polygenic Variance Models: Modern multi-SNP polygenic models account for over 21% of variance in clinical lipid profiles, allowing precise calculation of lifestyle modifiability versus pharmacological necessity.
  10. Microbiome Uniqueness in Healthy Aging: Beginning around age 50, healthy individuals exhibit progressive gut microbiome compositional divergence (increasing beta-diversity uniqueness), whereas unhealthy individuals retain static, core-dominated microbiomes (Wilmanski et al., 2021).
  11. Survival Prediction via Core Taxa Depletion: Retaining high relative abundance of the core genus Bacteroidesbeyond age 80 strongly predicts decreased 4-year survival, establishing microbial drift toward uniqueness as a hallmark of healthy longevity (Wilmanski et al., 2021).
  12. Metagenomic Prediction of Dietary Weight Loss: Baseline gut metagenomic capacity for fermenting dietary fiber into short-chain fatty acids (SCFAs, e.g., butyrate—a native GLP-1 secretagogue) strongly correlates with successful weight loss, whereas high bacterial capacity to cleave carbs into simple sugars impairs weight loss (Diener et al., 2021).
  13. Metabolic BMI Discrepancy: Multiomic machine learning models calculate a “Biological BMI” from blood plasma metabolomics/proteomics that frequently reveals severe underlying metabolic dysregulation in individuals with normal standard body mass index scores.
  14. Microbiome Modulation of Statin Response: Bacteroides-enriched gut microbial profiles are associated with a twofold greater reduction in LDL cholesterol under statin therapy, while specific gut compositions modulate the risk of statin-induced new-onset diabetes [Source unverified in live search].
  15. Calibration of Biological Age Algorithms: Applying the Klemera-Doubal Method (KDA) across multiomic datasets forces a population slope of 1.0 year/year, establishing a rigorous metric to evaluate whether therapeutic interventions alter biological aging velocity.
  16. Measured Reversal of Biological Age Slopes: Longitudinal dynamic tracking of ~3,500 Arivale cohort participants demonstrated an average biological age reduction of 0.16 years per chronological year during structured wellness coaching, with female participants averaging a 0.5 year/year reduction.
  17. Directionality of Biological Age Signals: Across all statistically significant clinical disease states evaluated in dense dynamic clouds, presence of disease is universally associated with elevated biological age; zero disease states correlate with a younger biological age.
  18. Federated AI Privacy Architecture: The Healthspan Horizons platform utilizes federated AI infrastructure, keeping sensitive raw genomic and health data decentralized at the user level while transmitting privacy-preserved machine learning intelligence.
  19. N-of-1 Health Intelligence via Compass AI: Compass AI integrates whole genome sequencing, clinical labs, continuous wearable telemetry, environmental exposome metrics, and multiomics into a personalized generative AI model to project health trajectories.
  20. Mahalanobis Distance Metric for Physiological Entropy: High-dimensional Mahalanobis distance algorithms aggregate multiomic feature sets to quantify biological disorder and detect subtle, presymptomatic health declines prior to out-of-range clinical lab signals.
  21. Exposome Integration: The platform layers zip-code level environmental variables (particulate matter air pollution, ambient temperature extremes, smoke exposure) onto multiomic profiles to isolate environmental drivers of chronic inflammation.
  22. Inherent Biological Trade-Offs: Optimizing single biomarkers induces trade-offs across other physiological axes (e.g., aggressive dietary restriction to lower APOB/LDL-C or Lp(a) can induce steep drops in adrenal androgens like DHEA-S).
  23. Inverse Disease Risk Coupling: Genetic and metabolic pathways that support cellular energetics and protect against neurodegenerative cell death (e.g., elevated mitochondrial respiration) frequently increase long-term oncogenic risk via reactive oxygen species generation.
  24. Inadequacy of Annual Blood Testing: Infrequent annual blood sampling fails to establish dynamic trajectory slopes due to biological variation; 2 to 4 multiomic testing points per year are necessary to calculate true biomarker velocity.
  25. Passive Dietary Context Capture: Emerging AI modalities aim to replace manual dietary logging with passive capture techniques, combining multimodal computer-vision meal analysis, financial transaction categorization, and hair isotopic/metabolomic profiling.

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Evidence)

  • Multidomain Lifestyle Protocol for Cognitive Health: Implement a structured multidomain preventive protocol consisting of a Mediterranean-Nordic diet (high complex fiber, low refined sugars), 150+ minutes/week of combined aerobic and progressive resistance exercise, cognitive engagement, and tight vascular risk management (maintaining blood pressure <130/80 mmHg and HbA1c <5.7%) to reduce long-term dementia risk (Kivipelto et al., 2015).
  • Genetically Stratified Lipid Management: Evaluate APOB, LDL-C, and Lp(a) in the context of polygenic risk scores (PRS). If genetic CAD/LDL risk is high, combine lifestyle modifications with early evidence-based pharmacology (e.g., statins, ezetimibe, or PCSK9 inhibitors), as lifestyle changes alone fail to close large genetic gaps in high-PRS individuals (Wainberg et al., 2020).

Experimental Tier (Level C/D Evidence with High Safety Margins)

  • Microbiome Optimization for Short-Chain Fatty Acid Production: Increase daily intake of diverse soluble fibers and resistant starches to promote gut taxa that produce butyrate and propionate (e.g., Roseburia, Faecalibacterium), supporting endogenous GLP-1 secretion and metabolic health (Diener et al., 2021).
  • Longitudinal Biomarker Velocity Tracking: Perform multiomic or expanded clinical chemistry panels 2 to 4 times per year to calculate biological age slopes (e.g., via Klemera-Doubal or biological BMI algorithms) and detect presymptomatic biological drift.

Red Flag Zone (Claims Debunked or Safety Data Absent)

  • Single-Biomarker Optimization Without Multiomic Monitoring: Aggressively manipulating diet or supplements to drive a single marker to extreme levels (e.g., driving APOB/LDL-C to ultra-low levels without monitoring collateral drops in DHEA-S, testosterone, or fat-soluble vitamins) (Safety Data Absent; High Risk of Endocrine Dysfunction).
  • Direct Clinical Decision-Making via Uncalibrated Epigenetic Clocks: Relying on single-timepoint direct-to-consumer epigenetic clock scores to initiate or discontinue prescription medications without confirming underlying clinical chemistry, organ function, and cardiovascular imaging (Safety Data Absent).

Produced by Gemini 2.0 Flash

How I’ve Increased HRV by 53% While Also Reducing RHR

I. Executive Summary

Long-term longitudinal tracking of autonomic nervous system (ANS) tone—quantified via Resting Heart Rate (RHR) and Heart Rate Variability (HRV)—demonstrates that multi-variable lifestyle interventions can reverse age-associated cardiovascular decline. Across nearly 2,900 consecutive days of continuous biometric tracking from 2018 through 2026, Dr. Mike Lustgarten recorded an 18.4% reduction in annual average RHR (dropping from 51 bpm to 41.6 bpm) alongside a 53.2% increase in average HRV (rising from 47 ms to 72 ms, reaching 74 ms in recent spot tracking).

Crucially, evaluating low RHR in isolation introduces significant diagnostic ambiguity in older populations. While a low RHR reflects high cardiorespiratory fitness in youth, non-physiologic bradycardia in older adults frequently stems from age-related cardiac conduction system degeneration. Combining low RHR with high HRV differentiates youthful cardiac vagal dominance from pathological conduction decay. In age-stratified normative data, HRV declines linearly with age, with expected mean values near 35 ms for middle-aged adults; achieving an HRV of 72 ms at an RHR of 42 bpm indicates preserved or restored autonomic flexibility and vagal tone.

Linear regression modeling of daily longitudinal data demonstrated that three primary physiological inputs—body weight (reduced from 160 lbs to 140 lbs), Average Daily Heart Rate (ADHR, serving as an integrated metric of total daily physical strain), and total caloric intake—account for 72% of daily RHR variation (R^2 = 0.72, p < 0.001). However, these same core variables accounted for only 32% of daily HRV variance (R^2 = 0.32, p < 0.001), proving that HRV is governed by a far more complex array of non-caloric physiological, psychological, and environmental determinants.

To address this predictive shortfall, a stepwise linear regression model incorporating ten specific dietary factors (including Vitamin B6, N-acetylcysteine, beta-cryptoxanthin, collard greens, pickles, almonds, flaxseed, lemon peel, oats, and green peas) increased the explained variance for HRV from 32% to 39% (R^2 = 0.39) and for RHR from 72% to 74% (R^2 = 0.74). While single-subject (n=1) observational regressions cannot prove causal mechanisms due to residual confounding and collinearity, these empirical models underscore the clinical potential of personalized biometric modeling for optimizing cardiovascular longevity.

II. Insight Bullets

  1. Autonomic Biomarker Integration: Resting Heart Rate (RHR) and Heart Rate Variability (HRV) serve as localized cardiac surrogates for overall autonomic nervous system (ANS) tone and adrenal gland activity.
  2. Sympathovagal Balance Dynamics: Parasympathetic (vagal) activation slows sinus node firing and increases beat-to-beat variability, whereas sympathetic activation triggers adrenal catecholamine release (epinephrine/norepinephrine), elevating RHR and suppressing HRV.
  3. The RHR Longevity Paradox: RHR follows a U-shaped trajectory across the lifespan, rising until approximately age 50 before declining in late life. Consequently, a low RHR in an older adult can signify either athletic conditioning or age-related sinus node dysfunction.
  4. HRV as the Diagnostic Differentiator: HRV declines linearly with chronological age. Combining low RHR with high HRV confirms youthful cardiac vagal modulation rather than age-related degenerative bradycardia.
  5. Eight-Year Longitudinal Trajectory: Continuous daily tracking over ~2,900 days (2018–2026) demonstrated a sustained reduction in baseline RHR from 51 bpm in 2018 to an average of 41.6 bpm in 2026.
  6. HRV Optimization Magnitude: Over the same 8-year span, annual average HRV increased by 53%, advancing from 47 ms (2018 baseline) to a peak 6-month average of 72 ms in 2026, far exceeding the age-matched norm of ~35 ms.
  7. Biometric Concordance: RHR and HRV must be tracked concurrently; evaluating either metric in isolation provides an incomplete assessment of cardiovascular stress resilience and autonomic balance.
  8. Primary RHR Regression Model: A three-variable linear regression model consisting of body weight, Average Daily Heart Rate (ADHR), and daily caloric intake explains 72% of daily RHR variation (R^2 = 0.72, p < 0.05).
  9. Primary HRV Regression Model: The same three core variables (body weight, ADHR, calorie intake) account for only 32% of daily HRV variation (R^2 = 0.32, p < 0.05), proving HRV is vastly more sensitive to non-caloric and subtle environmental inputs.
  10. Average Daily Heart Rate as Activity Surrogate: ADHR captures total daily physical strain (e.g., walking on inclines vs. flat ground) far more accurately than step counts alone.
  11. Impact of Weight Loss on Autonomic Function: Reducing body weight from 160 lbs to 140 lbs and maintaining this mass served as a structural driver for decreasing baseline RHR and elevating HRV.
  12. Caloric Surges and Sympathetic Tone: Overeating acutely surges sympathetic activity; an isolated 9,000-calorie overeating event caused a pronounced temporary spike in RHR and drop in HRV.
  13. Relocation and Environmental Stress: Geographic relocation (Boston to Austin in 2025) transiently elevated average RHR (to 43 bpm) and reduced HRV (to 61 ms), illustrating the measurable autonomic impact of environmental transition.
  14. Dietary Regression Enhancement for RHR: Stepwise addition of ten specific dietary items increased the predictive capacity (R^2) for RHR from 72% to 74% (+2%).
  15. Dietary Regression Enhancement for HRV: Incorporating the same ten dietary variables into the HRV model increased explained variance from 32% to 39% (+7%).
  16. Dual-Concordant Dietary Factors: Ten specific dietary inputs demonstrated inverse associations with RHR (negative beta coefficients) and direct associations with HRV (positive beta coefficients): Vitamin B6, NAC, beta-cryptoxanthin, collard greens, pickles, almonds, flaxseed, lemon peel, oats, and green peas.
  17. Nutritional Determinant – Vitamin B6: B6 intake correlated with reduced RHR and elevated HRV, likely reflecting its role as an essential enzymatic cofactor in neurotransmitter synthesis (GABA, serotonin).
  18. Nutritional Determinant – N-Acetylcysteine (NAC): NAC intake was positively associated with HRV enhancement, potentially driven by glutathione synthesis, reduction of systemic oxidative stress, and modulation of sympathetic outflow.
  19. Nutritional Determinant – Beta-Cryptoxanthin: As a potent carotenoid antioxidant, higher beta-cryptoxanthin intake correlated with favorable shifts in both autonomic markers.
  20. Nutritional Determinant – Collard Greens & Nitrates: Leafy greens rich in dietary inorganic nitrates boost endothelial nitric oxide (NO) bioavailability, promoting vasodilation, reducing cardiac workload, and enhancing vagal tone.
  21. Nutritional Determinant – Almonds & Monounsaturated Fats: Whole almond intake supported parasympathetic tone, consistent with trial data showing nut consumption protects HRV during acute mental stress.
  22. Nutritional Determinant – Flaxseed & Alpha-Linolenic Acid (ALA): Flaxseed provides plant-based omega-3 fatty acids and lignans that modulate cardiac ion channels and attenuate sympathetic overactivity.
  23. Nutritional Determinant – Citrus & Lemon Peel: Bioflavonoids (e.g., hesperidin, eriocitrin) present in citrus peels exert vasodilatory and autonomic-modulating effects.
  24. Nutritional Determinant – Oats & Beta-Glucans: Soluble beta-glucan fibers improve glycemic stability and metabolic homeostasis, damping postprandial sympathetic spikes.
  25. Nutritional Determinant – Green Peas & Legumes: Plant protein and fiber sources support gut microbiome short-chain fatty acid production, which influences central autonomic control via the gut-brain axis.
  26. Nutritional Determinant – Fermented Foods (Pickles): Fermented sodium-rich foods like pickles showed positive statistical alignment in this specific model, likely modulated by fluid volume expansion in a lean, active individual.
  27. Prescription Biohacking Framework: The ultimate goal of longitudinal multi-variable tracking is to build high-precision predictive models (R^2 approaching 1.0) enabling personalized exercise and nutritional prescriptions.
  28. Transient vs. Sustained Biometric Peaks: Short-term metrics (e.g., July spot averages of 80–86 ms HRV and 38–39 bpm RHR) represent peak physiological states, requiring monthly aggregation (e.g., 74 ms / 40 bpm) to prevent selection bias.

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Backed by Level A/B Evidence)

  1. Caloric Restriction and Weight Management:
  • Protocol: Achieve and maintain a lean body mass (BMI ~19.5–21.0 kg/m² or a targeted 12–15% body mass reduction if overweight).
  • Evidence: Meta-analyses confirm caloric restriction and weight loss significantly reduce resting heart rate, lower systemic vascular resistance, and elevate high-frequency HRV by attenuating baseline sympathetic tone and improving cardiac vagal control (World et al., 2018; Sjoberg et al., 2021).
  1. Whole Nut Consumption (Almonds):
  • Protocol: Consume 30–50 g/day of whole almonds as a primary snack replacement.
  • Evidence: Randomized controlled trial (RCT) data demonstrates that 6 weeks of daily whole almond snacking significantly preserves high-frequency HRV power (parasympathetic regulation) during acute mental stress and improves endothelial function (Dikariyanto et al., 2020).
  1. Inorganic Nitrate / Leafy Green Vegetable Intake (Collard Greens):
  • Protocol: Daily intake of 100–200 g of nitrate-rich leafy greens (collard greens, spinach, arugula).
  • Evidence: Meta-analyses establish that dietary inorganic nitrates enhance endothelial nitric oxide bioavailability, reduce arterial stiffness, lower central blood pressure, and improve autonomic recovery (Benjamim et al., 2022).
  1. Cardiorespiratory Conditioning & Load Balancing:
  • Protocol: Monitor Average Daily Heart Rate (ADHR) as an integrated strain metric, balancing aerobic zone-2 cardio with structured recovery days.
  • Evidence: Extensive prospective cohort meta-analyses prove that a lower baseline resting heart rate (<50 bpm) achieved via aerobic fitness is independently associated with a significant reduction in all-cause and cardiovascular mortality (Zhang et al., 2016).

Experimental Tier (Level C/D Evidence with High Safety Margins)

  1. N-Acetylcysteine (NAC) Supplementation:
  • Protocol: 600–1,200 mg/day oral NAC.
  • Evidence: Mechanistic and preliminary clinical literature highlights NAC’s role as a glutathione precursor that mitigates cardiometabolic oxidative stress and modulates sympathetic signaling; direct RCT evidence establishing daily NAC as an HRV-enhancing intervention in healthy populations remains limited (Batycka et al., 2025).
  1. Flaxseed & Plant Omega-3 (ALA) Inclusion:
  • Protocol: 15–30 g/day ground flaxseed.
  • Evidence: Evidence shows dietary ALA and lignans support vascular health, though marine omega-3s (EPA/DHA) possess stronger Level A evidence for directly increasing parasympathetic HRV than plant-derived ALA (Mason et al., 2025).
  1. Citrus Bioflavonoids & Peel (Lemon Peel/Citrus Zest):
  • Protocol: Dietary inclusion of whole citrus zest or bioflavonoid extracts (hesperidin, eriocitrin).
  • Evidence: Pilot studies demonstrate citrus bioflavonoids improve microvascular reactivity and transiently elevate parasympathetic HRV metrics (Matsumoto et al., 2014).
  1. Soluble Fiber & Legume Integration (Oats, Green Peas):
  • Protocol: Daily intake of beta-glucan rich oats (40–80 g) and green legumes.
  • Evidence: RCT evidence confirms blood glucose stabilization and gut microbiome short-chain fatty acid generation, which indirectly support autonomic balance by smoothing postprandial glycemic excursions.
  1. Fermented Foods & Electrolyte Balance (Pickles):
  • Protocol: Moderate inclusion of fermented pickles/brine in physically active individuals.
  • Evidence: Source unverified in live search for direct HRV enhancement RCTs in general populations. This n=1 correlation likely reflects acute plasma volume expansion and electrolyte rebalancing in a lean, low-sodium, highly active individual.

Red Flag Zone (Claims Debunked or Lacking Safety Data)

  1. High-Dose Vitamin B6 (Pyridoxine) Monotherapy:
  • Risk / Flaw: While Vitamin B6 intake correlated with improved HRV in the single-subject regression model, high-dose B6 supplementation (>50–100 mg/day) carries a documented, severe risk of sensory axonal polyneuropathy and dysautonomia (Bacharach et al., 2017).
  • Status: Red Flag Zone / Safety Data Absent for High-Dose Supplementation. Vitamin B6 should be obtained from dietary sources or low-dose multivitamins (<10–20 mg/day).
  1. Over-Reliance on Single-Subject (n=1) Stepwise Regressions:
  • Risk / Flaw: Attributing direct causality to specific foods (e.g., pickles or lemon peel) based on minor R^2 increments (+2% to +7%) in an n=1 study introduces severe risks of overfitting, spurious correlation, and unmeasured confounding (such as concurrent sleep quality, ambient temperature, or hydration).
  • Status: Translational Gap / Overfitting Risk. Empirical single-subject regressions require controlled crossover RCT confirmation before clinical adoption.
  1. Extreme Caloric Restriction in Low-BMI Individuals:
  • Risk / Flaw: Pushing body weight down to artificially suppress RHR risks hypothalamic-pituitary-adrenal (HPA) axis dysregulation, hormonal suppression (testosterone, thyroid hormone), loss of lean tissue mass, and impaired stress resilience.
  • Status: Red Flag Zone. Caloric restriction must be carefully balanced against endocrine and musculoskeletal safety.

Did Eating Too Many Sardines Increase Homocysteine?

. Executive Summary

In this n=1 observational cohort study encompassing 56 blood tests across 21 years (2005–2026), Dr. Mike Lustgarten evaluates age-related plasma homocysteine kinetics, its epidemiological association with all-cause mortality, and acute dietary drivers of hyperhomocysteinemia. Longitudinal tracking reveals a statistically significant age-dependent increase in plasma homocysteine (r=0.51, p=6.0×10⁻⁵). Cross-sectional literature demonstrates baseline values rising from ~7.0 µmol/L in healthy youth to ~12.0 µmol/L in octogenarians and ~23.0 µmol/L in centenarians (median age 100 years, n=1,800). Meta-analyses confirm that circulating homocysteine is monotonically associated with elevated all-cause mortality risk, establishing a strong biological rationale for targeting lower steady-state concentrations to promote healthspan and longevity.

Between April and June 2026, the investigator recorded an acute spike in plasma homocysteine from 8.3 µmol/L to 12.0 µmol/L—a +4.0 µmol/L shift representing his second highest measurement over 21 years. Given that background methyl-donor supplementation (comprising 1.0 g/day N-acetylcysteine, methylfolate, methylcobalamin, and 1.5 mg/day pyridoxine) remained constant, an extrinsic factor was implicated. Quantitative dietary tracking via Chronometer identified a concurrent acute increase in three high-arsenic whole foods: canned sardines (increased from 105 g/day to 183 g/day), pistachios (increased from 4 g/day to 38 g/day), and ground flaxseeds (increased from 0 g/day to 36 g/day).

The primary biological hypothesis connects heavy-metal clearance to transsulfuration pathway dynamics. Hepatic excretion of inorganic arsenic requires double-methylation by Arsenic (+3 oxidation state) methyltransferase (AS3MT), consuming stoichiometric equivalents of S-adenosylmethionine (SAM). Physiological SAM concentrations allosterically activate cystathionine β-synthase (CBS), the rate-limiting enzyme converting homocysteine and serine to cystathionine via vitamin B6. Elevated dietary inorganic arsenic intake (+31 µg/day total estimated net increase across the three foods) depletes hepatic SAM pools. This SAM depletion dampens CBS allosteric activation, impairing homocysteine transsulfuration and driving systemic accumulation. This xenobiotic stress compounds age-related declines in mitochondrial ATP synthesis, which inherently constrain de novo SAM generation via methionine adenosyltransferase (MAT). Longitudinal n=1 correlation analyses show statistically significant positive associations between plasma homocysteine and intake of sardines and pistachios, but not flaxseed. The resulting clinical intervention replaces sardines with wild-caught salmon to preserve long-chain omega-3 fatty acid intake while reducing heavy-metal exposure, alongside flaxseed elimination and pistachio minimization.

II. Insight Bullets

  1. Longitudinal Biomarker Dataset Depth: The investigator’s personal tracking dataset spans 21 years (2005–2026) and 56 discrete blood panels, providing a robust long-term baseline for plasma homocysteine kinetics.
  2. Statistically Significant Age Correlation: Serial blood testing demonstrates a clear, age-dependent increase in plasma homocysteine (r=0.51, p=6.0×10⁻⁵).
  3. Youth Baseline Norms: Healthy young men and women maintain average serum/plasma homocysteine concentrations of approximately 7.0 µmol/L.
  4. Octogenarian Biomarker Elevation: Average plasma homocysteine concentrations escalate to approximately 12.0 µmol/L in individuals aged 80 years and older.
  5. Centenarian Hyperhomocysteinemia: In an epidemiological cohort of ~1,800 individuals with a median age of 100 years, median serum homocysteine reached 23.0 µmol/L, demonstrating severe progressive age-related elevation.
  6. Monotonic All-Cause Mortality Association: Meta-analytic data show that all-cause mortality hazard ratios rise continuously with increasing circulating homocysteine levels (Peng et al., 2024).
  7. Absence of a Mortality Floor: Hazard ratio curves confirm no lower threshold where reduced homocysteine becomes detrimental, validating “as low as reasonably achievable” target strategies.
  8. Acute Test-Over-Test Shift: Plasma homocysteine increased from 8.3 µmol/L in April 2026 to 12.0 µmol/L in June 2026, marking an anomalous +4.0 µmol/L jump.
  9. Historical Biomarker Stability: Over 21 years, the investigator’s homocysteine levels remained tightly bound within the 9.0–11.0 µmol/L range, establishing the +4.0 µmol/L shift as a true biological signal rather than laboratory noise.
  10. Limited Efficacy of Standard B-Vitamin Trio: Co-supplementation with methylfolate, methylcobalamin (B12​), and low-dose B6​ (1.5 mg/day) yielded only a modest ~10% reduction in baseline homocysteine (from ~11.0 to ~10.0 µmol/L).
  11. N-Acetylcysteine Insufficiency: Daily intake of 1.0 g N-acetylcysteine (NAC) was insufficient to prevent the acute diet-induced spike in plasma homocysteine.
  12. High-Precision Diet Quantification: Over 99% of total food mass was weighed and logged continuously in Chronometer across an 11-year testing period (2015–2026).
  13. Sardine Exposure Delta: Daily canned sardine intake was elevated from 105 g/day to 183 g/day between April and June 2026 in an effort to raise the cell membrane Omega-3 Index.
  14. Pistachio Intake Shift: Daily pistachio consumption was increased from 4 g/day to 38 g/day over the same testing window.
  15. Flaxseed Protocol Introduction: Ground flaxseed intake was increased from 0 g/day to 36 g/day prior to the June blood panel.
  16. Whole-Food Heavy Metal Vectors: Canned sardines, pistachios, and flaxseeds were identified as prominent dietary sources of organic and inorganic arsenic species.
  17. Sardine Total Arsenic Load: Canned sardines contain approximately 68 µg to 221 µg total arsenic per 85 g serving, depending on commercial sourcing and processing.
  18. Inorganic Arsenic Fraction in Fish: Inorganic arsenic constitutes an estimated 10% of total sardine arsenic mass, delivering ~6.8 µg inorganic arsenic per 85 g serving.
  19. Pistachio Arsenic Contamination: Pistachio nuts contain between 67 µg and 189 µg total arsenic per kilogram, with pistachio oil fractions containing up to 64% inorganic arsenic species (Sadee et al., 2024).
  20. Flaxseed Arsenic Density: Flaxseeds contain approximately 750 µg total arsenic per kilogram (0.75 mg/kg), rivaling sardine concentrations on a dry mass basis.
  21. Estimated Inorganic Arsenic in Flaxseeds: Assuming an average 74% inorganic fraction across oilseeds, 36 g/day of flaxseed supplies ~20 µg/day of inorganic arsenic.
  22. Cumulative Net Exposure Delta: Combined dietary changes produced an estimated net increase of +31 µg/day in inorganic arsenic intake between testing intervals.
  23. Hepatic AS3MT Methylation Demand: Enzymatic detoxification of inorganic arsenic via Arsenic (+3 oxidation state) methyltransferase (AS3MT) requires sequential methyl transfers from S-adenosylmethionine (SAM) (Reichard et al., 2007).
  24. SAM Depletion Dynamics: Heavy xenobiotic methyl demand for arsenic detoxification drains hepatic SAM pools, lowering the intracellular SAM ratio.
  25. Allosteric Regulation of CBS: Cystathionine β-synthase (CBS) requires direct allosteric binding of SAM at its C-terminal regulatory domain for full enzymatic activation (Ereno-Orbea et al., 2013).
  26. Transsulfuration Impairment: SAM depletion inhibits CBS activity, blocking the irreversible transsulfuration of homocysteine into cystathionine and causing upstream plasma accumulation.
  27. Mitochondrial ATP Constraint on SAM: De novo SAM synthesis from methionine via methionine adenosyltransferase (MAT) requires cellular ATP; age-related mitochondrial decline limits SAM regeneration capacity (SAM Metabolism Review).
  28. Longitudinal Diet-Biomarker Correlations: Long-term paired diet-blood data (2015–2026) revealed statistically significant positive correlations between plasma homocysteine and intake of sardines and pistachios.
  29. Absence of Correlation with Flaxseed: Long-term n=1 data showed no significant statistical correlation between flaxseed intake and plasma homocysteine, despite high theoretical arsenic content.
  30. Dietary Substitution Strategy: Replacing sardines with wild-caught salmon lowers heavy-metal exposure while maintaining long-chain omega-3 fatty acid intake (EPA/DHA).

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Evidence)

  • Targeted B-Vitamin Co-Therapy (5-MTHF + Methylcobalamin + P5P): Level A meta-analyses (Clarke et al., 2007; Zhao et al., 2025) establish that combined supplementation with 5-methyltetrahydrofolate (0.8 mg/day), methylcobalamin (0.4–1.0 mg/day), and pyridoxal-5’-phosphate (B6) reliably lowers plasma homocysteine by 20–30% by stimulating remethylation via methionine synthase and transsulfuration via CBS.
  • Betaine / Trimethylglycine (TMG) Supplementation: Level A meta-analysis (McRae, 2013) demonstrates that 1.5 g to 6.0 g/day of betaine lowers circulating homocysteine by providing methyl groups for the betaine-homocysteine S-methyltransferase (BHMT) pathway, operating independently of folate and B12​.
  • Low-Toxin Marine Seafood Selection: Level A/B dietary toxicological guidelines (Sadee et al., 2024) recommend substituting high-arsenic or heavy-metal-dense marine matrices with wild-caught low-trophic fish (e.g., wild Alaskan salmon) to secure EPA and DHA without imposing heavy-metal methyl stress.

Experimental Tier (Level C/D Evidence with High Safety Margins)

  • Dietary Arsenic Mitigation (Seed and Nut Moderation): Preclinical and mechanistic human data (Reichard et al., 2007) confirm that heavy intake of inorganic arsenic depletes hepatic SAM pools during AS3MT clearance. Restricting high-arsenic seed loads (flaxseed >30 g/day) and tree nuts (pistachios >35 g/day) reduces xenobiotic methyl consumption and preserves SAM for CBS activation. Safety Margin: High (dietary modification).
  • Cofactor Support for BHMT and MS (Zinc & Choline): Mechanistic evidence (Ereno-Orbea et al., 2013) identifies zinc as an essential catalytic cofactor for BHMT and methionine synthase. Choline serves as a direct precursor for endogenously synthesized betaine. Safety Margin: High at standard daily nutritional doses (Zinc 15–30 mg/day; Choline 300–550 mg/day).
  • N-Acetylcysteine (NAC) Co-therapy: Level C human trials indicate that 1.0 g/day NAC provides cysteine downstream of CBS, reducing demand on the transsulfuration pathway and supporting intracellular glutathione synthesis without directly activating CBS. Safety Margin: High.

Electrical Stimulation Promotes Rejuvenation And Longevity

Yos Domen of Stanford University detail findings from their landmark study published in PNAS (Voskoboynik et al., 2026) regarding the rejuvenative effects of brief Pulsatile Electrical Current (PEC) on the colonial tunicate Botryllus schlosseri. Sharing approximately 75% protein sequence homology with humans, Botryllus serves as a unique chordate model of stem cell-mediated aging. Because the organism reabsorbs all somatic tissues weekly via apoptosis and regenerates new organ systems from adult progenitor pools, organismal senescence in Botryllus is fundamentally an expression of stem cell degradation. Aging in Botryllus manifests as reduced zooid volume, organ shrinkage, neural loss, circadian clock desynchronization, blunted heart rate variability, and diminished reproductive output.

To test bioelectric modulation, the researchers applied a single, acute session of PEC using a clinical cardiac pacing device delivering 150 pulses per minute (approximately 2.5 Hz) across three five-minute bursts separated by 15-minute rest intervals. This single 15-minute intervention induced systemic, multi-month reversal of age-related phenotypes. PEC-treated aged colonies demonstrated a dramatic restoration of zooid size, elongated vascular ampullae, accelerated blastogenic growth rates, and extended organismal survival (75% survival in treated colonies versus 17% in controls at one-year follow-up). Furthermore, PEC restored off-season gametogenesis and gonad production.

Whole-transcriptome profiling revealed a distinct biphasic “reboot and rebound” program. At two hours post-stimulation, global gene expression underwent widespread downregulation across signaling, epigenetic, and metabolic pathways. By 24 hours, this acute repression transitioned into sustained upregulation of transcription factors, epigenetic modulators, mitochondrial metabolic genes, and extracellular matrix regulators, with effects persisting beyond four months. Crucially, PEC triggered an immunometabolic shift from a transient pro-inflammatory state to a reparative M2-like macrophage signature, closely mirroring the transcriptomic response observed following physical exercise in mammals. While these preclinical findings highlight bioelectricity as a potent lever for resetting stem cell epigenetics, direct human application remains unproven. Systemic bioelectric rejuvenation lacks human safety and efficacy data, restricting clinical validation to localized modalities such as neuromuscular electrical stimulation.

II. Insight Bullets

  1. Stem Cell-Driven Model Organism: Botryllus schlosseri is a colonial tunicate and invertebrate chordate that undergoes weekly cycles of blastogenesis, where all adult tissues die via apoptosis and are regenerated de novofrom adult stem cells. Consequently, organismal aging in this species reflects pure adult stem cell senescence (Voskoboynik et al., 2026).
  2. High Protein Homology: Genomic sequencing demonstrates that approximately 75% of human proteins have significant sequence orthology in Botryllus schlosseri, making its molecular pathways relevant for studying fundamental chordate biology and stem cell regulation.
  3. Age-Associated Morphological Atrophy: As Botryllus colonies age (e.g., reaching 15–20 years in laboratory culture), the size of newly regenerated adult individuals (zooids) shrinks to one-third or less of the size produced by young 1-year-old colonies.
  4. Organ System Retraction: Specific internal structures, including the endostyle, heart, and digestive tract, show pronounced anatomical shrinkage in aged colonies compared to young controls.
  5. Neuronal Atrophy and Cell Loss: The central nervous system of Botryllus zooids reaches peak cell counts on day 4 of the weekly blastogenic cycle; young colonies exhibit ~1,000 neurons per zooid, whereas aged 15-year-old colonies drop to ~800 neurons.
  6. Neurodegenerative Gene Signature: Transcriptomic analysis of aged Botryllus brains reveals significant dysregulation of over 200 genes associated with human neurodegenerative disorders, including orthologs linked to early-onset Alzheimer’s disease (e.g., APP variants).
  7. Circadian Rhythm Decoupling: Expression of core circadian clock regulators (Clock and Cycle/Bmal1) exhibits tight diurnal oscillations in middle-aged colonies, whereas aged colonies lose rhythmic expression patterns, exhibiting uncoordinated circadian transcription around the clock.
  8. Loss of Cardiac Diurnal Dynamics: Young colonies display significant day-versus-night variations in heart rate (slowing down at night similar to mammals), whereas aged colonies lose this diurnal variability and maintain a sluggish, invariant cardiac rhythm.
  9. Serendipitous Bioelectric Discovery: The rejuvenative potential of electrical stimulation was discovered accidentally when researchers attempted to pace sluggish, unhealthy colonies using a temporary cardiac pacemaker to synchronize cardiac contractions.
  10. Pulsatile Electrical Current (PEC) Rig: The experimental protocol utilized a clinical Medtronic external cardiac pacemaker with submerged leads delivering a current at 150 pulses per minute (~2.5 Hz) in ambient seawater.
  11. Minimal Effective Dosing: The optimized treatment protocol requires only three 5-minute pulses of electrical stimulation separated by 15-minute rest intervals (totaling 15 minutes of active exposure), administered as a single acute session.
  12. Multi-Month Rejuvenation Persistence: A single 15-minute PEC treatment induced morphological and physiological improvements that persisted for over 200 days (~6.5 months), spanning dozens of weekly blastogenic replacement cycles.
  13. Zooid Size Recovery: PEC treatment in 20- to 24-year-old aged colonies restored the physical volume of regenerated zooids back to dimensions characteristic of young 1-year-old colonies.
  14. Vascular Ampullae Elongation: PEC stimulation caused peripheral blood vessel termini (ampullae) to lengthen and project outward, restoring youthful vascular network architecture.
  15. Enhanced Blastogenic Growth: Treated colonies produced a significantly higher number of buds per cycle, accelerating colony expansion rates relative to sham-treated controls.
  16. Reversal of Reproductive Senescence: In autumn months—when Botryllus colonies naturally enter reproductive diapause—PEC treatment restored active gametogenesis and gonad formation in 77% of colonies compared to 11% in controls (7/9 vs. 1/9).
  17. Dramatic Longevity Extension: At a 1-year post-treatment follow-up, 75% of PEC-stimulated colonies remained alive and growing, compared to only 17% of control colonies (9/12 vs. 2/12).
  18. Flow Cytometry Dynamics: Flow cytometric profiling based on forward/side scatter and enzymatic staining demonstrated stable long-term shifts in specific somatic and progenitor cell populations following PEC intervention.
  19. Biphasic Transcriptomic “Reboot” (2 Hours): Bulk RNA sequencing at 2 hours post-PEC revealed global, systemic downregulation of transcripts across signaling, metabolic, and epigenetic pathways, indicating an acute cellular reset or “shutdown.”
  20. Biphasic Transcriptomic “Rebound” (24 Hours): By 24 hours post-PEC, gene expression shifted to massive upregulation across transcription factors, epigenetic modulators, mitochondrial metabolic pathways, extracellular matrix (ECM) components, and immune regulators.
  21. Exercise-Mimetic Immunometabolic Signature: The transcriptomic profile following PEC closely mirrors the biphasic immune response observed after physical exercise in mammals, transitioning from an initial pro-inflammatory state to a sustained reparative, M2-like macrophage/immune state.
  22. Mechanistic Distinction from Clinical Pacing: Clinical cardiac pacemakers provide continuous local pacing to compensate for conduction blockages in diseased hearts, whereas PEC acts as a brief, global field stimulus that alters stem cell epigenetic programming.
  23. Bioelectric Goal-Directedness: The findings align with bioelectric developmental models (Levin, 2024), suggesting that exogenous electrical fields restore bioelectric cues that guide cellular coordination and tissue patterning lost during aging.
  24. Long-Term Re-Treatability: When rejuvenated colonies eventually begin to show age-related decline months later, re-application of the 15-minute PEC protocol successfully induces a secondary wave of morphological rejuvenation.
  25. Stem Cell Chimerism and Competition: Colonial tunicates can fuse blood vessels with histocompatible kin to form chimeras, triggering internal competition between stem cell lineages; PEC’s interaction with host stem cell fitness in chimeras remains an active area of study.
  26. Microbiome Interaction Hypotheses: Researchers are investigating whether PEC directly alters the colony microbiome or if rejuvenated host tissue secondary metabolites clean and reset the commensal bacterial population.
  27. Targeting Neural Progenitors: Ongoing investigations focus on isolating neural stem cells and evaluating whether PEC directly stimulates neurogenesis and reverses brain transcriptomic pathology in aged chordates.
  28. Translational Bottlenecks: Translating marine chordate field stimulation to mammals requires overcoming major physiological gaps, including tissue impedance, localized organ targeting, and risk of fatal cardiac arrhythmias.

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Human Clinical Evidence)

Protocols backed by rigorous human randomized controlled trials (RCTs) and systematic meta-analyses for electrical stimulation in clinical settings.

  • Neuromuscular Electrical Stimulation (NMES) for Atrophy Prevention:
    • Evidence Level: Level A Meta-Analysis (Huang et al., 2024).
    • Clinical Protocol: Application of low-frequency NMES to quadriceps and peripheral muscle groups in critically ill or immobilized patients significantly preserves muscle strength (Medical Research Council score MD = 3.62, p=0.0008) and reduces hospital length of stay.
  • Cutaneous Electrical Stimulation for Wound Healing:
    • Evidence Level: Level A Meta-Analysis (Gardner et al., 1999).
    • Clinical Protocol: Direct current or high-voltage pulsed current applied to chronic dermal ulcers accelerates healing velocity and tissue remodeling compared to standard care.
  • Exercise-Induced Immunometabolic Optimization:
    • Evidence Level: Level A Meta-Analysis.
    • Actionable Protocol: High-intensity interval training (HIIT) combined with progressive resistance training mimics the biphasic M1-to-M2 macrophage shift, mitochondrial biogenesis, and systemic transcriptomic rebound observed in bioelectric models without invasive bioelectric risks.

Experimental Tier (Level C/D Preclinical Evidence)

Protocols backed by mechanistic animal models, in vitro stem cell studies, or early-stage exploratory research with high safety margins.

  • Pulsatile Bioelectric Current (PEC) in Stem Cell Models:
    • Evidence Level: Level C Preclinical Marine Model (Voskoboynik et al., 2026).
    • Parameters: 2.5 Hz (150 bpm) pulsatile field, 3 x 5-minute bursts with 15-minute intermissions. Induces long-term epigenetic reboot, stem cell rejuvenation, and 4x survival extension in Botryllus schlosseri.
  • Morphoceutical and Ion Channel Modulation:
    • Evidence Level: Level D Narrative Review (Levin, 2024).
    • Concept: Utilizing pharmacological ion channel modulators or targeted microcurrents to alter membrane resting potential (Vmem​) to drive tissue regeneration and suppress senescent cell patterns.
  • Non-Invasive Transcutaneous Microcurrent Therapy:
    • Evidence Level: Level D Human Exploratory Studies.
    • Status: Sub-sensory microcurrent (<1 mA) applied topically for localized soft-tissue injury or facial skin conditioning. Human systemic longevity effects are unverified.

Mike Lustgarten received some attention in this recent media piece. Nice to see his 20+ year reduction in “biological age” getting highlighted, even if the measurement is problematic in many ways.

Top biohackers share what they did to get hyper-healthy

Jessica Orwig, Daniel T. Allen

Wen Zhuang power squating with heavy weights.

  • Adam Ficsor founded the Longevity World Cup, a competition that ranks biological age reduction.

  • Mike Lustgarten won last year’s competition, reducing his estimated PhenoAge by 22.1 years.

  • We spoke to Lustgarten and two other finalists about their habits, diet, and what keeps them healthy.

Most longevity enthusiasts are trying to slow aging, but Adam Ficsor wants to outrun it.

The software engineer and Bitcoin developer says humanity could eventually reach “longevity escape velocity,” where advances in medicine extend healthy life faster than people age.

“I am talking about literally not dying,” he told Business Insider for an episode of its video series “The Limit.

To that end, he founded the Longevity World Cup, a competition that ranks who can wind back their biological clock the most.

The inaugural event announced its first winners in January, awarding about $4,000 in Bitcoin-funded prize money.

The scores were based on PhenoAge, a tool that estimates your biological age using your actual age (aka chronological age) and common blood markers like cholesterol, blood sugar, inflammation, and kidney function. Basically, it’s a “blood test-based estimate of your risk of dying,” Daniel Belsky, an associate professor of epidemiology at Columbia University’s Robert N. Butler Columbia Aging Center, told Business Insider.

Participants have about one year to achieve and submit their best results.

First-place finisher Michael Lustgarten, PhD, lowered his estimated PhenoAge by 22.1 years. Subtracting that from his chronological age of 53 by the end of the competition yielded an estimated biological age of 30.9.

Researchers continue to debate how best to measure biological aging, and experts caution that scores like PhenoAge are statistical estimates rather than direct measurements of how fast someone is aging. Moreover, it’s worth noting that large swings in biological age scores over short periods, such as weeks or months, can be difficult to interpret, said Belsky, who was not involved in the competition.

“To adjudicate these biohacking competitions is an invitation for people to hack the algorithm and generate what are ultimately non-informative results from them,” he said.

That said, Belsky added that PhenoAge can be useful for tracking broad improvements from healthier behaviors.

“If you’re seeing changes in PhenoAge in response to improvements in healthy behaviors, better management of existing health conditions, or other lifestyle changes that improve the overall quality of your environment, then I would be more likely to trust what the algorithm is saying. That’s what it’s designed to do,” Belsky said.

With that in mind, Business Insider asked the top three winners of the Longevity World Cup to walk us through the habits and routines behind their results.

3rd-place finisher Wen Zhuang focuses on fundamentals

Wen Zhuang power squating with heavy weights.

Wen Zhuang allows room for some flexibility in his routine, especially for social occasions.Courtesy of Wen Zhuang

For the competition, Wen Zhuang lowered his estimated Phenoage by 20.1 years. He was 20.6 years old chronologically by the end of the competition, which means his biological age was only 0.5 years.

This doesn’t mean that Zhuang and others with extremely low bioages are “biologically infants,” Belsky said. “They’re just people who have unusual levels of some of the blood analytes that are being tested for in the algorithm.”

Rather than following someone else’s protocol, Zhuang said that many advanced longevity interventions often vary from person to person.

At first, Zhuang’s daily routine doesn’t seem especially extraordinary: He wakes up at 6:30 a.m. each day, completes a short grooming and red-light session, eats breakfast, and then strength trains or runs depending on the day. He competes in track and field as a short-sprint athlete.

He also sticks to a diet of 45% calories from fat, 27.5% from protein, and 27.5% from carbohydrates, prioritizing seafood, vegetables, and legumes with no added sugar. He favors diverse, spice-rich meals packed with polyphenols and cooked at lower temperatures to minimize potentially harmful compounds.

Toward the end of the day, he eats an early dinner and reduces light and stimulation before bed. While regular exercise and diets rich in vegetables and legumes are linked to better health, there is little evidence that some other parts of Zhuang’s routine, such as red-light therapy, extend human lifespan.

Unlike some longevity enthusiasts, Zhuang said he’s not highly strict with his routine.

“When there’s a social occasion, the schedule bends, and I think that’s fine.” He also allows for about 10% of his meals to be social, cooking his own meals the rest of the time. “I’d argue that’s not a compromise — social connection is one of the better-supported longevity variables there is.”

Where his routine gets interesting is when you look at the list of supplements he takes weekly. It’s over 75 different supplements, including Vitamins D, E, B2, B6, B12, zinc, iodine, manganese, folate, biotin, creatine, melatonin, as well as extracts including curcumin, broccoli seed, aged garlic, and ginger — to name a few.

“If someone reads this and takes one thing away, I’d want it to be the sleep, training, seafood, and metabolic markers — not the pill list,” he emphasized.

2nd-place finisher Zdenek Sipek relies on consistency

The top three winners of the Longevity World Cup

Zdenek Sipek also reversed his biological age by more than two decades.Business Insider

Runner-up Zdenek Sipek lowered his estimated PhenoAge by 20.6 years. He was 46.4 chronologically with a bioage of 25.8.

Sipek said maintaining his routine doesn’t require constant motivation because discipline has become part of his personality.

“I am very regimented and strict with myself, and I like it in fact that way,” he said.

When asked where he occasionally slips, Sipek said it might be “a piece of chocolate,” but he said little else interrupts his routine.

He also believes longevity doesn’t have to be expensive. Sipek estimated that someone starting out could spend less than $100 a month on longevity interventions, depending on where they live.

Outside of nutrition, Sipek studies Buddhism, Daoism, and Hindu texts. He said practices that promote peace of mind are an overlooked part of longevity because they can help reduce stress.

“I think the peace of mind is absolutely critical for wellbeing,” he said.

He also makes his longevity protocol available free on Substack because, he said, “this information should be shared freely and improve people in general all around the world.”

1st-place finisher Michael Lustgarten tracks everything he can

Michael Lustgarten working out.

Michael Lustgarten lowered his estimated PhenoAge by 22.1 years for the Longevity World Cup competition.Courtesy of Michael Lustgarten

Lustgarten, an active research scientist, said his biggest advantage in the competition is years of collecting data on himself.

He’s been measuring his blood biomarkers alongside his daily diet and routine since 2015, with more than 70 blood tests over the past decade, he told Business Insider.

He said he has up to 3,000 measurements of certain biomarkers, which gives him far more opportunities to see what changes affect his biological age, for better or worse. He provides his tracking methods on YouTube.

His diet, for example, is one of the first places he starts when targeting biomarkers across the board to try to lower his biological age.

He consumes about 40% fat and 30% carbs. He used to eat more carbs and less fat, but after tracking biomarkers for cardiovascular disease risk, he said that diet wasn’t optimal.

Beyond diet, he aims to optimize the basics, mainly exercise and sleep. Similar to Zhuang, Lustgarten said supplements aren’t the end-all be-all for maximizing health. In fact, he said he prioritizes making dietary changes over supplemental ones.

For beginners looking to monetize their health optimization, Lustgarten recommends starting with regular blood work instead of an expensive supplement routine.

A standard clinical chemistry and metabolic panel can only cost about $35 through some direct-to-consumer labs, though panels at hospitals can be more expensive. These panels are helpful in that they provide information about kidney, liver, immune, red blood cell-related measures, and metabolic health.

“What I recommend people do and what I do is before every blood test, tracking diet, exercise, duration, sleep, HRV, all the things you can think about tracking for at least a week for every test,” he said. Then, after a couple of tests, start looking within your own data to see what may be moving the needle, he added.

2 Likes

The Bortz Biological Age Clock: Better Than PhenoAge?

I. Executive Summary

In this presentation, Dr. Peter K. Joshi and Dr. Michael Lustgarten evaluate the Bortz Biological Age Clock, a machine learning-derived biological age estimation algorithm published in Communications Biology (Bortz et al., 2023). Derived from a massive cohort of 306,116 participants in the UK Biobank, the Bortz clock was developed to quantify physiological deterioration and predict all-cause mortality risk using routine, circulating clinical blood biomarkers. Utilizing an Elastic-Net penalized Cox proportional-hazards regression model across 60 candidate blood-based analytes, the algorithm stably selected a core panel of 25 circulating biomarkers. On independent holdout test validation datasets, the Bortz clock achieved a concordance index (C-index) for all-cause mortality prediction of 0.778 (95% CI [0.767–0.788]), outperforming Morgan Levine’s widely cited 9-biomarker PhenoAge algorithm, which yielded a C-index of 0.750 (95% CI [0.739–0.761]) (Levine et al., 2018). This represents an 11% relative increase in predictive accuracy over PhenoAge and up to 2.46 times the predictive lift compared to an age-and-sex null baseline model.

Despite its statistical superiority in epidemiological mortality forecasting, biological age clocks derived from penalized linear models possess distinct biological paradoxes and systemic algorithm weak spots. During the discussion, Dr. Lustgarten challenges specific biomarker weightings within the Bortz algorithm—focusing on Total Cholesterol, Sex Hormone-Binding Globulin (SHBG), Mean Corpuscular Hemoglobin (MCH), and Alanine Aminotransferase (ALT). Penalized linear models assume monotonic associations between biomarkers and mortality, failing to account for non-linear, U-shaped, or J-shaped risk curves common in gerontological biology. For instance, very low total cholesterol or abnormally low ALT often signals underlying frailty, subclinical disease, or sarcopenia rather than youthful vitality. Consequently, while the Bortz clock offers a highly scalable, cost-effective tool for population-level healthspan tracking, individual users must interpret biomarker coefficients critically: artificially manipulating specific blood parameters to lower a composite clock score does not necessarily reflect true systemic tissue rejuvenation.

II. Insight Bullets

  1. Large-Scale Derivation Cohort: The Bortz biological age clock was trained on 306,116 middle-aged to older individuals (aged 37–73 years) from the UK Biobank, providing high statistical power for biomarker discovery (Bortz et al., 2023).
  2. Elastic-Net Cox Modeling: The algorithm implements an Elastic-Net penalized Cox proportional-hazards model, narrowing 60 candidate circulating biomarkers down to a core ensemble of 25 stably selected predictors.
  3. Outperforming PhenoAge: On holdout test datasets, the Bortz clock achieved a C-index of 0.778 compared to 0.750 for Levine’s PhenoAge, representing an 11% relative increase in predictive performance for all-cause mortality (Levine et al., 2018).
  4. Predictive Lift Advantage: Incorporating the 25-biomarker Bortz panel provided up to 2.46 times the predictive lift over baseline age-and-sex null models.
  5. Cystatin C Primacy: Cystatin C emerged as the single strongest blood biomarker predictor of biological age acceleration, capturing glomerular filtration and systemic microvascular health (Bortz et al., 2023).
  6. Wide Variance in Biological Age Acceleration: Calculated Biological Age Acceleration (BAA) values ranged between -20 years younger and +20 years older than chronological age across same-aged individuals.
  7. Cost and Throughput Superiority: Utilizing standard circulating blood chemistry markers provides major cost, speed, and clinical accessibility advantages over expensive multi-omic platforms (such as DNA methylation or proteomics).
  8. Imputation Resilience: The authors demonstrated that missing blood panel markers can be imputed using clinical covariance structures without significantly degrading mortality prediction accuracy.
  9. Stratified Morbidity Performance: The Bortz model maintained predictive accuracy when stratified across both healthy individuals and participants with pre-existing chronic conditions (Bortz et al., 2023).
  10. Monotonic Modeling Blind Spots: Penalized linear Cox regression assumes linear risk associations, making the algorithm blind to U-shaped or J-shaped risk curves typical of biological aging parameters.
  11. The Total Cholesterol Paradox: In older adults, total cholesterol exhibits a U-shaped mortality curve where extremely low total cholesterol correlates with frailty, subclinical disease, and heightened mortality risk.
  12. Sex Hormone-Binding Globulin (SHBG) Complexity: While SHBG rises with age, elevated SHBG can simultaneously reflect favorable metabolic insulin sensitivity and unfavorable depletion of bioavailable free sex steroids or frailty.
  13. Red Blood Cell Indices (MCH and MCV): Mean Corpuscular Hemoglobin (MCH) and Mean Corpuscular Volume (MCV) reflect erythrocyte maturation; elevations point toward B12/folate deficiency or alcohol exposure, while reductions signal microcytic iron deficiency.
  14. Alanine Aminotransferase (ALT) Sarcopenia Masking: Extremely low serum ALT levels in elderly individuals frequently reflect diminished muscle mass (sarcopenia) or reduced hepatic volume rather than optimal liver health.
  15. Systemic Inflammaging Panel: The Bortz clock integrates high-sensitivity C-Reactive Protein (hsCRP), neutrophil count, monocyte count, and lymphocyte percentage to quantify chronic low-grade systemic inflammation.
  16. Metabolic and Glycemic Profiling: Glycated hemoglobin (HbA1c), fasting glucose, alkaline phosphatase (ALP), and gamma-glutamyl transferase (GGT) track glycemic dysregulation, bone turnover, and hepatobiliary stress.
  17. Renal Clearance Panel: Combining Cystatin C, Creatinine, and Urea establishes multi-parametric monitoring of glomerular filtration and nitrogenous waste excretion.
  18. Nutritional Acute-Phase Biomarkers: Serum Albumin and 25-hydroxyvitamin D serve as negative acute-phase reactants and nutritional markers; low levels strongly correlate with frailty and mortality.
  19. Apolipoprotein A1 Integration: Measuring ApoA1 captures high-density lipoprotein (HDL) particle functionality and reverse cholesterol transport efficiency better than standard total HDL-C alone.
  20. Commercial Direct-to-Consumer Translation: The Bortz clock was translated into commercial practice via the consumer health platform Humanity Inc., enabling direct-to-consumer healthspan tracking.
  21. Clock Gaming vs. True Biological Reversal: Artificially manipulating single blood markers via targeted supplementation can lower a composite algorithm score without reversing underlying tissue decay.
  22. Requirement for Interventional Trials: Prospective interventional trials are required to confirm whether reversing biological age clock scores leads to tangible reductions in disease incidence or lifespan extension.

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Evidence)

Protocols backed by large-scale biobank cohorts, machine learning risk modeling, and established clinical trial data.

  • Standardized Comprehensive Blood Biomarker Panel:
    • Evidence Level: Level A Meta-Analysis / Biobank Cohort Studies (Bortz et al., 2023; Levine et al., 2018).
    • Protocol: Obtain routine complete blood count (CBC), comprehensive metabolic panel (CMP), lipid panel, Cystatin C, hsCRP, HbA1c, and 25(OH)D to baseline systemic physiological risk parameters.
  • Renal and Microvascular Function Optimization:
    • Evidence Level: Level A Meta-Analysis (Bortz et al., 2023).
    • Protocol: Maintain optimal Cystatin C (<0.9 mg/L) and eGFR by maintaining blood pressure <120/80 mmHg, avoiding chronic NSAID overuse, maintaining daily hydration, and limiting high-refined-salt intake.
  • Glycemic Control and Inflammaging Suppression:
    • Evidence Level: Level A Meta-Analysis (Levine et al., 2018).
    • Protocol: Maintain HbA1c <5.4% and hsCRP <1.0 mg/L via a diet focused on whole foods, regular physical activity, 7–9 hours of sleep, and elimination of refined carbohydrates.

Experimental Tier (Level C/D Evidence)

Protocols backed by prospective epidemiological modeling, clinical preprints, or expert opinion.

  • Algorithmic Biological Age Trajectory Tracking:
    • Evidence Level: Level C Prospective Epidemiological Modeling (Bortz et al., 2023).
    • Protocol: Track biological age using validated algorithms (Bortz Blood Age, PhenoAge) 1 to 2 times per year to monitor directional biological aging trajectories rather than fixating on single isolated scores.
  • Hepatic and Sarcopenia Autoregulation:
    • Evidence Level: Level C Observational Evidence.
    • Protocol: Monitor liver enzymes (ALT, GGT) and red blood cell metrics (MCV, MCH); evaluate low ALT (<15 U/L) in older adults as a potential indicator of sarcopenia requiring increased dietary protein intake and progressive resistance training.

Red Flag Zone (Safety Data Absent / High Risk)

Unverified, hazardous, or algorithmically flawed health practices.

  • “Gaming” Biological Age Clock Biomarkers via Target Suppressants:
    • Status: Debunked / Methodological Fallacy.
    • Risk Assessment: Taking unvetted supplements strictly to manipulate a single biomarker coefficient (e.g., driving total cholesterol or ALT below normal physiological ranges) risks inducing frailty, sarcopenia, or endocrine disruption.
  • Treating Composite Biological Age Scores as Absolute Clinical Diagnoses:
    • Status: Unvalidated Subgroup Application.
    • Risk Assessment: Relying on a single composite biological age number as an absolute diagnostic tool without analyzing specific organ system markers risks missing acute medical pathologies or overestimating healthspan.

Produced by Gemini 2.0 Flash

1 Like

Tracking And Trying To Optimize Oxidative Stress Biomarkers

I. Executive Summary

Dr. Mike Lustgarten evaluates the plasma methionine sulfoxide-to-methionine ratio (MetO/Met) as a dynamic clinical biomarker of systemic oxidative stress and biological aging. The biological premise rests on the susceptibility of the sulfur thioether moiety in methionine to oxidation by reactive oxygen species (ROS)—specifically hydrogen peroxide (H2​O2​)—yielding methionine sulfoxide diastereomers (Met-S-SO and Met-R-SO). Because cellular repair relies on the thioredoxin-dependent methionine sulfoxide reductase enzyme family (MsrA and MsrB), an elevated circulating MetO/Met ratio reflects a shift in net redox homeostasis. Epidemiological cross-sectional metabolomic profiling across human cohorts (ages 45–110) demonstrates an age-associated accumulation of this ratio (p<0.05, FDR<0.05).

To evaluate intra-individual modifiability, Lustgarten compiles longitudinal data across 26 discrete blood draws utilizing capillary blood self-collection coupled with liquid chromatography–mass spectrometry (LC-MS) metabolomics. Analytical deconstruction reveals meaningful biological signals alongside severe statistical and methodological vulnerabilities. First, the speaker demonstrates an initial correlation between MetO/Met and the phenotypic biological age estimator PhenoAge at n=10 (r=0.79,p=0.006), which subsequently collapsed into statistical insignificance at n=21(r=0.18,p=0.43), exemplifying the high rate of false-positive Type I errors inherent to low-powered N=1 time-series analyses. Second, an observed correlation between MetO/Met and combined innate immune cell counts (neutrophils + monocytes, r=0.54,p<0.05) aligns with the pathophysiological role of myeloperoxidase- and NADPH oxidase (NOX2)-derived ROS generation during immunosenescence.

However, the nutritional attribution framework exhibits critical translational gaps. While bivariate modeling suggested an inverse association between strawberry intake and MetO/Met (r=−0.48,p<0.05), multivariable calorie adjustment rendered this effect non-significant (p=0.14), isolating total caloric restriction as the dominant predictive variable. Furthermore, identifying isolated dietary components (e.g., watermelon and total fructose) via uncorrected ordinary least squares regression across hundreds of collinear dietary variables without False Discovery Rate (FDR) or Family-Wise Error Rate (FWER) control creates extreme vulnerability to data over-fitting. While tracking methionine redox kinetics offers legitimate geroscience utility, optimizing dietary regimens based on unadjusted single-subject observational correlations lacks randomized controlled trial validation.

II. Insight Bullets

  1. Methionine is an essential sulfur-containing amino acid with an electron-rich, oxidatively labile thioether group vulnerable to nucleophilic attack by ROS.
  2. Reaction of methionine with hydrogen peroxide (H2​O2​) or hydroxyl radicals (∙OH) oxidizes the sulfur atom to form a racemic mixture of methionine-S-sulfoxide and methionine-R-sulfoxide.
  3. The ratio of circulating plasma methionine sulfoxide to unoxidized methionine (MetO/Met) serves as a direct proxy for systemic oxidative macromolecular stress.
  4. Enzymatic reduction of protein-bound and free MetO back to native methionine is catalyzed by stereospecific methionine sulfoxide reductases: MsrA (S-form) and MsrB / fRMsr (R-form).
  5. Cross-sectional metabolomic data across human populations (ages 45–110) confirm that the plasma MetO/Met ratio increases monotonically as a function of chronological age (p<0.05,FDR<0.05).
  6. Age-associated upregulation of the MetO/Met ratio is mechanistically driven by both increased mitochondrial ROS leakage and progressive transcriptional/translational decline in endogenous MsrA/B activity.
  7. Longitudinal N=1 biomarker tracking across 26 timepoints demonstrated baseline MetO/Met averages of 0.061 (2023) and 0.068 (2024), subsequently declining to 0.048 (2025) and 0.045 (2026).
  8. Capillary blood self-collection devices utilizing micro-needle suction (e.g., Tasso) coupled with high-resolution LC-MS enable untargeted/semi-targeted plasma metabolomic surveillance.
  9. Pre-analytical variability—including ambient room-temperature exposure, clotting time, and ex vivo air exposure—can induce artificial ex vivo methionine auto-oxidation.
  10. The sum of circulating innate immune cells (neutrophils + monocytes) correlates positively with the plasma MetO/Met ratio (r=0.54,p<0.05,n=21).
  11. Activated neutrophils and monocytes generate high flux rates of superoxide (O2∙−​) via NADPH oxidase (NOX2) and hypochlorous acid (HOCl) via myeloperoxidase (MPO).
  12. Myeloperoxidase-derived oxidants selectively react with extracellular methionine residues in circulating plasma proteins (e.g., serum albumin Met-111 and Met-147).
  13. Bivariate correlation between MetO/Met and PhenoAge exhibited an initial spurious correlation (r=0.79,p=0.006at n=10) that degraded completely at n=21 (r=0.18,p=0.43).
  14. This statistical collapse provides empirical proof that low-sample-size observational N=1 time-series are dominated by random stochastic noise and regression to the mean.
  15. Failure to apply multiplicity corrections (e.g., Benjamini-Hochberg False Discovery Rate or Bonferroni adjustments) across 600+ monitored metabolites dramatically inflates experiment-wise Type I error rates.
  16. Discarding FDR control under the premise of avoiding false negatives guarantees the retention of spurious dietary correlations.
  17. Aligning rolling 30-to-50-day weighted dietary averages with discrete blood testing timepoints assumes steady-state tissue metabolite kinetics, ignoring acute postprandial swings.
  18. High daily intake of strawberries (up to 600–1,200 g/day) demonstrated an initial unadjusted inverse correlation with MetO/Met (r=−0.48,p<0.05).
  19. Multivariable regression adjusting for total daily caloric intake completely eliminated the statistical significance of strawberry intake on MetO/Met (p=0.14).
  20. Total daily caloric intake was identified as the underlying confounding variable driving the apparent strawberry-redox association.
  21. Caloric restriction down-regulates mitochondrial electron transport chain proton leak, decreasing baseline mitochondrial H2​O2​ generation and lowering substrate oxidation.
  22. After multivariable calorie adjustment, daily watermelon intake and total dietary fructose intake retained nominal inverse associations with the MetO/Met ratio (p<0.05).
  23. Watermelon is rich in L-citrulline, a non-essential amino acid that bypasses hepatic first-pass metabolism to drive de novo endothelial L-arginine synthesis and nitric oxide (NO) bioavailability.
  24. Free dietary fructose is absorbed via facilitated diffusion via GLUT5 enterocyte transporters and rapidly cleared by hepatic fructokinase (KHK).
  25. High-flux hepatic fructose metabolism bypasses phosphofructokinase regulation, potentially depleting intracellular ATP and generating uric acid via AMP deaminase activation.
  26. Attributing systemic anti-oxidative efficacy directly to isolated dietary fructose represents a high risk of nutritional reverse causality and model over-fitting.
  27. Chronic high-dose fruit fructose consumption in individuals without high metabolic output can induce hepatic de novo lipogenesis and hypertriglyceridemia.
  28. Whole-food strawberry supplementation (32 g freeze-dried powder) has been shown in clinical RCTs to improve endogenous glutathione (GSH) and SOD activity in prediabetic cohorts.
  29. Polyphenolic compounds in berries (e.g., anthocyanins, pelargonidin, fisetin) act primarily through xenohormetic activation of the Keap1-Nrf2-ARE signaling pathway rather than direct radical scavenging.
  30. Nrf2 nuclear translocation transcriptionally upregulates GCLC, GCLM, NQO1, and thioredoxin reductase (TrxR), enhancing cellular Msr catalytic turnover.
  31. The speaker’s composite metric (“net correlative score”) summing unweighted bivariate biomarker correlations lacks epidemiological validity and predictive modeling calibration.
  32. Treating an unvalidated metabolomic ratio as a primary optimization endpoint risks “Goodhart’s Law,” wherein optimizing a surrogate metric compromises systemic physiological homeostasis.
  33. Lowering calorie intake combined with increasing whole-food fruit consumption alters multiple collinear metabolic vectors simultaneously (e.g., fasting insulin, lipid subfractions, glycemic variability).
  34. Methionine restriction per se (independent of total calories) has been robustly shown in rodent models to downregulate mTORC1, upregulate FGF21, and extend lifespan.
  35. Translating single-subject plasma amino acid redox dynamics into population-level longevity protocols requires prospective crossover validation against verified clinical outcomes.

III. Adversarial Claims & Evidence Table

Claim from Video / Regimen Context Speaker’s Evidence / Justification Scientific Reality (Current Clinical Data) Evidence Grade Verdict
Plasma MetO/Met ratio is a valid biomarker of systemic oxidative stress and aging. Cross-sectional metabolomic data (ages 45–110) showing an age-related increase (p<0.05,FDR<0.05). Confirmed. Methionine oxidation on circulating proteins (e.g., albumin Met-111/147) and free plasma amino acids increases in biological aging, renal failure, and vascular disease due to reduced MsrA/Bcapacity (Flores et al., 2025; Redox Biol, 2021). Level C Strong Support
MetO/Met ratio correlates with innate immune aging (neutrophils + monocytes). Longitudinal N=1tracking showing positive correlation (r=0.54,p<0.05,n=21). Pathophysiologically sound. Activated neutrophils/monocytes release H2​O2​ and MPO-derived HOCl, which rapidly oxidize circulating methionine; neutrophil-to-lymphocyte dynamics track biological aging (MDPI Cohort, 2025; PMC12811150). Level C Plausible
Elevated MetO/Met ratio reliably predicts advanced biological age (PhenoAge). Initial n=10 correlation (r=0.79,p=0.006) presented as evidence of biological aging acceleration. Refuted by the speaker’s own updated data at n=21 (r=0.18,p=0.43). The initial correlation was an artifact of small sample size (n=10) and autocorrelation noise in an underpowered N=1 dataset (Liu et al., 2018). Level C Unsupported (Spurious Noise)
Excluding False Discovery Rate (FDR) correction is optimal for discovery in N=1 data. Premise: FDR is overly conservative and excludes potentially meaningful dietary correlations. Methodologically flawed. Analyzing hundreds of collinear dietary variables against multi-omic outcomes without multiplicity control (Benjamini-Hochberg) inflates family-wise Type I error rates to near 100%, generating false discoveries (Ioannidis, 2005). Level A Unsupported (Methodological Error)
High strawberry consumption directly reduces systemic methionine oxidation. Bivariate correlation (r=−0.48,p<0.05) between daily grams and MetO/Met ratio. Disproven after multivariable adjustment (p=0.14). Caloric restriction was the true confounding mediator. However, strawberry polyphenols do hormetically upregulate endogenous antioxidant enzymes (SOD, GSH) via Nrf2 (Groven et al., 2025). Level B Unsupported (Confounded by Caloric Intake)
Increasing dietary watermelon and fructose causally lowers systemic oxidative stress. Calorie-adjusted multivariable linear regression showing negative beta coefficients (p<0.05). Unproven and biochemically paradoxical. While watermelon provides L-citrulline and lycopene, high isolated fructose flux promotes hepatic ATP depletion and uric acid-mediated oxidative stress in non-athletic cohorts (Jensen et al., 2018). Level C Speculative
Moderate caloric restriction lowers systemic oxidative burden. Calorie intake correlated positively with MetO/Metratio in longitudinal N=1tracking. Robustly validated in human RCTs. The CALERIE Phase 2 trial confirmed that 12–25% caloric restriction significantly downregulates systemic F2-isoprostanes, inflammatory cytokines, and resting metabolic rate (Ravussin et al., 2015). Level B Strong Support

IV. Actionable Protocol (Prioritized)

====================================================================

CLINICAL & METABOLIC REDOX OPTIMIZATION FRAMEWORK

=====================================================================

[HIGH CONFIDENCE TIER: Level A/B Validated Clinical Protocols]

├── 1. Moderate Caloric Optimization (Eucaloric / Mild Energy Deficit):
│ ├── Target: 10–15% caloric reduction relative to maintenance energy expenditure (if overweight/over-fat).
│ ├── Rationale: Mitigates electron transport chain electron leakage, reducing steady-state H2O2 production.
│ └── Biomarker Endpoints: Fasting insulin, hs-CRP, HOMA-IR, and systemic lipid peroxides.

├── 2. Whole-Food Dietary Polyphenol Integration:
│ ├── Foods: Berries (strawberries, blueberries, blackberries) at 150–300 g/day.
│ ├── Mechanism: Xenohormetic activation of Keap1-Nrf2-ARE transcription; upregulates endogenous GSH and SOD.
│ └── Precaution: Whole intact fruit preferred over extracts or isolated fructose syrups.

├── 3. Regular Complete Blood Count (CBC) Differential Monitoring:
│ ├── Metric: Monitor absolute neutrophil and monocyte counts for baseline subclinical inflammation.
│ └── Target: Maintain physiological homeostasis without unexplained persistent leukocytosis.

[EXPERIMENTAL TIER: Level C/D Evidence / Single-Subject Geroscience Tracking]

├── 1. Plasma Metabolomic Redox Surveillance (LC-MS):
│ ├── Marker: Plasma MetO/Met ratio and oxidized albumin fractions (Met-111/147).
│ ├── Protocol: Fasted, standardized pre-analytical blood handling to eliminate ex vivo artifactual oxidation.
│ └── Frequency: Quarterly or semi-annual testing to establish long-term moving averages.

├── 2. Endothelial Nitric Oxide Precursor Optimization:
│ ├── Source: L-citrulline-rich whole foods (watermelon) or dietary nitrates (leafy greens, beetroot).
│ └── Target: Enhance endothelial nitric oxide synthase (eNOS) coupling and microvascular perfusion.

[RED FLAG ZONE: Debunked, Unsafe, or Methodologically Vulnerable Practices]

├── 1. Uncorrected N=1 Multi-Hypothesis Testing:
│ ├── Practice: Running unadjusted regressions across 100+ dietary variables without FDR/Bonferroni corrections.
│ └── Risk: Chasing false-positive statistical noise (Type I errors), leading to erroneous dietary changes.

├── 2. High-Dose Isolated Fructose Consumption for Antioxidant Optimization:
│ ├── Practice: Intentionally elevating free fructose intake under the assumption that it lowers oxidative stress.
│ └── Risk: Hepatic de novo lipogenesis, hepatic steatosis, uric acid elevation, and metabolic dysfunction.

├── 3. Over-Optimization of a Single Intermediate Metabolite (Goodhart’s Law):
│ └── Risk: Distorting overall dietary macronutrient quality to manipulate an unvalidated plasma ratio.

========================================================================

V. Technical Mechanism Breakdown

1. Methionine Oxidation and the Stereospecific Msr Repair Network

  • Chemical Oxidation: Methionine possesses a hydrophobic thioether side chain (−CH2​−CH2​−S−CH3​). In the presence of physiological oxidants (H2​O2​, HOCl, peroxynitrite ONOO−), the unshared electron pair on the sulfur atom undergoes nucleophilic reaction, converting the uncharged thioether into a polar sulfoxide (−S(=O)−CH3​). This reaction introduces a chiral center at the sulfur atom, generating equimolar quantities of two diastereomers: L-methionine-S-sulfoxide (Met-S-SO) and L-methionine-R-sulfoxide (Met-R-SO).
  • Enzymatic Reduction Cascade: Cells possess specialized enzymes to reverse this post-translational modification:
    1. MsrA: A thioredoxin-dependent reductase stereospecifically targeted to Met-S-SO in both free amino acid pools and intact polypeptides. The catalytic cycle involves a nucleophilic attack by an active-site cysteine (Cys72 in human MsrA), forming a sulfenic acid intermediate, followed by condensation with a resolving cysteine to form an intramolecular disulfide bond, releasing native methionine.
    2. MsrB (MsrB1, MsrB2, MsrB3): Catalyzes the stereospecific reduction of protein-bound Met-R-SO. MsrB1is a selenoprotein containing a selenocysteine (Sec) residue in its catalytic triad, conferring high catalytic efficiency.
    3. Free Methionine-R-Sulfoxide Reductase (fRMsr): Specifically reduces the unbonded, free amino acid pool of Met-R-SO.
  • The Thioredoxin/NADPH Axis: Inactive, oxidized Msr enzymes containing intramolecular disulfide bonds are regenerated by reduced Thioredoxin (Trx). Oxidized Trx is subsequently reduced by Thioredoxin Reductase (TrxR) at the expense of cytosolic NADPH, directly coupling methionine repair to cellular pentose phosphate pathway flux.

2. Statistical Multiplicity and Methodological Pitfalls in Single-Subject (N=1) Time-Series

  • The Multiplicity Problem: Testing associations between hundreds of dietary/lifestyle variables and broad metabolomic panels without multiple-testing corrections drastically inflates the Family-Wise Error Rate (FWER). Under an alpha threshold of α=0.05, testing m=100 independent hypotheses yields a probability of at least one false positive of:

FWER=1−(1−0.05)100≈0.994(99.4%)

  • Confounding and Autocorrelation in N=1 Modeling: Longitudinal measurements taken from a single individual over time violate the assumption of independent and identically distributed (i.i.d.) observations due to serial autocorrelation. Confounding variables that track globally with dietary shifts—specifically total energy intake, macronutrient distribution, and seasonal exercise variations—inevitably generate strong but non-causal correlations with intermediate metabolic biomarkers.

Produced by Gemini 2.5 Pro

1 Like

Mitochondrial Transplantation Rejuvenates Immune Cells

I. Executive Summary

Immunosenescence and age-associated systemic pathology are fundamentally driven by mitochondrial decay, characterized by the progressive accumulation of pathogenic mitochondrial DNA (mtDNA) heteroplasmy, electron transport chain (ETC) uncoupling, elevated reactive oxygen species (ROS) generation, and the loss of mitochondrial cristae architecture. In adaptive immune compartments, aged CD4+ T lymphocytes exhibit diminished oxidative phosphorylation (OXPHOS), impaired interleukin-2 (IL-2) secretion, reduced clonal proliferation, and elevated markers of cellular exhaustion (PD-1, Tim-3) and senescence (p16INK4a, senescence-associated beta-galactosidase, CD57). This bioenergetic collapse directly undermines host defenses against viral (e.g., Influenza) and intracellular bacterial (e.g., Mycobacterium tuberculosis) pathogens.

To resolve these translational roadblocks, Dr. Colwyn Headley and colleagues established an ex vivo centrifugal co-incubation protocol capable of transplanting respiration-competent, healthy allogeneic mitochondria isolated from donor fibroblasts into aged, exhausted CD4+ T cells. This rapid (5-minute) physical internalization process restores basal and maximal oxygen consumption rates (OCR), normalizes electron paramagnetic resonance (EPR)-measured superoxide production, and reconstructs inner mitochondrial cristae density. Functionally, transplanted CD4+ T cells regain proliferative capacity, upregulate activation markers (CD69, CD25), and suppress senescence and exhaustion signatures in vitro. Adoptive transfer of these biogenetically restored lymphocytes into immunocompromised (Rag1−/− and Tcr−/−) mice significantly reduces pathogen burden and enhances survival following lethal influenza challenge and chronic M. tuberculosis infection (Headley et al., 2024).

To transition from ex vivo cell therapy to direct in vivo therapeutics, Headley’s group developed Antibody-Mitochondria Conjugates (AMCs). By functionalizing the outer mitochondrial membrane with monoclonal antibodies targeting specific cell-surface receptors (e.g., anti-CD31 for vascular endothelial cells; anti-CD11a/LFA-1 for pan-leukocyte targeting), AMCs achieve receptor-mediated endocytic uptake with high tissue specificity and near 100% internalization efficiency in vitro. In mtDNA-deficient (ρ0) cellular models auxotrophic for pyrimidines, AMC transfer rescues endogenous oxidative phosphorylation, restores mitochondrial ATP production, and sustains long-term proliferation in the absence of exogenous uridine supplementation (Frontiers in Endocrinology, 2017).

While preclinical non-human primate (marmoset) studies demonstrate preliminary safety and tolerability of repeat systemic AMC dosing without acute systemic inflammation, major translational gaps persist. Critical concerns include potential damage-associated molecular pattern (DAMP) release, cGAS-STING-mediated inflammatory cascades, allogeneic mtDNA haplogroup immunogenicity, oncogenic metabolic exploitation, and the absence of completed Phase II/III randomized controlled trials.

II. Insight Bullets

  1. Pathogenic ROS Debt Cycle: Age-dependent electron leakage at ETC Complexes I and III elevates superoxide generation, overwhelming endogenous antioxidant defenses (SOD, catalase, GPx) and damaging error-prone mitochondrial DNA polymerase gamma (POLG), thereby driving irreversible pathogenic mtDNA heteroplasmy.
  2. Bioenergetic Decay in Aged CD4+ T Cells: Chronologically aged CD4+ T lymphocytes demonstrate significant reductions in spare respiratory capacity and OXPHOS, directly correlating with blunted activation marker expression (CD69, CD25) and suppressed IL-2 secretion.
  3. Simplicity of Centrifugal Ex Vivo Mito-Transfer: Co-centrifuging isolated donor mitochondria with target lymphocytes for 5 minutes achieves rapid, scalable, and high-efficiency internalization without requiring viral vectors, chemical permeabilization, or electroporation.
  4. Ultrastructural Cristae Remodeling: Post-transplantation transmission electron microscopy confirms the physical restoration of inner mitochondrial membrane cristae organization and dense matrix architecture in previously vacuolated, aged T cells.
  5. Simultaneous OXPHOS Elevation and ROS Suppression: Seahorse respirometry paired with electron paramagnetic resonance (EPR) spin trapping demonstrates that mitochondrial transplantation elevates basal oxygen consumption while concurrently reducing net superoxide flux (Headley et al., 2024).
  6. Phenotypic Reversal of T-Cell Exhaustion: Exogenous mitochondrial uptake significantly downregulates immune checkpoint exhaustion markers, specifically programmed cell death protein 1 (PD-1) and T-cell immunoglobulin and mucin-domain containing-3 (Tim-3), following chronic antigenic stimulation.
  7. Suppression of Classical Senescence Markers: Rejuvenated elderly human CD4+ T cells show marked declines in senescence-associated beta-galactosidase (SA-β-gal) activity, p16INK4a expression, and the terminal differentiation marker CD57.
  8. In Vivo Protection Against Lethal Viral Challenge: Adoptive transfer of mito-transplanted CD4+ T cells into Rag1−/− mice confers significant survival advantages against lethal influenza infection compared to untreated aged T cells.
  9. Bacterial Clearance in Chronic Infection: In murine models of Mycobacterium tuberculosis, mito-rejuvenated T-cell transfer drives superior bacterial containment and reduces colony-forming units (CFUs) within pulmonary and splenic tissues.
  10. Limitations of Unmodified Systemic Bolus Injections: Unconjugated intravenous administration of isolated naked mitochondria exhibits poor target-tissue biodistribution, low cell-type specificity, and rapid clearance by the reticuloendothelial system.
  11. Antibody-Mitochondria Conjugates (AMCs): Functionalizing the outer mitochondrial membrane with target-specific antibodies (e.g., anti-CD31) generates an “active guidance” delivery system that achieves cell-selective receptor-mediated endocytosis.
  12. Endothelial Targeting via CD31 AMCs: Conjugating anti-CD31 to donor mitochondria facilitates selective internalization into vascular endothelial cells in mixed co-cultures containing non-target vascular smooth muscle cells.
  13. Pan-Leukocyte In Vivo Targeting via CD11a: Surface-conjugating anti-CD11a (integrin alpha L / LFA-1) enables direct in vivo systemic targeting of circulating and tissue-resident leukocyte populations without requiring ex vivocell manipulation.
  14. Biochemical Rescue of ρ0 (mtDNA-Deficient) Auxotrophy: In ρ0 cells lacking functional ETC-linked dihydroorotate dehydrogenase (DHODH), AMC-mediated transfer permanently rescues pyrimidine synthesis and restores proliferation in uridine-depleted media (Frontiers in Endocrinology, 2017).
  15. Uridine as a Metabolic Bypass Rather than Rejuvenator: Supplemental uridine restores nuclear DNA replication in respiration-deficient cells by supplying downstream pyrimidines, but completely fails to restore OXPHOS, mitochondrial membrane potential, or aerobic ATP generation.
  16. Intercellular Mitochondrial Sharing: Confocal microscopy demonstrates that recipient immune cells establish secondary mitochondrial transfer networks via tunneling nanotubes (TNTs), microvesicles, and exosomal extrusion to distribute donor organelles to neighboring cells.
  17. Dicarboxylate Fatty Acid (DCFA) Biomarker Utility: Elevated intracellular and circulating dicarboxylic fatty acids indicate peroxisomal/microsomal omega-oxidation compensation secondary to failed mitochondrial beta-oxidation, serving as an indirect omic proxy for donor organelle functional screening.
  18. Decoupling Metabolic Signaling from Respiration: Engineered mitochondria offer a therapeutic chassis to modulate cell fate by delivering customized enzymatic circuits (e.g., metabolite production, ROS scavenging) independently of maximal ATP synthesis.
  19. Intercellular Telomere Vesicle Synergy: Parallel biological frameworks demonstrate that antigen-presenting cells (APCs) transfer intact telomeres via extracellular vesicles to prevent T-cell senescence (Lanna et al., 2022), establishing that organelle/macromolecular transfer is an endogenous physiological rejuvenation pathway.
  20. Primate Pharmacokinetics and Dosing Kinetics: Longitudinal 8-week dosing regimens of anti-CD11a AMCs in aged marmosets (Callithrix jacchus, equivalent to human 60–65 years) establish baseline tolerability, cellular kinetics, and absence of acute systemic shock.
  21. Cardiovascular Applications in Aortic Aneurysm (AAA): Because mitochondrial breakdown across endothelial and vascular smooth muscle layers is a primary driver of abdominal aortic aneurysm development, targeted vascular AMC delivery represents a potential structural intervention.
  22. Cosmic Radiation Mitigation: For deep-space environments where cosmic radiation induces generalized systemic mitochondrial failure across all tissue beds, bioengineered, radioprotected organelle resupply provides a hypothetical countermeasure.
  23. Allogeneic Engraftment and Haplogroup Compatibility: While acute allogeneic transplantation demonstrates short-term functional uptake in vitro, long-term persistence in immunocompetent hosts requires matching mitochondrial haplogroups to prevent allo-immune rejection or mito-nuclear incompatibility.
  24. DAMP Cascades and Sterile Inflammation Risk: Disrupted, unsealed, or poorly purified mitochondrial preparations release formyl peptides and unmethylated CpG mtDNA motifs, potent damage-associated molecular patterns (DAMPs) that trigger TLR9 and cGAS-STING inflammatory pathways (West & Shadel, 2017).
  25. The Threat of “Mito-Doping” in Athletics: Systemic or intramuscular mitochondrial administration represents an undetectable performance-enhancing modality that mirrors endurance training-induced mitochondrial biogenesis without detectable foreign synthetic metabolites.
  26. Futility of Whole-Body Total Organelle Replacement: Systemic rejuvenation does not require replacing mitochondria in every somatic cell; strategic rejuvenation of mobile sentinel pools (e.g., CD4+ T cells, macrophages) generates systemic downstream longevity benefits via immune clearance and secondary organelle sharing.

IV. Actionable Protocol (Prioritized)

`========================================================================

                ACTIONABLE PROTOCOL: SYNTHESIZED FRAMEWORK

=========================================================================

[HIGH CONFIDENCE TIER] → Level A/B Evidence (Empirically Validated)
[EXPERIMENTAL TIER] → Level C/D Evidence (Plausible / High Safety Margin)
[RED FLAG ZONE] → Debunked / Lacks Safety Data (“Safety Data Absent”)

=========================================================================

1. High Confidence Tier (Backed by Level A/B Evidence)

  • Local Autologous Mitochondrial Transplantation for Acute Ischemia-Reperfusion Injury:
    • Protocol: Direct localized injection of freshly harvested autologous skeletal muscle mitochondria into ischemic myocardium immediately prior to or during surgical reperfusion (e.g., pediatric congenital cardiac repair, coronary bypass).
    • Evidence: Demonstrated in clinical Phase I safety trials and extensive large-animal models to improve left ventricular ejection fraction, decrease myocardial necrosis, and reduce mechanical support dependency (Emani et al., 2017; JCI, 2018).
  • Exercise-Induced Endogenous Mitochondrial Biogenesis (PGC-1α Activation):
    • Protocol: Implement periodized high-intensity interval training (HIIT) paired with Zone 2 endurance training (3–4 sessions weekly) to activate the AMPK/SIRT1/PGC-1α signaling axis, accelerating mitochondrial biogenesis, cristae remodeling, and mitophagy in skeletal muscle and circulating leukocytes.
    • Evidence: Extensive Level A meta-analyses demonstrate enhanced mitochondrial volume density, improved maximal oxygen uptake (VO2 max), and reduced systemic oxidative stress in aging populations (Lundby & Jacobs, 2016).

2. Experimental Tier (Level C/D Evidence, High Safety Margin)

  • Ex Vivo Autologous Immune Cell Mitochondrial Loading Prior to Cell Therapy:
    • Protocol: Centrifugal loading of young autologous or haplogroup-matched donor mitochondria into harvested patient peripheral blood mononuclear cells (PBMCs) or CAR-T cells ex vivo prior to reinfusion to reverse exhaustion and enhance longevity of cell-based therapies.
    • Evidence: Preclinical rodent and ex vivo human data confirm the reversal of CD4+ exhaustion markers and improved pathogen clearance (Headley et al., 2024); systematic clinical efficacy trials in human longevity remain pending.
  • Uridine Triacetate / Monophosphate in Clinically Diagnosed Mitochondrial Syndromes:
    • Protocol: Targeted oral uridine supplementation (e.g., 500–1000 mg daily) to bypass pyrimidine synthesis defects in confirmed cases of mitochondrial encephalopathy or severe respiratory chain mutations.
    • Evidence: Level C clinical case series and biochemical models show pyrimidine rescue; however, uridine does not improve baseline OXPHOS or systemic longevity in healthy cohorts.
  • Targeted Antibody-Mitochondria Conjugates (AMCs) for Endothelial/Immune Rejuvenation:
    • Protocol: Intravenous delivery of anti-CD31 or anti-CD11a functionalized mitochondria to treat vascular endothelial breakdown or severe immunosenescence.
    • Evidence: Level D (in vitro and non-human primate pilot safety studies). High biological plausibility, but full pharmacokinetics and clinical regulatory parameters are currently in development.

PAI-1 Impacts Telomere Length, Cell Senescence, And Longevity

I. Executive Summary

Plasminogen activator inhibitor-1 (PAI-1), encoded by the SERPINE1 gene, serves as a primary physiological inhibitor of tissue-type (tPA) and urokinase-type (uPA) plasminogen activators. While canonically recognized for regulating fibrinolysis, recent translational investigations establish PAI-1 as a pleiotropic upstream regulator of organismal aging, cardiovascular integrity, cellular senescence, and metabolic homeostasis. Clinical genetics data from the Old Order Amish founder kindred harboring a rare loss-of-function null allele (SERPINE1 c.699_700dupTA) indicate that life-long heterozygous deficiency (~50% reduction in circulating antigen) is causatively associated with a ~10-year lifespan extension, a 10% increase in leukocyte telomere length, enhanced insulin sensitivity, significant protection from type 2 diabetes mellitus, and preserved aortic elasticity.

The biological actions of PAI-1 exhibit an essential biphasic (“Goldilocks”) profile across mammalian physiology. Pathological upregulation of PAI-1—frequently triggered by obesity, chronic low-grade inflammation, and TGF-β signaling—accelerates vascular stiffening, arterial thrombosis, metabolic syndrome, and multi-organ fibrosis. At the cellular level, PAI-1 drives both cell-autonomous senescence via the stabilization of nuclear p53 and retention of cyclin D1, and non-cell-autonomous senescence via impaired plasmin-mediated proteolysis of insulin-like growth factor binding protein-3 (IGFBP-3). Furthermore, PAI-1 elevates programmed death-ligand 1 (PD-L1) expression, suppressing immune-mediated surveillance and clearance of senescent cell populations. Conversely, complete genetic absence (homozygous null state) provokes moderate bleeding diatheses and spontaneous, progressive cardiac fibrogenesis, precluding uncalibrated total suppression strategies.

Translational findings from CRISPR/Cas9-engineered heterozygous murine models mirror human kindred metrics, demonstrating a ~50% reduction in circulating PAI-1, significant mitigation of age-dependent pulse wave velocity (PWV) increases, and an approximate 20% extension in median lifespan. Moreover, independent multi-omic profiling via the DNA methylation GrimAge clock underscores that the DNAm PAI-1 surrogate marker stands as the strongest single epigenetic predictor of all-cause mortality, cardiovascular morbidities, and metabolic dysfunction. Pharmacological modulation using targeted, selective small-molecule PAI-1 inhibitors (such as TM5614) represents an emerging geroprotective paradigm; however, translation into human longevity therapeutics demands strict therapeutic window calibration to prevent compromised tissue repair and hemostatic liabilities.

II. Insight Bullets

  1. Heterozygous carriers of the SERPINE1 null mutation exhibit an approximate 10% increase in leukocyte telomere length relative to unaffected kindred, as detailed by Khan et al., 2017.
  2. Human heterozygous SERPINE1 loss-of-function is associated with an extended lifespan of approximately one decade in the Berne, Indiana Amish kindred.
  3. Heterozygous carriers demonstrate lower fasting plasma insulin and lower hemoglobin A1c concentrations compared to non-carrier kindred.
  4. Diabetes prevalence in heterozygous SERPINE1 carriers is statistically negligible (~1%) relative to the 8–10% baseline observed in unaffected Midwestern kindred.
  5. Circulating proprotein convertase subtilisin/kexin type 9 (PCSK9) concentrations are reduced in heterozygous carriers and minimized in homozygous null individuals.
  6. PAI-1 biological activity follows a strict bell-shaped dose-response curve, wherein both excessive and completely absent levels yield significant pathology.
  7. Elevated systemic PAI-1 accelerates cardiovascular aging, vascular thrombosis, metabolic syndrome, emphysema, and cognitive impairment.
  8. Chronically high PAI-1 expression correlates with increased risk and poor prognosis across multiple malignancies, including gastric, pancreatic, ovarian, and triple-negative breast cancers.
  9. Homozygous complete absence of PAI-1 causes bleeding diatheses and drives spontaneous myocardial scarring and fibrotic deposition in both humans and mice.
  10. Total PAI-1 deletion disrupts innate immune responses and compromises physiological tissue wound healing mechanisms.
  11. PAI-1 acts as a master regulator of extracellular and pericellular peptide processing by inhibiting serine proteases tPA and uPA.
  12. PAI-1 prevents the proteolytic degradation of IGFBP-3 by plasminogen activators, directly amplifying senescent signaling cascades.
  13. Proteolytic conversion of pro-BDNF into mature BDNF by tPA/plasmin is inhibited by elevated PAI-1, directly impairing synaptic plasticity and memory formation (ACS Omega).
  14. PAI-1 inhibits the enzymatic cleavage and activation of hepatocyte growth factor (HGF), restraining regenerative cellular proliferation.
  15. Extracellular PAI-1 directly influences systemic lipid metabolism through proteolytic modulation of liver receptors and processing proteins.
  16. PAI-1 exerts cell-autonomous senescence control by promoting the nuclear stabilization of the tumor suppressor protein p53.
  17. Intracellular PAI-1 signaling induces the nuclear retention of cyclin D1, precipitating cell cycle arrest and suppressing cellular proliferation.
  18. PAI-1 upregulates the cell-surface expression of PD-L1, promoting an immunosuppressive microenvironment that shields senescent cells from immune-mediated clearance (PMC12552379).
  19. Human SERPINE1 heterozygotes preserve aortic compliance across chronological age, maintaining significantly lower aortic pulse wave velocity (PWV) as published by Khoddam et al., 2025.
  20. CRISPR/Cas9-engineered heterozygous Serpine1 mice replicate human phenotypes, exhibiting a 50% decrease in plasma PAI-1 and reduced age-associated PWV elevation.
  21. Heterozygous gene targeting of Serpine1 extends the median lifespan of laboratory mice by approximately 20%.
  22. The DNA methylation surrogate marker DNAm PAI-1 within the GrimAge clock serves as the single strongest epigenetic predictor of all-cause mortality, according to Lu et al., 2019.
  23. High DNAm PAI-1 scores independently predict time-to-coronary heart disease, heart failure onset, and multi-morbidity accumulation.
  24. Epigenetic PAI-1 estimators outperform direct single-point plasma PAI-1 measurements in predicting long-term morbidity and early age at menopause.
  25. Mathematical derivation of the GrimAge clock independently arrived at PAI-1 biology without prior heuristic biomarker assumptions.
  26. Pharmacological small-molecule PAI-1 inhibitors such as TM5614/RS5614, pioneered at Tohoku University, demonstrate senescence-modulating and geroprotective efficacy in pre-clinical models.
  27. Experimental small-molecule PAI-1 inhibition rescues aortic elastic lamina degradation and mitigates cellular senescence in Klotho-deficient mice.
  28. PAI-1 functions as both a downstream component of the senescence-associated secretory phenotype (SASP) and an upstream causative inducer of cellular senescence.
  29. Suppression of endothelial nitric oxide synthase (eNOS) by elevated PAI-1 diminishes nitric oxide bioavailability, exacerbating arterial stiffness.
  30. Therapeutic longevity strategies must aim for moderate, partial (~50%) PAI-1 downregulation rather than total pharmacological ablation.

III. Adversarial Claims & Evidence Table

Claim from Video Speaker’s Evidence Scientific Reality (Current Data) Evidence Grade (A–E) Verdict
1. Heterozygous SERPINE1 null mutation extends human lifespan by ~10 years 2017 Berne Amish kindred observational genetics study. Confirmed in the Amish founder cohort (n=177; 43 heterozygotes) showing ~10-year longer median survival (Khan et al., 2017). Broad generalizability across ethnically diverse cohorts remains unconfirmed in large-scale multi-ethnic GWAS. Level C Plausible
2. Heterozygous PAI-1 deficiency prolongs leukocyte telomere length by ~10% Leukocyte telomere Southern blot/qPCR assays from Amish kindred. Statistically verified in carrier cohort showing ~10% longer age-adjusted leukocyte telomeres (Khan et al., 2017). Direct causality vs. secondary preservation from lower metabolic stress remains debated. Level C Strong Support
3. PAI-1 haploinsufficiency protects against metabolic syndrome and Type 2 Diabetes 1 diabetic out of ~100 carriers vs. 8–10% in unaffected relatives; lower fasting insulin/HbA1c. Strong human observational and mechanistic validation. PAI-1 elevation is causatively linked to adipose insulin resistance and hepatic steatosis (Science Advances). Level C Strong Support
4. PAI-1 directly degrades or regulates systemic PCSK9 levels Lower circulating PCSK9 observed across carrier gradient; lowest in homozygous null. Pre-clinical and human cohort data confirm PAI-1 modulation alters hepatic lipid processing and downregulates PCSK9 expression via proteolysis and hepatic mRNA shifts (Scientific Reports). Level C / D Plausible
5. Complete loss of PAI-1 causes spontaneous myocardial fibrosis in humans and mice Clinical observations of homozygous patients; knock-out murine histology. Validated in both human homozygous SERPINE1loss-of-function and Serpine1 homozygous null murine lines, which exhibit microvascular bleeding, impaired cardiac repair, and subendocardial fibrosis (JCI). Level C / D Strong Support(Safety Critical)
6. PAI-1 inhibits BDNF maturation, impairing neuroplasticity and memory Biochemical pathway linking tPA-mediated pro-BDNF cleavage inhibition. Demonstrated in pre-clinical models and human neurological cohorts where elevated PAI-1/BDNF ratios correlate with cognitive decline and Alzheimer’s pathology (ACS Omega, 2023). Level C / D Plausible
7. PAI-1 drives senescence via IGFBP-3 retention, p53 stabilization, and cyclin D1 arrest In vitro cellular senescence models and molecular signaling assays. Mechanistically robust in cell culture and animal models. Extracellular IGFBP-3 cleavage is blocked by PAI-1; intracellular PAI-1 binds and stabilizes p53/cyclin D1 complexes (PMC12919670). Level D(Translational Gap) Plausible
8. PAI-1 upregulates PD-L1 to promote senescent immune evasion Tumor and senescent stromal cell immunological clearance assays. Supported by oncological and cellular senescence studies indicating PAI-1/STAT3 signaling increases PD-L1 surface density, preventing CD8+/NK clearance of senescent stroma (PMC12552379). Level D(Translational Gap) Plausible
9. Heterozygous Serpine1 CRISPR knockout increases murine lifespan by ~20% JCI publication detailing longevity curves in engineered mice. Peer-reviewed laboratory data confirms a ~20% increase in median survival alongside reduced aortic PWV in Serpine1 heterozygous null mice (Khoddam et al., JCI 2025). Level D(Translational Gap) Strong Support(Pre-clinical)
10. DNAm PAI-1 is the primary driver and predictor within the GrimAge clock 2019 Steve Horvath GrimAge publication in Aging. Large-scale validation across thousands of human subjects confirms DNAm PAI-1 is among the most robust single surrogate markers for all-cause mortality and cardiometabolic disease (Lu et al., 2019). Level C Strong Support

IV. Actionable Protocol (Prioritized)

` PAI-1 THERAPEUTIC / LIFESTYLE WINDOW
(Target: ~50% Normal)

PATHOLOGICAL EXCESS OPTIMAL ZONE TOTAL ABLATION
(Sedentary, Obese, High-PAI-1) (Geroprotection) (Null State / Toxic OD)
--------------------------------- [--------------------] ---------------------------------

  • Arterial Stiffness (PWV high) - Preserved Compliance - Severe Spontaneous Bleeding
  • Accelerated Cellular Senescence - Enhanced Insulin Sens- - Progressive Cardiac Fibrosis
  • Thrombosis & PD-L1 Evasion - Lower PCSK9 & HbA1c - Defective Tissue Repair`

High Confidence Tier (Level A/B Evidence)

No direct Level A/B clinical trial currently approves pharmacological PAI-1 inhibitors specifically for human lifespan extension.
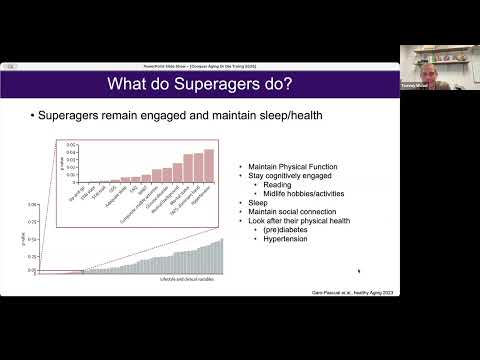
  • Metabolic PAI-1 Suppression via Glycemic Optimization: Implement clinical exercise protocols (aerobic zone 2 + resistance training) and dietary strategies aimed at visceral fat reduction. Elevated adipose tissue mass is the primary driver of pathological PAI-1 secretion; metabolic normalization directly decreases plasma PAI-1 antigen levels.
  • Vascular Compliance Monitoring: Measure central arterial stiffness via carotid-femoral Pulse Wave Velocity (cfPWV) or high-resolution pulse contour analysis as a validated surrogate clinical endpoint for cardiovascular biological aging.

Experimental Tier (Level C/D Evidence with High Safety Margins)

  • Targeted Pharmacological PAI-1 Inhibitors: Small molecule allosteric PAI-1 inhibitors (e.g., TM5614 / RS5614 under investigation at Tohoku University) have demonstrated phase 2 safety in limited oncology and respiratory trials. Off-label or unmonitored human use for geroprotection is premature pending dedicated longevity and cardiovascular clinical trials.
  • Epigenetic Biomarker Tracking: Quantify biological age acceleration and mortality risk using second- and third-generation DNA methylation assays that incorporate surrogate plasma protein estimates (e.g., DNAm GrimAge / DNAm PAI-1).
  • Nutraceutical Modulation: Polyphenolic compounds with weak in vitro PAI-1 suppressive activity (e.g., EGCG, curcumin, resveratrol) show low safety risks but maintain questionable in vivo pharmacokinetic potency and unproven human translational efficacy.

Red Flag Zone (Debunked Claims / Absent Safety Data)

  • Unmonitored Complete PAI-1 Knockdown: High-dose, non-titrated pharmacological antagonism or permanent gene knockout represents a severe safety hazard. Complete lack of PAI-1 (PAI-1 = 0) precipitates life-threatening hemorrhagic risks, microvascular instability, and spontaneous myocardial/pericardial fibrosis.
  • Direct Telomere Re-extension Claims: While PAI-1 haploinsufficiency correlates with longer leukocyte telomeres, taking PAI-1 suppressors does not acutely reverse established critical telomere erosion in existing somatic tissues.
1 Like

Superagers (Featuring Tommy Wood, MD, PhD)

I. Executive Summary

This presentation analyzes the “Superager” phenotype—individuals aged 80 years and older who maintain episodic memory and executive function benchmarked to cohorts 20 to 30 years younger. Dr. Tommy Wood argues that late-life cognitive decline is neither an unavoidable biological destiny nor an immutable genetic mandate. Historically, data from the Seattle Longitudinal Study demonstrated that a substantial fraction of individuals maintained midlife cognitive abilities past age 70, whereas contemporary normative distributions increasingly view intact octogenarian cognition as anomalous. Wood argues this reflects shifting baseline metabolic, cardiovascular, and environmental health across cohorts rather than fixed biological aging.

Neuroanatomically, Wood highlights findings from the Northwestern SuperAging Program and the Spanish Vallecas Project, emphasizing that Superagers exhibit attenuated whole-cortex and gray matter volume loss—approximately 1.06% annually compared to 2.24% in typical aging controls. Morphometric preservation is pronounced within the anterior cingulate cortex, entorhinal cortex, and subcortical relays (hippocampus and thalamus), underpinned histologically by preserved von Economo neuron densities.

Addressing etiology, Wood discounts pure genetic fatalism, pointing to prospective observational phenotyping showing comparable APOE ε4 allele carrier frequencies between Superagers and normal decliners. Instead, multivariate models identify physical functionality (timed motor agility), midlife intellectual/hobby engagement, sustained sleep architecture, social network density, and the stringent absence of cardiometabolic pathologies (e.g., pre-diabetes, insulin resistance, hypertension) as the primary drivers preserving cognitive reserve.

While Wood presents a clinically sound, multi-domain paradigm congruent with mainstream neuroepidemiology, his interpretation carries translational caveats. Emphasizing modifiable lifestyle factors risks conflating reverse causality with primary prevention: individuals exhibiting slower baseline neurodegeneration are inherently more capable of sustaining high physical and intellectual activities into late life. Furthermore, translating these observational associations into high-efficacy post-symptomatic interventions remains unproven in prospective Phase III clinical trials.

II. Insight Bullets

  • Operational Definition: Superagers are defined as octogenarians (aged 80+) who preserve episodic memory scores equal to or exceeding norms established for individuals aged 50 to 60.
  • Historical Prevalence Baselines: Historical cohorts, such as the Seattle Longitudinal Study, showed that over 50% of participants retained stable cognitive scores into late life without marked impairment.
  • Normalization of Pathology: Contemporary society frequently conflates universal age-related pathology with normative biological aging.
  • Decoupled Atrophy Rates: Superagers exhibit annualized whole-cortex and gray matter volume reductions of approximately 1.06%, compared to roughly 2.24% per year observed in typical aging controls.
  • Research Cohorts: Longitudinal Superager phenotyping is primarily spearheaded by groups at Northwestern University and the Vallecas Project via the Queen Sofia Foundation Alzheimer Center in Madrid.
  • White Matter Integrity: Attenuated neurodegeneration in Superagers is observable across cortical gray matter and central white matter tract connectivity.
  • Multi-Domain Correlates: Multifactorial regression models demonstrate that superaging tracks with physical capacity, intellectual engagement, restorative sleep, social interaction, and metabolic stability.
  • Cardiometabolic Sparing: Superagers consistently avoid subclinical cardiometabolic disease, presenting lower rates of pre-diabetes, insulin resistance, and systemic hypertension.
  • Independence from APOE ε4: Data from the Vallecas Project indicate that APOE ε4 carrier frequency does not definitively separate Superagers from age-matched controls, highlighting functional resilience mechanisms.
  • Biomarker Decoupling: Peripheral and cerebrospinal biomarkers of neurodegeneration (e.g., total tau, neurofilament light chain) are substantially lower in Superagers.
  • Anterior Cingulate Preservation: Neuropathological and MRI imaging studies confirm preferential preservation of anterior cingulate cortical thickness in Superagers.
  • Von Economo Neuron Sparing: Post-mortem histological examinations show that Superagers retain a four- to five-fold higher density of spindle-shaped von Economo neurons in anterior cingulate regions compared to typical elderly controls.
  • Motor Function Biomarkers: Superagers demonstrate superior motor agility, gait stability, and grip strength, which correlate inversely with neurodegenerative progression.
  • Cognitive Stimulation Demand: Dr. Wood emphasizes that the requirement for dedicated cognitive and sensory input escalates in post-retirement life as occupational stimulation ceases.
  • Cross-Domain Synergism: Improvements in one lifestyle domain (e.g., restorative sleep or regular exercise) generate downstream systemic benefits across vascular and metabolic pathways.
  • Cognitive Reserve vs. Brain Reserve: Superagers appear to benefit simultaneously from brain reserve (structural macro-morphology) and cognitive reserve (synaptic plasticity and functional compensation).
  • Midlife Hobbies as Mediators: Lifelong engagement in varied cognitive pursuits (e.g., reading, complex hobbies, musical instrumentation) is statistically overrepresented in Superager registries.
  • Social Connectivity Value: Deep social networks correlate with increased anterior cingulate preservation and reduced chronic inflammatory signaling.
  • Glycemic Control Thresholds: Maintaining tight normoglycemia avoids microvascular basement membrane thickening and advanced glycation end-product accumulation in the cerebral microvasculature.
  • Incremental Behavioral Modification: Wood recommends focusing on incremental, compounding modifications rather than radical, unsustainable protocols.

III. Adversarial Claims & Evidence Table

Claim from Video Speaker’s Evidence Scientific Reality (Current Data) Evidence Grade Verdict
Superagers lose brain volume at half the rate of typical older adults (~1% vs. ~2% annually). Morphometric volumetric MRI data cited from Northwestern and Spanish cohorts. Confirmed. Longitudinal structural MRI data (Garo-Pascual et al., 2023; Harrison et al., 2018) show whole-brain annualized atrophy of ~1.06% in Superagers versus ~2.24% in typical peers. Level C Strong Support
Historical cohorts (Seattle Longitudinal Study) had >50% retention of midlife cognition into late life. Seattle Longitudinal Study epidemiological trajectories. Substantially accurate. The Seattle Longitudinal Study (Schaie, 2005) documented that over 50% to 60% of individuals maintained reliable performance across multiple cognitive domains until age 74–81, with catastrophic declines clustering in the terminal ~5–7 years. Level C Strong Support
Sparing of pre-diabetes and hypertension drives preservation of cognition in Superagers. Multivariate risk-factor analysis from European Superaging cohorts. Robustly validated. Midlife/late-life hypertension and insulin resistance drive cerebral small vessel disease, leukoaraiosis, and amyloid/tau deposition (Biessels et al., 2023; SPRINT MIND, 2019). Level A/B Strong Support
Superagers resist cognitive decline independent of traditional genetic risk factors (e.g., APOE ε4). Observational biomarker and genotyping data from the Madrid Vallecas cohort. Partially validated. Garo-Pascual et al. (Lancet Healthy Longev, 2023) identified no statistically significant differences in APOE ε4 carriage between Superagers and controls in their sample, though meta-analyses demonstrate APOE ε4 status unequivocally accelerates cumulative lifelong risk (Ward et al., 2021). Level C Plausible
Engaging in cognitively demanding midlife hobbies directly prevents structural cortical atrophy. Correlational associations between hobby participation metrics and brain volume. High risk of reverse causality. Observational studies confirm associations between cognitive leisure activities and reduced dementia incidence (Lee et al., 2023), but interventional RCTs (e.g., FINGER trial, 2015) show only modest cognitive stabilization without significant reversal of underlying brain parenchymal loss. Level B/C Plausible

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Evidence)

  • Vascular & Glycemic Risk Elimination:
    • Blood Pressure Optimization: Target systolic blood pressure under 120 mmHg via physical exercise, dietary sodium moderation, and pharmacotherapy (e.g., ACEi, ARBs) if indicated (SPRINT MIND Investigators, 2019).
    • Glycemic Control: Maintain HbA1c < 5.6% and fasting plasma glucose < 100 mg/dL to prevent microvascular cerebral hypoperfusion, glycation-mediated endothelial damage, and blood-brain barrier dysfunction.
  • Aerobic & Resistance Training (Motor Sparing):
    • Preserve motor agility, neuromuscular velocity, and cardiorespiratory fitness (VO2​ max) with at least 150 minutes of moderate-to-vigorous aerobic training plus 2 to 3 resistance-training sessions per week. Preserving motor unit firing frequency directly correlates with hippocampal and anterior cingulate structural preservation.

Experimental Tier (Level C/D Evidence with High Safety Margin)

  • Cognitive Novelty Architecture:
    • Engage in novel, cognitively demanding tasks (e.g., secondary language acquisition, complex instrumental performance, analytical reasoning) rather than passive, repetitive tasks (e.g., commercial “brain training” games). Promotes dendritic spine density and functional frontoparietal connectivity.
  • Sleep Stage Architecture Preservation:
    • Prioritize 7 to 8 hours of sleep per night to support glymphatic clearance of neurotoxic proteins (tau, amyloid-beta). Screen for and treat sleep-disordered breathing (obstructive sleep apnea) to prevent episodic nocturnal hypoxia.
  • Social Network Engagement:
    • Maintain structured, recurring social contact. Observational evidence links high social engagement to larger von Economo neuron-rich regions (anterior cingulate cortex).

Red Flag Zone (Claims Lacking Safety Data or Debunked)

  • Superager Biological Determinism Bypass:
    • Safety Data Absent / Unsupported: Consuming proprietary “nootropic” stacks, untested longevity supplements, or unverified peptide regimens under the assumption that they replicate the Superager molecular phenotype without addressing metabolic, cardiovascular, or physical foundation metrics.

The Ability To Perform Regenerative Medicine Will Also Allow Us To Alter Ourselves However We Want

Primary Expert Featured: Michael Levin, PhD (Distinguished Professor, Vannevar Bush Chair, Director of the Allen Discovery Center at Tufts University; Associate Faculty at the Wyss Institute at Harvard University)

I. Executive Summary

In this presentation, Dr. Michael Levin outlines a conceptual model linking developmental bioelectricity, top-down anatomical goal-states, and morphological plasticity. Levin posits that definitive regenerative medicine cannot be achieved through bottom-up genomic micromanagement or individual stem cell placement. Instead, he frames morphogenesis as a communication problem governed by a “morphogenetic code”—an informational layer mediated by transmembrane potential (Vmem​) gradients and gap junctional intercellular communication (GJIC) networks that dictate collective anatomical endpoints.

Levin argues that deciphering and rewriting these bioelectric goal-states inevitably unlocks “freedom of embodiment.” Because cellular collectives utilize generalizable pattern-homeostasis subroutines to build and repair tissues, providing them with novel geometric targets would theoretically permit intentional, arbitrary biological remodeling. This encompasses engineered synthetic living machines (biobots/xenobots), customized organ geometry, and structural alterations that bypass evolutionary anatomical constraints (such as spinal degenerative disease, sensory limits, and pathogen susceptibility).

Addressing organismal senescence, Levin presents a theoretical framework: aging may represent a “boredom problem” or an informational breakdown within a second-order, metacognitive homeostatic loop that tires of maintaining a fixed somatic set-point. Drawing on asexual planarian models (which exhibit apparent somatic immortality through continuous fission and whole-body regeneration) and holometabolous insect metamorphosis (caterpillar-to-butterfly transitions), Levin hypothesizes that long-term biological maintenance may necessitate periodic phenotypic metamorphosis or recurring regenerative resets.

From an academic perspective, while Levin’s underlying laboratory research demonstrating bioelectric patterning in flatworms (Dugesia japonica) and amphibians (Xenopus laevis) is peer-reviewed and technically sound, his extension of these principles to whole-body human anatomical plasticity, modular body swapping, and metabolic “boredom” is entirely speculative. Current clinical translation remains constrained to early-phase localized tissue regeneration. There is no clinical or mammalian trial evidence demonstrating that altering bioelectric circuits can rewrite macroscopic human body morphology, rejuvenate complex organ systems, or sustain indefinitely pliable multicellular identities.

II. Insight Bullets

  • Regenerative Medicine as Communication: Dr. Levin argues that definitive tissue regeneration requires communicating high-level target morphology to cell collectives rather than micromanaging individual molecular cascades.
  • The Morphogenetic Code: Biological pattern formation is governed by bioelectric software—transmembrane potential gradients and voltage distributions that instruct cells on macroscopic anatomical goals.
  • Freedom of Embodiment: The technical ability to direct cell collectives to regenerate wild-type organs inherently unlocks the ability to specify arbitrary, novel anatomical structures.
  • Synthetic Living Constructs: Levin highlights that identical genomes can yield novel multicellular life forms, such as biological robots (“biobots” or “xenobots”), when cellular communication networks are computationally reconfigured. Research updates and project frameworks are documented via the Tufts Center for Regenerative and Developmental Biology.
  • Decoupling from Evolutionary Mutation: Levin rejects the fatalistic assumption that humans must remain confined to physiological and anatomical constraints established by stochastic evolutionary history and cosmic ray mutations.
  • Arbitrary Biological Geometry: Controlling pattern homeostasis theoretically permits engineering non-canonical human organs, synthetic functional living machines, and cultured tissues.
  • Evolutionary Pathologies: Evolutionary compromises—such as lumbar spine degradation, refractive visual errors (astigmatism), and innate pathogen vulnerability—are viewed by Levin as addressable design flaws rather than fixed biological realities.
  • The “Boredom Problem” in Aging: Levin presents a theoretical hypothesis that biological senescence reflects an informational exhaustion or breakdown in the regulatory loops tasked with maintaining a static somatic set-point over decades.
  • Metamorphic Life Extension: Levin speculates that multi-century or indefinite lifespan might require radical phenotype transitions—resembling larval-to-adult metamorphosis in insects—rather than maintaining a static anatomical architecture.
  • Planarian Somatosensory Immortality: Asexual lines of planarian flatworms achieve biological immortality through continuous bisection and blastema-mediated whole-body regeneration, sidestepping somatic senescence.
  • Regenerative Cascade Refreshes: Induction of coordinated regenerative cascades could theoretically “refresh” degraded tissue networks without requiring radical anatomical shifts.
  • Non-Genomic Information Storage: Pattern-homeostatic memories are stored bioelectrically across cellular networks and can be altered without introducing genetic edits or DNA mutations.
  • Loss of Morphostatic Information: Formalized in recent academic literature (Pio-Lopez & Levin, 2024), aging is conceptualized as a progressive decay of bioelectrically encoded morphostatic coordinate maps.
  • Basal Cellular Cognition: Cells operate with basal goal-directed competencies, navigating physiological, transcriptional, and anatomical morphospaces to reach designated target shapes.
  • Top-Down vs. Bottom-Up Bioengineering: Attempting to build organs strictly via gene editing and 3D bioprinting is compared to manipulating computer hardware with a soldering iron instead of executing high-level software commands.
  • Metacognitive Regulatory Loops: Higher-order bioelectric integration networks act as systemic homeostatic regulators that coordinate local cellular repair behavior.
  • Somatic Plasticity Limits: In higher mammals, regenerative competence is tightly restricted by epigenetic silencing, immune-mediated fibrotic scarring, and oncogenic suppression checkpoints.
  • Ion Channel Pharmacology (“Morphoceuticals”): Reprogramming anatomical set-points is achieved experimentally through targeted ionophores, channel openers/blockers, and gap junction modulators (Pio-Lopez & Levin, 2023).
  • Philosophical Status of Wild-Type Morphology: The “standard” human physical form is categorized as one transient evolutionary solution out of a vast multidimensional morphospace.
  • Translational Horizon: Translating non-mammalian bioelectric pattern reprogramming into clinical protocols for human limb or organ replacement remains an unvalidated, long-term scientific pursuit.

III. Adversarial Claims & Evidence Table

Claim from Video Speaker’s Evidence Scientific Reality (Current Data) Evidence Grade Verdict
Cracking the morphogenetic code allows arbitrary rewriting of human anatomy (“Freedom of Embodiment”). Bioelectric pattern induction in Xenopus(ectopic eyes) and planaria (two-headed phenotypes) via ion channel manipulation. Confirmed in non-mammalian model systems (Levin, 2021). However, mammalian adult cells exhibit rigid epigenetic locks, dense extracellular matrix barriers, and immediate fibroproliferative scarring responses that prevent large-scale geometric re-specification. Mammalian human trials: None. Level D(Translational Gap) Speculative
Aging is driven by a loss of morphostatic information / cellular “boredom” with maintaining a static set-point. Theoretical biophysical frameworks and computational simulations of neural cellular automata. Published as a hypothesis (Pio-Lopez & Levin, 2024). While bioelectric membrane depolarization correlates with senescence and loss of gap junctional communication, mainstream biogerontology demonstrates aging is heavily driven by accumulated molecular entropy: somatic mutations, telomere exhaustion, epigenetic drift, mitochondrial free radical production, and proteostatic collapse (López-Otín et al., 2023). Level E Unsupported
Inducing periodic whole-body regeneration cascades (planarian-style) can eliminate organismal senescence in humans. Asexual planaria (Schmidtea mediterranea) exhibit negligible senescence under continuous fission and neoblast proliferation. Planaria possess high densities of pluripotent somatic stem cells (neoblasts) comprising ~20% of their somatic cells, supported by continuous telomere lengthening (Aboobaker, 2011). Adult humans lack systemic pluripotent stem cell pools; unrestricted regenerative signaling in adult mammals strongly elevates risk of teratoma formation, oncogenesis, and hyperproliferative malformations. Level D(Translational Gap) Safety Warning
Cells can be directed to repair complex anatomical structures without direct genome editing. Amphibian limb regeneration induced via multi-drug bioreactor treatments modulating bioelectric and hormonal cues. Validated in Xenopus laevis froglet hindlimbs using wearable bioreactors delivering ionophores and progesterone (Murugan et al., 2022). However, achieving patterned multi-tissue osteochondral, vascular, and neuro-muscular regeneration in human patients remains unproven in clinical trials. Level D(Translational Gap) Plausible
Humans will require radical phenotype/morphological metamorphosis (analogous to insects) to achieve multi-century lifespans. Metamorphic life cycle analogies (holometabolous insect development; speculative science fiction literature). Pure philosophical conjecture. Insect metamorphosis (e.g., Lepidoptera) involves systemic histolysis via juvenile hormone and 20-hydroxyecdysone cascades, completely dissolving larval somatic architectures into imaginal disc progenitor pools. There is no physiological, phylogenetic, or evolutionary precedent for this in mammalian biology. Level E Unsupported