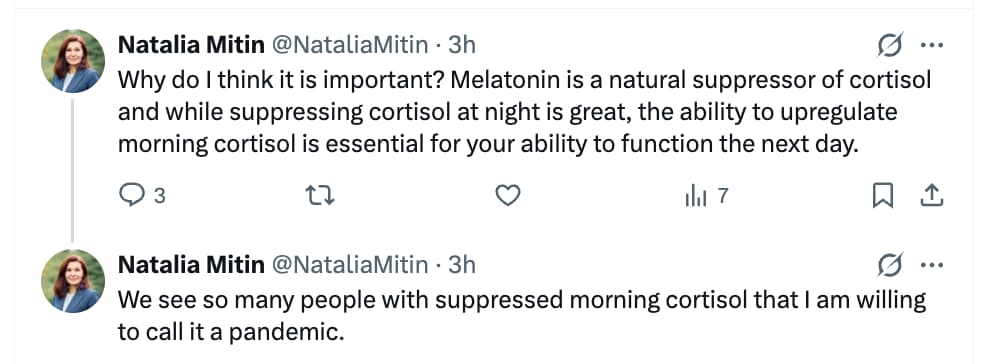
Melatonin megadoses?

I currently use topical Minoxidil to which I add Rapamycin and stevia. Seems like adding Melatonin might prove an interesting addition by possibly addressing an otherwise unaddressed factor.

I asked ChatGPT

Given your particular situation, I think topical melatonin deserves consideration—not because the evidence equals that for minoxidil or finasteride, but because:

  1. it appears to act through mechanisms that only partially overlap with your current regimen,
  2. it has an unusually favorable safety profile,
  3. you have already demonstrated a better-than-average response to an experimental combination (minoxidil + rapamycin).

That does not mean it will necessarily add benefit, but biologically it makes more sense than many of the compounds commonly added to topical hair formulas.

Current regimen

Your present topical approach already appears to target several major aspects of androgenetic alopecia.

Agent Likely primary action
Minoxidil Potassium-channel opening, VEGF, prolongation of anagen
Rapamycin mTOR modulation, stem-cell homeostasis, reduced senescence/inflammation (experimental)
Stevia Highly speculative; possible anti-inflammatory and microbiome effects

Melatonin would add something different.


What topical melatonin actually does

Hair follicles are unusual.

They do not merely respond to circulating melatonin.

They synthesize melatonin locally, express melatonin receptors, and possess an intrinsic melatonin antioxidant system. Hair follicles therefore appear to use melatonin as a local signaling molecule rather than simply responding to pineal secretion.

Current evidence suggests several mechanisms.

1. Antioxidant protection

Probably the strongest mechanism.

Hair follicles generate large amounts of reactive oxygen species because matrix keratinocytes divide extraordinarily rapidly.

Melatonin

  • scavenges free radicals
  • activates endogenous antioxidant enzymes
  • protects mitochondrial DNA
  • reduces lipid peroxidation

These actions could preserve follicular function under chronic oxidative stress.


2. Mitochondrial support

This interests me even more.

Melatonin accumulates inside mitochondria.

It appears to

  • stabilize mitochondrial membranes
  • improve ATP production
  • reduce mitochondrial oxidative injury
  • support mitophagy under stress

Since hair follicles rank among the body’s most metabolically active tissues, this represents a plausible biological target.


3. Prolongation of anagen

Multiple studies suggest that melatonin shifts follicles toward the growth phase.

Rather than dramatically increasing growth rate, it appears to reduce premature transition into catagen.


4. Anti-inflammatory effects

AGA increasingly appears to involve chronic perifollicular inflammation.

Melatonin decreases several inflammatory cytokines and oxidative mediators.

This may complement rapamycin rather than duplicate it.


Human clinical evidence

The evidence remains modest but better than many realize.

Randomized placebo-controlled trial

The best study remains the 2004 Fischer trial.

  • 40 women
  • placebo-controlled
  • double blind
  • 0.1% topical melatonin
  • once daily
  • six months

Result:

Statistically significant improvement in anagen hair proportion in several measured scalp regions compared with placebo.


Open-label studies

Several subsequent studies involving both men and women reported

  • increased hair density
  • increased hair counts
  • reduced shedding
  • improved hair thickness

These studies lack placebo controls, so they provide supportive—but weaker—evidence.


Recent review

A 2023 review identified 11 human studies (over 2,200 participants collectively).

Overall conclusion:

  • most studies reported improved hair growth
  • several reported improved density
  • some reported thicker shafts

The authors concluded that topical melatonin appears promising, but larger randomized trials remain necessary.

That seems like a fair assessment.


Would it complement your regimen?

I think yes.

Mechanistically, your regimen looks like this:

Minoxidil
        ↓
vascular signaling
potassium channels
VEGF

Rapamycin
        ↓
mTOR
cellular aging
autophagy

Melatonin
        ↓
mitochondria
oxidative stress
circadian follicle biology

Those represent largely independent pathways.

That raises the possibility—not proof—of additive effects.


Interaction with rapamycin

This interests me the most.

Both agents influence

  • autophagy
  • mitochondrial quality
  • oxidative stress

However, they act differently.

Rapamycin primarily alters nutrient-sensing pathways.

Melatonin primarily protects mitochondria from oxidative injury.

Those mechanisms appear complementary rather than redundant.

There is currently no evidence that topical melatonin interferes with topical rapamycin.


Could melatonin interfere with minoxidil?

Nothing currently suggests this.

If anything, improved follicular mitochondrial function could theoretically support the proliferative response induced by minoxidil.

Again, this remains theoretical.


Vehicle considerations

This may matter more than the melatonin itself.

Most positive studies used

  • ethanol
  • propylene glycol
  • hydroalcoholic vehicles

Those vehicles closely resemble many commercial minoxidil formulations.

Therefore, if adding melatonin directly into your topical minoxidil solution, compatibility seems chemically plausible, although I have not seen published stability testing for that exact combination.

I would avoid assuming long-term stability without data.


Dosing

Human evidence clusters around two concentrations: 0.1%
Most studied.

or: 0.0033%
Some supportive studies.

The higher concentration has the stronger evidence base.


Safety

Topical melatonin appears remarkably well tolerated.

Reported adverse effects have generally been limited to

  • mild scalp irritation
  • occasional transient itching

Importantly,

systemic melatonin concentrations remained within normal nighttime physiological ranges in the randomized trial despite daily application.


My assessment for your specific case

Given what I know about your situation:

  • age 74
  • ongoing oral finasteride
  • oral minoxidil
  • topical minoxidil
  • topical rapamycin
  • documented improvement with the current regimen
  • willingness to use evidence-informed experimental approaches

I would rate topical melatonin as:

Biological plausibility: ★★★★★

Human evidence: ★★★☆☆

Safety: ★★★★★

Probability of a meaningful additional benefit: ★★☆☆☆ to ★★★☆☆

In other words, I would not expect melatonin to produce another dramatic improvement comparable to initiating minoxidil, but I do think it has a reasonable chance of incrementally increasing hair density or prolonging anagen through mechanisms not fully addressed by your current regimen.

One additional thought

Your current topical formulation already contains an unusual combination of active agents. Before simply adding melatonin into the same bottle, I would first want to evaluate the chemical stability and compatibility of melatonin with:

  • minoxidil,
  • rapamycin,
  • the solvent system,
  • and stevia extract.

That question has a different answer than whether melatonin itself works. If the mixture degrades one of the actives or reduces penetration, it could negate any potential benefit. Assessing formulation compatibility would be the logical next step before modifying a regimen that is already producing meaningful results.


1 Like


Source: This post on X

Related Paper Cited:

Study Overview & Metabolic Implications

The file HT4WU4MWEAAkqXz.jpeg highlights a randomized, double-blind, crossover trial involving 21 healthy adults[cite: 1]. The study investigated how a 5 mg dose of supplemental melatonin impacts glucose metabolism, explicitly segmenting subjects by their MTNR1B genotype[cite: 1].

Key findings for MTNR1B risk-allele carriers compared to non-carriers include:

  • An 11.7% increase in overall glucose exposure
  • A 19.2% reduction in early C-peptide response
  • A 40% blunting of first-phase beta-cell responsivity
  • A 64.3% slower insulin feedback inhibition

These major metabolic effects were isolated to risk-allele carriers and were not observed in non-carriers.

Complete Paper Summary:

Melatonin Blunts the Insulin Response in People With a Common Diabetes-Risk Gene Variant

In a tightly controlled crossover trial at Brigham and Women’s Hospital, 21 healthy adults received 5 mg of melatonin or placebo in the afternoon, followed an hour later by an intravenous glucose tolerance test. In the 10 participants carrying the common MTNR1B risk variant (rs10830963 G), melatonin raised the glucose response by about 12 percent and cut the first-phase insulin response of the pancreas by about 40 percent. It also slowed the normal shut-off of insulin secretion after an insulin injection. The 11 noncarriers showed no significant change. The trial’s prespecified primary outcome, the disposition index, was not affected, and the study tested one daytime dose in young, lean, healthy people of European ancestry.

Melatonin is one of the most widely used supplements, taken mostly for sleep. A small but carefully run trial suggests that for roughly half the population, it may come with a metabolic cost when it overlaps with a glucose load.

The reason lies in a gene called MTNR1B, which encodes one of the two melatonin receptors. A common variant of this gene is among the strongest known genetic signals for raised fasting glucose and type 2 diabetes. By the paper’s figures, about 48 percent of Europeans, 70 percent of East Asians and 13 percent of African Americans carry at least one copy. The variant is thought to make insulin-producing beta cells more responsive to melatonin, and melatonin tells those cells to hold back.

To test what that means in practice, researchers kept 21 healthy volunteers in a laboratory for five days with fixed sleep, light and meals. On two separate days, each person swallowed either 5 mg of melatonin or a placebo in the afternoon, in random order, with neither side knowing which. An hour later they received glucose directly into a vein, followed 20 minutes later by a small injection of insulin, with blood drawn more than 30 times over three hours.

Across the whole group, melatonin did not significantly change the glucose response. The picture changed when the group was split by genotype. In the 10 carriers, the glucose response rose by about 12 percent. A mathematical model of the blood data pointed to the cause: the rapid first burst of insulin release that normally follows a glucose rise was about 40 percent weaker. Every one of the 10 carriers showed a drop, ranging from 8 to 66 percent. Noncarriers showed no reliable change.

A second effect appeared after the insulin injection. Normally, rising insulin in the blood tells the pancreas to ease off. In carriers on melatonin, that shut-off took about 64 percent longer. The authors read this as a failure of insulin’s own feedback brake.

There was one unexpected finding. After the insulin injection, seven of the 10 carriers dipped below 70 mg/dL on placebo, but none did on melatonin. The authors suggest this might one day be useful for people on insulin therapy, though that is speculation.

The authors propose a practical precaution: keep melatonin and main meals at least two hours apart. That advice goes beyond what was tested. The study used a single daytime dose that pushed blood melatonin far above natural levels, with glucose delivered by vein instead of food. When the same participants later ate dinner and breakfast, the genotype difference did not show up. And the measure the trial was designed around, a combined index of insulin secretion and sensitivity, did not move.

The result fits a consistent line of work from this group, but it shows a short-term physiological shift in healthy people, not a path to diabetes.

Actionable Insights

This trial measured a single dose in 21 healthy people. It does not show that melatonin causes diabetes, and it did not test any of the timing strategies below.

  • Who is affected. Only carriers of the MTNR1B risk variant showed an effect. About half of people of European descent carry it, and more in East Asian populations. Most people do not know their status, though rs10830963 is reported in many consumer genetic tests.
  • Size of the effect in carriers. The glucose response after an intravenous sugar load was about 12 percent higher. The fast first burst of insulin release was about 40 percent lower. Late glucose ran about 11 mg/dL higher. These are modest shifts in healthy people, with no symptoms.
  • Size of the effect in noncarriers. None detected, though the study was too small to rule out a small one.
  • The authors’ suggestion. Avoid taking melatonin within two hours of a main meal, or avoid eating for several hours afterward. This is reasonable and low cost, but untested here. Typical bedtime use several hours after dinner already fits it.
  • Dose. Only 5 mg was tested, which the paper notes can produce blood levels up to 10 times the natural night-time peak. Lower doses were not studied.
  • Hypoglycemia finding. Not a reason for anyone on insulin to start melatonin.

Context and Source

  • Full title: Melatonin Impairs Glucose Tolerance, First-Phase Insulin Secretion, and Insulin Feedback Inhibition; Interaction With MTNR1B Diabetes Risk Variant
  • Access: Published under the standard American Diabetes Association license, not an open access license. The copy provided was downloaded as a guest, so it may be free to read, which I did not verify.
  • Institution: Brigham and Women’s Hospital and Harvard Medical School (lead), with the University of Pennsylvania, University of Copenhagen, University of Murcia, Massachusetts General Hospital and the Broad Institute
  • Country: United States, with collaborators in Denmark and Spain
  • Journal: Diabetes Care, 2026, volume 49, issue 8, pages 1498 to 1506. DOI 10.2337/dc26-0164
  • Trial registration: NCT02642640
  • Funding and conflicts: NIDDK grant R01 DK102696 and a Harvard CTSA award. The senior author reports consultancies stated to be unrelated and managed by his institution. No other conflicts declared.

Impact evaluation: The impact score of this journal is 22.6 (Journal Impact Factor, 2025 citation data, as reported by one third-party tracker), evaluated against a typical high-end range of 0 to 60+ for top general science, therefore this is a High impact journal.

3 Likes

Another reason to have your genome sequenced? Can’t hurt.

1 Like

These are acute effects measured shortly after taking melatonin when a lot of it is in the blood. If you take melatonin before bedtime (not an extended release one) then it should for the most part be long gone from the blood in the morning. I think this may be a reason to prefer plain melatonin instead of time-release capsule rather than necessarily avoiding taking melatonin.

2 Likes