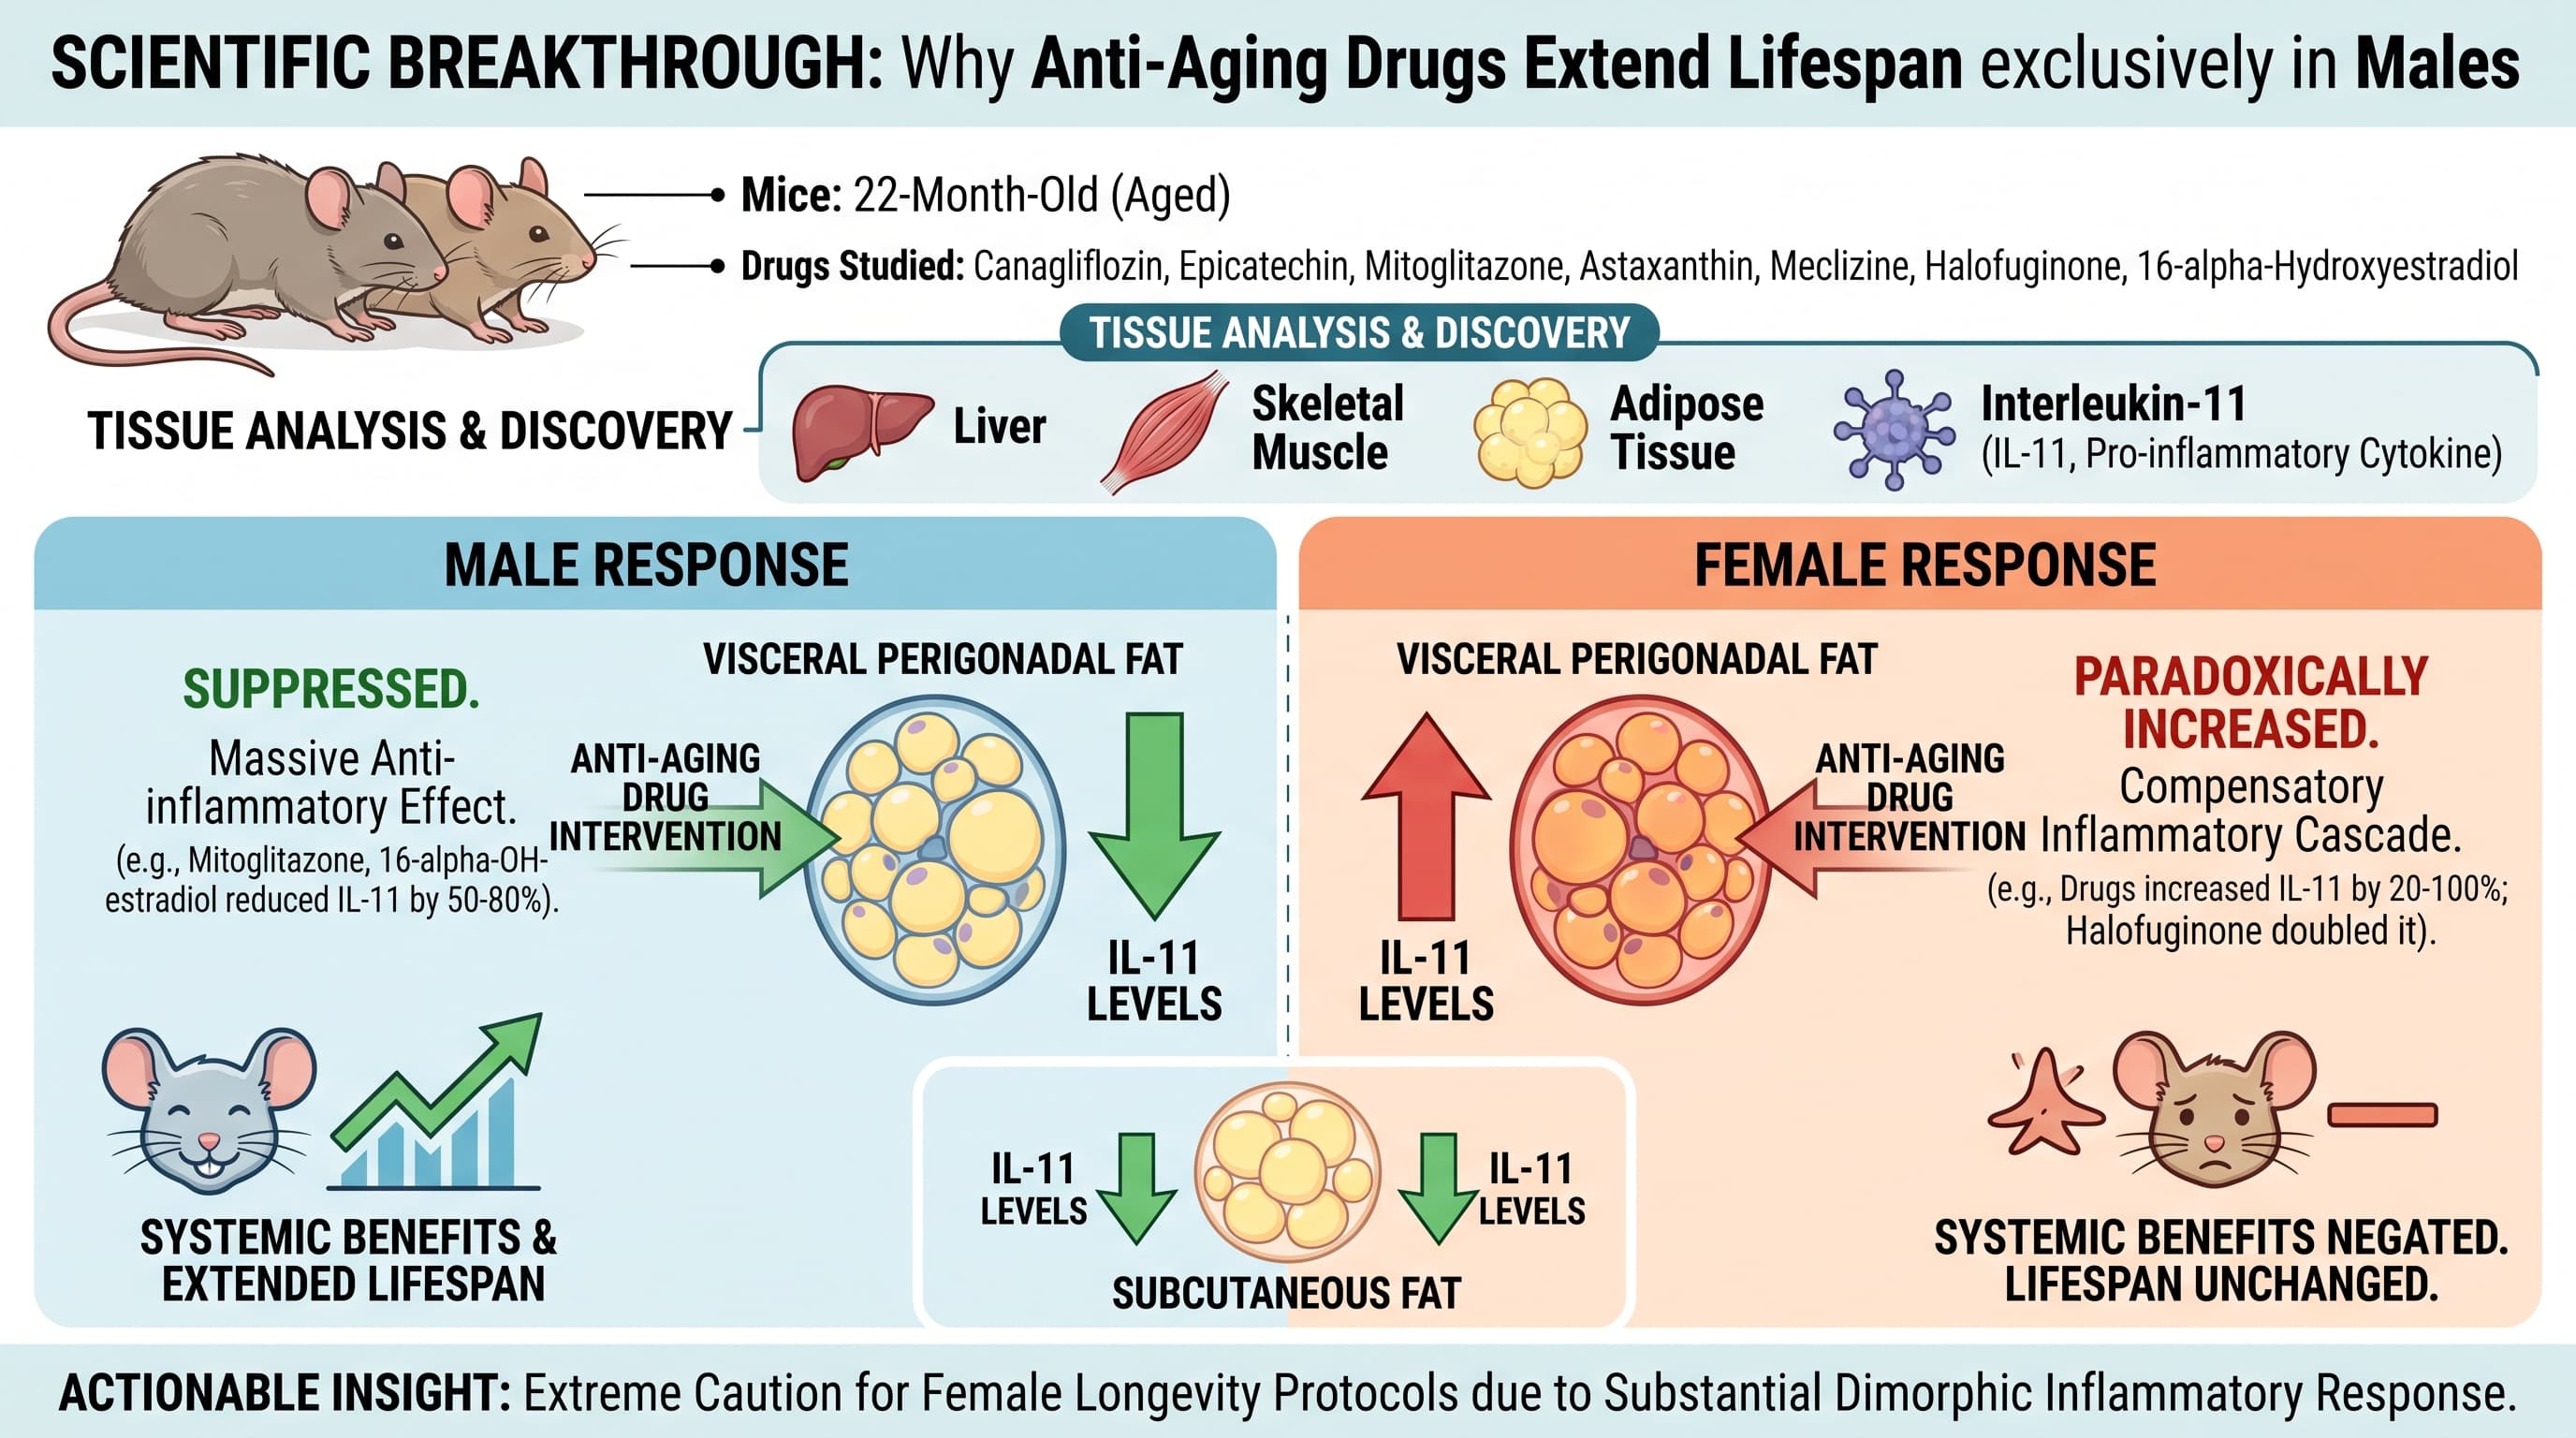
Researchers analyzed tissue from 22-month-old mice to determine why seven prominent anti-aging drugs extend lifespan exclusively in males. The study measured levels of the pro-inflammatory cytokine interleukin-11 across liver, muscle, and adipose tissues. While the drugs successfully lowered interleukin-11 in subcutaneous fat for both sexes, they triggered divergent responses in visceral fat. In males, the interventions suppressed visceral interleukin-11, but in females, five of the seven drugs paradoxically increased it. This dimorphic inflammatory response in abdominal fat suggests a compelling mechanism for the male-exclusive lifespan benefits observed in previous pharmacological trials.
The pharmacological extension of mammalian lifespan faces a persistent and poorly understood hurdle involving sexual dimorphism. The Interventions Testing Program has identified multiple compounds that extend lifespan in male mice while failing to benefit females. This phenomenon limits the clinical translation of these longevity therapeutics.
A specific protein called interleukin-11 acts as a primary driver of age-related inflammation and fibrosis. Earlier research established that blocking interleukin-11 signaling directly extends mammalian lifespan. Building on this foundation, investigators hypothesized that male-specific longevity compounds might operate by suppressing this inflammatory cytokine.
The research team tested tissue from aged mice treated with seven known male-specific longevity drugs. These drugs included canagliflozin, epicatechin, mitoglitazone, halofuginone, astaxanthin, meclizine, and 16-alpha-hydroxyestradiol. The investigators measured interleukin-11 protein levels across liver, skeletal muscle, subcutaneous fat, and visceral perigonadal fat.
The results revealed absolute tissue specificity. None of the seven drugs altered interleukin-11 expression in liver or skeletal muscle. In subcutaneous inguinal fat, the treatments universally reduced the inflammatory cytokine in both male and female subjects.
The critical discovery occurred in visceral perigonadal fat. Six of the seven drugs induced severe sex-specific divergence. Male mice experienced a significant reduction in visceral interleukin-11. Conversely, female mice experienced a paradoxical elevation of the cytokine.
Visceral adipose tissue acts as a central regulatory node for systemic metabolic health. The data indicates that while these pharmaceutical interventions successfully mitigate subcutaneous fat inflammation, they trigger a compensatory inflammatory cascade in female visceral fat. This localized tissue inflammation likely counteracts any systemic benefits the drugs might otherwise provide to females, fully negating potential lifespan extension.
Actionable Insights
Biohackers and clinicians must treat male-specific longevity compounds with caution regarding female longevity protocols. The magnitude of the dimorphic response can be substantial. In male subjects, drugs like mitoglitazone and 16-alpha-hydroxyestradiol reduced visceral interleukin-11 by 50 to 80 percent, demonstrating a massive anti-inflammatory effect size.
For female subjects, the exact same interventions increased visceral interleukin-11 by 20 to 100 percent. Halofuginone doubled the inflammatory marker in female visceral fat. This represents a significant pro-inflammatory insult.
Females utilizing compounds like astaxanthin, epicatechin, or canagliflozin for generalized anti-aging purposes may inadvertently accelerate visceral adipocyte inflammation.
Context/Source
- Open Access Paper: IL-11 inhibition by anti-aging drugs in mice: sex-specific effects for perigonadal fat depots
- Authors: Richard Miller’s Group
- Institution: University of Michigan
- Country: USA
- Journal: Immunity & Ageing
- Impact Evaluation: The impact score of this journal is approximately 8.5, evaluated against a typical high-end range of 0–60+ for top general science, therefore this is a Medium impact journal.