New hair loss drug may reverse hair loss AND hair graying without touching DHT - ABS-201

Executive Summary

ABS-201 is a new experimental hair-loss drug targeting the prolactin receptor (PRLR) rather than DHT. The strongest interpretation is not that prolactin replaces DHT as the cause of androgenetic alopecia (AGA), but that PRLR signaling may be an additional upstream or parallel pathway affecting androgen signaling, hair cycling, and the follicular stem-cell niche.

There is legitimate biology behind this. Human scalp follicles produce prolactin and express PRLR, and prolactin can inhibit hair-shaft growth and promote catagen in cultured human follicles. Separately, AGA scalp appears to retain hair-follicle stem cells while losing important progenitor populations, suggesting that advanced hair loss may partly involve failed regeneration rather than complete stem-cell loss.

The most dramatic evidence comes from anti-PRLR treatment in spontaneously balding stumptail macaques, where very large terminal-hair gains and even repigmentation were reported. However, these data mainly come from patent/company material, and macaque hair-loss models often produce much stronger responses than humans.

ABS-201 is designed to test whether sustained, very high PRLR blockade can outperform the earlier antibody HMI-115, which produced only modest human regrowth. Early Phase 1 human data show a very long half-life and encouraging short-term tolerability, but meaningful human hair-regrowth data are still pending.

Why This Is Interesting

The most important idea is not simply that prolactin affects hair growth.

The more interesting possibility is that PRLR signaling helps maintain the regenerative failure seen in miniaturized follicles.

AGA research has shown that balding scalp can retain K15-positive stem cells while losing CD34-positive progenitor cells. In other words, the stem cells may still be there, but their ability to generate the cells needed to rebuild a terminal follicle becomes impaired.

If PRLR blockade restores that process, it could potentially do something current therapies struggle to achieve: move deeply miniaturized follicles back toward full terminal growth.

That would make ABS-201 fundamentally different from simply lowering DHT or stimulating anagen.

COL17A1 May Be the Key Link

One of the most interesting mechanistic claims involves COL17A1, or collagen XVII.

COL17A1 helps maintain and anchor hair-follicle stem cells. Experimental loss of COL17A1 contributes to stem-cell depletion, follicular miniaturization, hair loss, and graying.

Absci claims that blocking PRLR increases COL17A1 and improves markers of the follicular stem-cell niche.

If confirmed, the proposed pathway could look something like:

prolactin → PRLR signaling → impaired COL17A1 / stem-cell niche → reduced progenitor output → progressive miniaturization

This is biologically plausible, but the specific PRLR-to-COL17A1 link has not yet been independently established in human AGA.

The reported macaque hair repigmentation is also interesting here because COL17A1 helps maintain the melanocyte stem-cell niche as well as the epithelial hair-follicle stem-cell niche.

Prolactin vs DHT Is Probably the Wrong Framing

Androgen signaling remains exceptionally well established in AGA.

A more realistic model is:

DHT / androgen receptor signaling + PRLR signaling + regenerative niche failure

rather than:

DHT or prolactin

Absci also reports data suggesting prolactin may increase androgen-receptor expression, which would place PRLR partly upstream of androgen sensitivity. That is intriguing, but this specific result remains company-generated and unpublished.

If ABS-201 eventually works particularly well when combined with dutasteride or finasteride, that would support the idea that the two pathways are complementary rather than competing explanations.

Why HMI-115 Was Disappointing

HMI-115 previously targeted PRLR and reportedly produced only around 14 additional non-vellus hairs/cm² in a small human cohort.

That is nowhere near the dramatic macaque response.

Absci’s explanation is that HMI-115 did not maintain sufficiently high PRLR occupancy in humans.

This matters because some receptor systems have large receptor reserves. Blocking 60, 70, or even 80% of receptors may still leave enough active receptors to preserve most downstream signaling.

ABS-201 was therefore designed for much higher and more sustained PRLR blockade.

This creates a very useful experiment:

  • If high sustained PRLR occupancy produces major human regrowth, the HMI-115 explanation gains credibility.
  • If ABS-201 achieves high occupancy but still produces weak results, the macaque model probably overpredicted human efficacy.

Important Limitations

The mechanistic data are interesting but still preliminary.

The ex vivo scalp experiments described in the video used only three male AGA scalp samples and did not include matched non-balding scalp controls.

That matters because older human follicle studies showed that prolactin can also inhibit growth in non-balding follicles.

So one unresolved question is:

Is prolactin specifically driving AGA, or is it simply a general regulator of human hair cycling?

A stronger experiment would compare frontal AGA scalp with androgen-resistant occipital scalp from the same patients while measuring PRLR signaling, COL17A1, CD34 progenitors, androgen-receptor expression, and hair growth.

Why the Monkey Results Need Caution

The stumptail macaque results are the main reason this program is exciting.

Anti-PRLR treatment reportedly produced roughly 50 to 220 additional terminal hairs/cm² in responders, and some animals continued improving after treatment stopped.

That is extraordinary.

But macaques frequently overpredict the magnitude of human hair-regrowth responses. Minoxidil and prostaglandin-related treatments have also looked much more impressive in these animals than they ultimately did in humans.

So the monkey data should be interpreted as:

strong evidence that PRLR blockade can profoundly alter primate follicular biology

rather than:

evidence that humans will regrow 100+ hairs/cm².

Why 13 Weeks May Not Tell Us Much

If ABS-201 is simply another growth stimulant, early hair-count changes should be visible quickly.

If it genuinely repairs the stem-cell niche, restores progenitor output, and gradually reverses miniaturization, the effect may take multiple hair cycles to emerge.

The most useful timeline may therefore be:

13 weeks: safety and directional signal
26 weeks: meaningful initial efficacy
9 to 12 months: possible regenerative trajectory
after treatment stops: durability

Continued improvement after treatment withdrawal would be particularly important because it would be difficult to explain through simple anagen stimulation alone.

Safety

ABS-201 blocks PRLR throughout the body, not just in scalp follicles.

Prolactin signaling is involved in reproduction, lactation, metabolism, immune function, and other physiology. Long-term systemic PRLR blockade therefore needs much more safety data.

Early Phase 1 results are encouraging: 32 participants received single IV doses up to 1,800 mg, with no serious adverse events reported at the cutoff.

However, that does not establish the safety of sustained PRLR blockade for years.

ABS-201 also has an estimated half-life of at least 65 days, which is useful for maintaining target engagement but also means adverse effects could persist long after dosing.

It is also important not to confuse PRLR blockade with simply lowering serum prolactin. Using cabergoline or similar drugs to suppress prolactin is not a DIY substitute for ABS-201.

What Would Convince Me

The decisive evidence will be human data showing:

  • substantial terminal-hair count increases
  • increased hair diameter
  • recovery in heavily miniaturized areas
  • benefit beyond strong androgen suppression alone
  • restoration of COL17A1 or progenitor-cell markers
  • persistent improvement after treatment stops
  • acceptable reproductive, metabolic, and sexual safety

If ABS-201 produces substantial regrowth in people already using finasteride or dutasteride, that would be strong evidence that AGA contains an important therapeutic bottleneck beyond DHT alone.

If it also restores COL17A1, CD34-positive progenitors, and durable post-treatment gains, then this starts looking less like another hair-growth drug and more like genuine follicular regeneration.

Bottom Line

PRLR is a serious and biologically credible hair-loss target, but “prolactin is the root cause of AGA” is not established.

The more interesting hypothesis is that prolactin signaling contributes to a second layer of the disease involving androgen sensitivity, stem-cell niche dysfunction, and failed regeneration.

ABS-201 is now positioned to test that directly in humans.

If it works, the biggest implication may not be that DHT was wrong.

It may be that suppressing DHT was only treating part of the problem.

2 Likes

Here is Claude Fable 5.1 high take on that:

I’ll pull the current literature on each claim in the transcript (HMI-115 macaque/human data, ABS-201 trial status, the prolactin follicle biology, and the comparator treatments), then deliver the full five-section analysis here in Markdown.# Adversarial Review: “Prolactin Is THE Root Cause of Hair Loss?! Absci’s New Drug May Prove It” (Rob English / Sean McClain interview)

Reviewer note on the source: the presenter (Rob English) is co-founder of ULO, a telehealth brand selling finasteride, dutasteride, and minoxidil formulations. That commercial interest sits in the same market as ABS-201 and is disclosed only in the closing ad read. The interviewee is the CEO of the sponsor. Both biases are filtered below.


I. Executive Summary

The video argues that androgenetic alopecia (AGA) is not adequately explained by DHT alone and that prolactin (PRL) signaling through the prolactin receptor (PRLR) sits upstream of both androgen receptor expression and hair follicle stem cell (HFSC) niche decay. The thesis is built on four legs: (1) a Bayer stump-tailed macaque study in which the PRLR antibody later called HMI-115 produced dramatic regrowth that persisted and reportedly repigmented gray hair for years after withdrawal; (2) an unpublished Absci analysis of UK Biobank data associating PRLR expression-linked genotypes with balding severity; (3) ex vivo human AGA scalp biopsies (n = 3 male donors, 3 to 6 day cultures) in which ABS-201 prolonged anagen, preserved K15+ stem cells and CD34+ progenitors, and raised COL17A1; and (4) a pharmacokinetic argument that HMI-115 failed in humans (about 14 hairs/cm2 in an open-label phase 1b) because it reached only roughly 70% receptor occupancy and oscillated, whereas a spare-receptor system like PRLR requires sustained occupancy above 90%, which Absci claims ABS-201 achieves for six months.

Live verification: the macaque data exist only in a Bayer patent, press releases, and company slides; no peer-reviewed report of the 4-year follow-up or repigmentation was found. The HMI-115 phase 1b (240 mg SC every 2 weeks, 24 weeks, 12 men, 4 women, open-label) did report a statistically significant gain of 14 non-vellus hairs/cm2, which is comparable to finasteride’s placebo-adjusted effect in meta-analysis (about 12 hairs/cm2 at 24 weeks), a comparison the video omits. The receptor-reserve premise is real: in prolactin-dependent Nb2 lymphoma cells, maximal mitogenesis occurs at about 35% occupancy. Absci’s receptor occupancy modeling for either drug is unpublished. ABS-201 phase 1 SAD data (n = 32, IV 150 to 1800 mg) show no serious adverse events and an estimated half-life of at least 65 days; MAD dosing in AGA patients is underway with interim proof-of-concept guided for 2H 2026 and full data in early 2027.

Critical gaps the video partly acknowledges: no non-balding control tissue in the ex vivo work; the Paus lab’s own 2006 and 2010 data show PRL effects are sex- and site-specific and that a PRLR antagonist actually inhibited hair shaft production in female frontotemporal follicles; the link between COL17A1 loss and human AGA (as opposed to chronological aging) remains inferential; and a sustained pan-tissue PRLR blockade is functionally an induced hypoprolactinemia, which in men is associated in cohort data with sexual dysfunction, metabolic syndrome, and type 2 diabetes risk. The presenter’s claim that 60 to 90% of oral minoxidil users develop hypertrichosis is contradicted by meta-analyses (pooled 23 to 35%, strongly dose-dependent).

Bottom line: a plausible, mechanistically coherent hypothesis with Level D support, an unpublished PK rescue argument, and a real but modest human signal. The December 2026 readout is a safety and directional read, not an efficacy verdict.


II. Insight Bullets

  1. The DHT-centric model of AGA is not being replaced; McClain explicitly positions PRL as upstream of androgen receptor expression, adding steps to the existing causal chain rather than contradicting it.
  2. The core clinical claim is regeneration of fully miniaturized (vellus) follicles, not just anagen prolongation, which no approved therapy reliably does.
  3. HMI-115 originated as a Bayer endometriosis program (BAY 1158061) and pivoted to hair after an incidental mouse observation by Andreas Busch.
  4. Busch, who ran the original Bayer macaque work, is now working with Absci and co-authored the underdosing hypothesis; this is the same person defending the same thesis with a new molecule.
  5. The macaque regrowth claim in the 2019 Bayer/Hope Medicine license announcement was “nearly doubling” terminal hairs at 6 months with effect sustained 2 years post-treatment; the video’s “100+ hairs/cm2” and “4 years of continued regrowth” figures come from later company presentations, not a published paper.
  6. Repigmentation of gray hair in macaques is a company slide claim with no peer-reviewed report.
  7. HMI-115 phase 1b was open-label, single-arm, 16 patients, 240 mg SC every 2 weeks for 24 weeks; the 14 hairs/cm2 result was reported only for the 12 men.
  8. That 14 hairs/cm2 is roughly on par with finasteride’s placebo-adjusted meta-analytic gain at 24 weeks and about half of what oral extended-release minoxidil (VDPHL01) delivered at 6 months in a 519-man phase 2/3 trial.
  9. HMI-115’s phase 2 in AGA (NCT06118866) was planned for 192 men at 120 mg Q4W, 240 mg Q4W, and 240 mg Q2W; no peer-reviewed or registry results were located in live search.
  10. Hope Medicine has nonetheless registered a phase 3 for HMI-115 in endometriosis (NCT07318688), implying the PRLR mechanism performed acceptably in that indication.
  11. The video’s timeline is wrong on one point: the HMI-115 phase 1b press release was January 2024, not 2025.
  12. The receptor-reserve argument rests on a 1983 Nb2 rat lymphoma paper showing maximal PRL mitogenesis at about 35% occupancy; the specific “7% occupancy gives 50% effect” and “80% gives over 90%” figures could not be verified.
  13. Spare receptors in a cell line do not establish that scalp keratinocytes or dermal papilla cells share the same occupancy-response curve.
  14. Absci’s receptor occupancy model for HMI-115 (about 70% peak, oscillating) is derived from Bayer’s public PK data in postmenopausal women at 30 to 90 mg, not necessarily from the 240 mg AGA regimen; the modeling itself is unpublished.
  15. Blocking PRLR raises circulating PRL by removing short-loop dopaminergic feedback, so any dip below the occupancy threshold exposes follicles to supraphysiologic ligand. This is a coherent explanation for oscillation-driven failure, but it is hypothesis, not measurement.
  16. ABS-201 SAD cohorts used IV dosing (150 to 1800 mg); the MAD cohorts in AGA patients use subcutaneous dosing. Route and exposure differ between the safety data and the efficacy arm.
  17. Half-life of at least 65 days supports 2 to 3 injections per 6 months; this is the commercial differentiator versus HMI-115’s biweekly schedule.
  18. The ABS-201 ex vivo dataset was generated by Ralf Paus’s lab, the same group that first showed human follicles make PRL in 2006.
  19. Paus’s 2006 catagen-induction work used occipital (non-balding) follicles from facelifts and transplants, and used 400 ng/mL PRL, a level seen in macroprolactinoma, not normal scalp.
  20. The same group’s 2010 JID paper found PRL promoted hair shaft elongation in female frontotemporal follicles and that a PRLR antagonist inhibited shaft production and promoted catagen. The video does not mention this.
  21. Sex- and site-specific PRL effects are a direct problem for a “PRL is the root cause” framing and a practical problem for enrolling women.
  22. The UK Biobank PRLR-genotype analysis is unpublished. Published MPB GWAS with 250+ loci consistently headline AR/EDA2R, WNT10A, and others; PRLR is not a marquee locus in those papers.
  23. The presenter’s spare-receptor rebuttal to the genetic data is sound: if 10% occupancy is enough, small expression differences should be biologically irrelevant.
  24. The ex vivo n = 3 male donors, 3 to 6 day organ culture, with no non-AGA control tissue, cannot distinguish an AGA-specific mechanism from a generic hair follicle response to PRL.
  25. Garza 2011 established that bald scalp retains KRT15-high stem cells but loses CD34-high and CD200-high progenitors; this is the framework Absci’s stem cell data plug into.
  26. COL17A1 proteolysis driving HFSC aging comes from Matsumura 2016 in mice and aged human scalp; a 2026 review explicitly notes the human AGA link is inferential.
  27. Arrector pili muscle detachment as a point of no return comes from Sinclair’s group; Sinclair himself has written that it is unclear whether APM regression is cause or effect.
  28. Rodney Sinclair ran the HMI-115 phase 1b and sits on Absci’s ABS-201 scientific advisory board.
  29. Stump-tailed macaques respond to minoxidil with vellus-to-terminal conversion that regresses on withdrawal, and respond best early in balding; monkey magnitude routinely exceeds human magnitude.
  30. Latanoprost produced 5 to 10% vellus-to-terminal conversion in macaques but only small density gains in human trials; setipiprant (PGD2 antagonist) failed outright in a placebo-controlled phase 2a despite observational and mechanistic support. The “graveyard” warning is well founded.
  31. The presenter’s 60 to 90% hypertrichosis figure for oral minoxidil is inaccurate; pooled meta-analytic rates are 23 to 35%, and dose-dependent (10% at 0.25 mg, 33% at 1.25 mg, about 49% in one 5 mg RCT).
  32. Veradermics’ phase 2/3 data showed 3.5 to 6.3% hypertrichosis in men, but 21.4% in the female phase 2; the discrepancy is sex- and dose-related, not necessarily an AE-capture artifact.
  33. The AE-collection question McClain deferred (spontaneous report vs. structured questionnaire) remains unanswered and materially affects comparability of safety data.
  34. The stated efficacy bar, 30+ hairs/cm2 at 26 weeks, would roughly match VDPHL01 and double finasteride, but would not resemble the macaque phenotype.
  35. Interim data are guided for 2H 2026, full proof-of-concept early 2027; McClain’s “13-week December read” is directional by his own description.
  36. One-year post-treatment follow-up is built into the trial; that is the only way to test the “durable after withdrawal” claim in humans.
  37. McClain committed on record to a non-controversial data cut without subgroup-of-subgroup analyses; this is a verifiable promise.
  38. Eli Lilly made a $40 million strategic equity investment in Absci in mid-2026; it is a signal of pharma interest, not of efficacy.
  39. Absci’s claim that ABS-201 outperformed minoxidil in mice is Level D and, as the presenter says, mice grow hair in response to nearly anything.
  40. The video treats a failed trial as non-falsifying (“maybe not enough blockade”); that is an unfalsifiable posture and should be flagged as such.
  41. Sustained >90% PRLR blockade is functionally a whole-body PRLR loss-of-function state; the relevant safety literature is hypoprolactinemia in men, which the company website reportedly does not emphasize.
  42. Lactation failure and fertility effects in women are predictable from PRLR biology and are the reason postmenopausal women were used in Bayer’s first-in-human study.
  43. Absci plans an endometriosis phase 2 for ABS-201 in Q4 2026, meaning the drug’s commercial case does not rest on hair alone.
  44. Extra-pituitary PRL is under a separate promoter with different transcription factors; normal serum PRL does not exclude high local scalp PRL. This is why serum PRL screening has never implicated PRL in AGA.
  45. The hypothesis predicts finasteride/dutasteride non-responders and plateau patients should have the most to gain; the trial as described does not stratify on this.

III. Adversarial Claims and Evidence Table

Claim from Video Speaker’s Evidence Scientific Reality (Current Data) Evidence Grade Verdict
PRLR antibody regrew hair in stump-tailed macaques, with regrowth continuing 4 years after withdrawal and repigmentation Bayer macaque study, company slides Bayer patent WO2019011719 describes efficacy in the stumptail model; the 2019 license announcement states near doubling of terminal hairs at 6 months and a sustained effect 2 years post-treatment. No peer-reviewed publication of 4-year follow-up or repigmentation found. Patent; Hope/Bayer 2019. Source unverified in live search for the 4-year and repigmentation claims. D (Translational Gap) Speculative
HMI-115 regrew only about 14 hairs/cm2 in a 16-person phase 1 Hope Medicine press release Confirmed: 12 men and 4 women, 24 weeks; in men mean non-vellus target-area hair count rose 14 hairs/cm2, statistically significant. Open-label, no placebo, 240 mg SC Q2W. Press release dated Jan 2024, not 2025. Hope Medicine 2024; NCT05324293 C (uncontrolled) Plausible (but the number is not a failure by AGA standards; see next row)
14 hairs/cm2 is “a far cry” and effectively a failure Comparison to macaque result Finasteride 1 mg meta-analysis: mean difference vs placebo 12.4 hairs/cm2 at 24 weeks and 16.4 at 48 weeks. HMI-115’s uncontrolled 14 is in the same range as standard of care. Meta-analysis A (for finasteride comparator) Unsupported as framed
HMI-115 phase 2 completed in 2024 and results never released Presenter’s observation NCT06118866 (192 men, three dose arms, 24 weeks) registered; a Dec 2024 Chinese interview reportedly claimed completion. No results located in registry or literature. Trial listing. Source unverified in live search for completion status. E Plausible
PRLR has large receptor reserve; maximal effect at 35% occupancy in lymphoma cells Nb2 study Confirmed: maximal growth stimulation by PRL occurs at only 35% of maximal binding, suggesting most sites are spare receptors. Rat pre-T lymphoma line, not follicle cells. Shiu et al., 1983 D (Translational Gap) Plausible
HMI-115 only reached about 70% occupancy and oscillated; ABS-201 sustains >90% for 6 months Absci in-house modeling of Bayer PK Bayer’s published PK is from 29 postmenopausal women at 30 to 90 mg SC, not the 240 mg AGA regimen. Absci’s occupancy model for either molecule is unpublished. Nave et al., 2019. Source unverified in live search. E Speculative
ABS-201 phase 1 shows it is safe with a long half-life Company Four SAD cohorts, 32 participants, IV 150 to 1800 mg, no SAEs, mostly mild TEAEs; half-life estimated at least 65 days, supporting 2 to 3 doses per 6 months. Blinded aggregate, interim. Absci June 2026; Q2 2026 B (interim, sponsor-reported) Plausible
Phase 2 is 3:1 placebo-controlled, double-blind, in men and women, with 13- and 26-week reads McClain NCT07317544 is a Phase 1/2a, randomized, double-blind, placebo-controlled, up to 227 participants; MAD part enrolls participants including men with AGA and evaluates hair growth. 3:1 ratio and female enrollment not confirmed in registry text found. NCT07317544 B (design) Plausible
Human hair follicles make PRL locally and PRL induces catagen (Paus 2006) Foitzik/Paus 2006 Confirmed: 400 ng/mL PRL inhibited shaft elongation and induced premature catagen with keratinocyte apoptosis in organ-cultured scalp follicles. Occipital, non-balding tissue; supraphysiologic dose. Foitzik et al., 2006 D (ex vivo) Plausible
PRL uniformly inhibits human hair growth Implied by the model Contradicted in part: in female frontotemporal follicles PRL promoted elongation and a PRLR antagonist alone inhibited shaft production and promoted catagen. Langan et al., 2010 D Unsupported as a universal claim
ABS-201 prolongs anagen, blocks STAT5, preserves K15/CD34 cells, raises COL17A1 in human AGA biopsies Absci/Paus ex vivo, n = 3 Company disclosure: significant inhibition of STAT5 phosphorylation correlating with anagen prolongation, stem cell niche preservation, and potential reconversion. Not peer-reviewed; no non-AGA control per McClain. Absci Dec 2025 D Speculative
Bald scalp keeps stem cells but loses progenitors Garza 2011 Confirmed: KRT15-high stem cells preserved in bald scalp while CD200-high/ITGA6-high and CD34-high progenitors were markedly diminished. Garza et al., 2011 C (human tissue) Strong Support
COL17A1 loss anchors HFSC decline and miniaturization Matsumura 2016 Confirmed in mice and aged human scalp: DNA damage response drives COL17A1 proteolysis, HFSC aging, and follicle miniaturization; forced COL17A1 maintenance prevents it. A 2026 review notes that in human miniaturizing alopecia the evidence remains inferential; COL17A1 loss is not proven as a direct initiating cause of AGA. Matsumura et al., 2016; Review 2026 D (aging model) Plausible
Arrector pili detachment marks irreversible miniaturization Sinclair group Human histology: loss of APM contact with the bulge in MPHL/FPHL may explain largely irreversible hair loss, versus maintained contact in alopecia areata. Causality vs. consequence unresolved. Yazdabadi et al., 2012; Torkamani et al., 2014 C Plausible
PRL drives androgen receptor expression Absci unpublished data Rat prostate: growth hormone and prolactin stimulate androgen receptor levels in the immature rat prostate. Nothing in human scalp. Nat Rev Urol 2011. Source unverified in live search for scalp. D Speculative
UK Biobank genotypes for PRLR expression track balding severity Absci internal analysis Unpublished. Published MPB GWAS identified over 250 independent loci in 52,000 UK Biobank men, with AR/EDA2R dominant; PRLR is not a featured locus. Hagenaars et al., 2017; Yap et al., 2018. Source unverified in live search. E Speculative
Men who cannot make DHT never bald; finasteride works in 80 to 90% Presenter 5-alpha-reductase deficiency: affected adults show no evidence of male pattern baldness. Finasteride: durable improvement over five years vs. progressive loss on placebo. Fratianni and Imperato-McGinley, 1994; 5-year finasteride A/B and C Strong Support
Macaque results routinely exceed human results (minoxidil, latanoprost) Presenter Minoxidil in macaques: vellus follicles enlarged to terminal size, regressed after withdrawal, and regrowth was stronger in early baldness. Latanoprost: 5 to 10% vellus-to-terminal conversion in monkeys; human 0.1% latanoprost showed significantly increased density at 24 weeks vs placebo but small. Uno et al., 1987; Uno et al., 2002 C/D Strong Support
Setipiprant (PGD2 antagonist) had zero effect in men with AGA Presenter Confirmed: neither coprimary endpoint met; no hair growth improvement vs placebo on TAHC, SSA, or IGA. DuBois et al., 2021 B Strong Support
60 to 90% of oral minoxidil users develop hypertrichosis; VDPHL01’s 3 to 6% is implausible Presenter Meta-analysis (27 studies, 4,294 pts): hypertrichosis in 23% overall, 10 to 33% across 0.25 to 1.25 mg oral doses; another pooled estimate 35%. VDPHL01 phase 2/3 (n = 519 men): hypertrichosis 3.5% QD and 6.3% BID; female phase 2: hypertrichosis 21.4%. JAAD Reviews 2025; PMC 2025; Veradermics 8-K A Unsupported (premise overstated; AE-capture concern still legitimate)
Lowering PRL is safe apart from lactation/fertility Absci website (per presenter) Men: lowest-quartile PRL associated with higher odds of metabolic syndrome, arteriogenic ED, and premature ejaculation (n = 2,531); EMAS cohort (n = 2,948) links low PRL to worsening sexual function and metabolic disturbance; low PRL below 5 ng/mL associated with increased adjusted risk of type 2 diabetes in European men. Corona et al., 2009; Corona et al., 2014; Review 2024 C Safety Warning
Prolactin receptor blockade raises circulating PRL McClain Mechanistically expected (loss of short-loop feedback; PRLR-null mice are hyperprolactinemic) and the Bayer phase 1 measured serum PRL effects. Magnitude in the AGA regimen unpublished. Nave et al., 2019 D/B Plausible
Insulin receptors are a classic spare-receptor example Presenter Textbook receptor pharmacology (Kono and Barham 1971). Not re-verified in live search; the “one of 100 receptors” phrasing is a simplification. E (as stated) Plausible
Best current treatments rewind the clock 6 to 36 months then plateau Presenter Consistent with plateauing regrowth curves in network meta-analysis (finasteride/dutasteride plateau, minoxidil loses some gain after 12 weeks) but the specific “months rewound” metric is opinion. Bayesian NMA 2023 E Plausible

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B)

  • Continue evidence-based standard of care for AGA: 5-alpha-reductase inhibition (finasteride 1 mg or dutasteride 0.5 mg) plus minoxidil (topical or low-dose oral). These have RCT and meta-analytic support with 5-year durability data, and nothing in this video changes that.
  • Treat early. Both macaque and human data show larger responses before advanced miniaturization; the APM-detachment and progenitor-loss literature explain why.
  • If considering low-dose oral minoxidil, use the real hypertrichosis numbers (roughly 10% at 0.25 mg rising to about 33% at 1.25 mg; higher in women) when weighing dose.
  • Do not treat a “prolactin hypothesis” as a reason to delay proven therapy while waiting for ABS-201 data.

Experimental Tier (Level C/D, high safety margin)

  • Clinical trial enrollment in HEADLINE (NCT07317544) is the only legitimate route to PRLR blockade; it includes placebo control and 1-year post-treatment follow-up.
  • For self-directed readers, the only safe PRL-related action is exclusion of true hyperprolactinemia (serum PRL, review of dopamine-antagonist medications) in patients with diffuse or atypical shedding. This addresses pituitary PRL, not the local scalp PRL the hypothesis is about, and should not be oversold.
  • Watch the December 2026 interim read for: pre-specified AE list (libido, erectile function, semen parameters, glucose/lipids, mood), AE collection method, serum PRL trajectory, and absolute non-vellus hair counts with placebo arm shown. Absence of any of these is a red flag regardless of the headline number.

Red Flag Zone

  • Attempting to lower PRL pharmacologically (cabergoline, bromocriptine) for hair loss: no human hair efficacy data, induces hypoprolactinemia with the documented sexual, mood, and cardiometabolic associations, and does not replicate receptor blockade. Safety Data Absent for this use.
  • Gray-market or compounded “PRLR antibody” products: none exist legitimately; any offering is fraudulent.
  • Interpreting 13-week hair counts as efficacy proof in either direction; the sponsor and presenter both call it directional.
  • Treating a negative ABS-201 result as non-falsifying (“just block harder”). Sustained >90% occupancy with a 65-day half-life is a fair test; if it fails, the hypothesis should be downgraded, not rescued.
  • Women of reproductive age: lactation failure and fertility effects are predictable; there is no safety data, and Bayer deliberately restricted first-in-human dosing to postmenopausal women.

V. Technical Mechanism Breakdown

PRLR signaling. PRLR is a class 1 cytokine receptor lacking intrinsic kinase activity. Ligand-induced dimerization activates JAK2, which phosphorylates STAT5a/b; pSTAT5 dimers translocate to the nucleus and drive transcription. Absci’s ex vivo readout of reduced STAT5 phosphorylation is the correct proximal pharmacodynamic marker. PRL also engages MAPK/ERK and PI3K/AKT arms, which matter for the proliferation and survival claims in matrix keratinocytes.

Extra-pituitary prolactin. The PRL gene uses a distal “superdistal” promoter in extra-pituitary tissues that is Pit-1 independent, unlike the pituitary promoter. This is the molecular basis of McClain’s point that serum PRL can be normal while local scalp PRL is high, and why hyperprolactinemia screening has never implicated PRL in AGA. Local production has been shown in the follicle epithelium (Foitzik 2006). What has not been shown is that balding follicles produce more PRL than non-balding follicles in the same scalp.

Receptor reserve and occupancy pharmacology. In systems with spare receptors, the EC50 for response sits far to the left of the KD for binding. A neutralizing antibody must therefore reduce free receptor below the fraction needed for near-maximal signaling, which for Nb2 cells was about 35% occupancy for maximal mitogenesis. The corollary McClain draws is correct in principle: 70% blockade may leave essentially full pathway activity. The uncertainty is whether scalp cells have the same reserve, and whether Absci’s occupancy model (a PK-to-occupancy translation requiring receptor density, turnover, and antibody affinity assumptions) is right. Because ABS-201 is a noncompetitive-type blocker like BAY 1158061, occupancy is not simply displaced by the rising PRL that follows receptor blockade, but sub-threshold troughs would be.

Feedback loop. Pituitary PRL is tonically suppressed by hypothalamic dopamine from tuberoinfundibular neurons that themselves express PRLR (short-loop feedback). Blocking PRLR systemically disinhibits lactotrophs and raises serum PRL. If occupancy dips, follicles face higher ligand than baseline, a plausible explanation for cycling between anagen and catagen with an oscillating antibody.

Androgen receptor cross-talk. The proposed step “PRL increases AR transcript” has support in rat prostate (PRL/GH raise AR and IGF-1 receptor levels) and in prostate STAT5-AR interplay. In the follicle it is asserted from unpublished Absci data. Mechanistically, STAT5 can co-regulate AR target genes, so the idea is not unreasonable; it is simply unproven in scalp.

Stem cell niche. The bulge houses KRT15-high quiescent HFSCs anchored to the basement membrane by hemidesmosomes containing COL17A1 (BP180). Matsumura showed that DNA-damage-triggered proteolysis of COL17A1 (via neutrophil elastase, also MMP9) causes HFSCs to lose stemness, commit to epidermal fate, and be shed transepidermally, miniaturizing the follicle. Garza showed AGA scalp keeps KRT15-high cells but loses CD34-high and CD200-high progenitors, implying a block in the stem-to-progenitor transition. Absci’s claim is that PRLR signaling drives K15 cell apoptosis, CD34 depletion, and COL17A1 loss, and that blockade reverses all three in 6-day culture. If true in vivo, this is the only current mechanism that touches the progenitor-conversion bottleneck. The caveat is that COL17A1’s role is established for chronological aging, and PRL is one of many candidate upstream inputs (TGF-beta, DKK1, PGD2 have all been proposed for the same niche).

Catagen induction. PRL at high dose upregulates catagen effectors (TGF-beta2, reduced IGF-1 and FGF7 signaling) and induces matrix keratinocyte apoptosis. Absci reports the inverse under ABS-201: increased IGF-1 and FGF7. These are the same growth factors implicated in minoxidil and dermal papilla-mediated anagen maintenance, which is why anagen prolongation is the expected, and least novel, part of the readout.

Sex and site specificity. Langan 2010 found PRL is pro-elongation in female frontotemporal follicles while PRLR antagonism inhibited shaft production. Possible explanations include isoform differences (long vs short PRLR), estrogen receptor cross-talk, or dose-dependent biphasic responses. For the drug, the practical implication is that female responses could differ in direction, not just magnitude.

Why withdrawal durability is biologically possible but unproven. If the niche is genuinely rebuilt (COL17A1 restored, progenitor pool re-established), each subsequent hair cycle could produce a larger follicle without continued blockade, because niche integrity is self-reinforcing over cycles. This distinguishes the mechanism from minoxidil (a KATP-channel/vasodilatory anagen stimulant whose gains regress on withdrawal, in macaques and humans alike). The 1-year post-treatment follow-up in HEADLINE is the first human test of that prediction.


Sources:

If you want this as a .md file for your vault, say the word and I’ll write it out.

3 Likes

I’ve been thinking about this drug ever since I made this first post. It would truly be amazing if a DHT independent mechanism for hair loss was discovered, but if this were paired with the ability to reverse greying hair then that is even better!

I had some shower thoughts this morning after the gym - If cabergoline and similar drugs blocking prolactin secretion from the pituitary doesn’t stop hair loss, but blocking the receptor does, then this could mean a number of different things:

  1. Something other than prolactin can agonise those receptors and is the cause
  2. It’s possible that DHT is that molecule and 5AR blocking DHT production (among other hormonal changes) stops that from happening. DHT can impact estrogen receptors for instance via its metabolite 3β-androstanediol.
  3. Cabergoline might block pituitary production of prolactin but if there is local paracrine production at the hair follicle site then it could never prevent it from hitting the receptor.
  4. If this is the case it might actually prove a unifying theory of hair loss for men and women despite male and female pattern hairloss manifesting differently. This can be true due to sexual dimorphic hormonal and receptor density/location differences impacting the prolactin receptors at the hair follicle differently.

I rushed out the shower and started discussing this with ChatGPT thinking I might have come up with some unique thoughts that could contribute ideas to hair loss reversal and grey hair reversal science.

Here is the final output resulting from my discussion with ChatGPT on the subject:

The more I have looked into prolactin receptor blockade for hair loss, the more interesting the mechanism has become. If drugs such as ABS-201 ultimately produce strong results in humans, I think the next experiments could potentially overturn some long-standing assumptions about how male and female pattern hair loss actually work.

We already know that human scalp follicles are both a source and target of prolactin. They produce prolactin locally, express prolactin receptors (PRLR), and high prolactin exposure can inhibit hair-shaft elongation, reduce follicular proliferation and induce premature catagen.

More importantly, this local follicular prolactin system appears to be partly independent of circulating prolactin. Isolated human follicles continue producing PRL without any pituitary input, and dopamine, which strongly suppresses pituitary prolactin, does not significantly suppress follicular PRL. IFN-γ and TNF-α, however, can modify the local PRL/PRLR system.

This could explain something that otherwise seems strange: lowering serum prolactin and blocking PRLR are not necessarily equivalent interventions.

Cabergoline can crush pituitary prolactin while leaving locally produced follicular prolactin relatively untouched. A PRLR antibody blocks the receptor regardless of whether the ligand came from the pituitary, the follicle itself, or potentially another hormone.

There is even another possible PRLR ligand to consider: human growth hormone can activate human PRLR.

So PRLR blockade could potentially eliminate signaling from:

local PRL + circulating PRL + GH

while simply lowering circulating prolactin does not.

The primate experiment is what makes this hard to ignore

An earlier PRLR antibody, mat3, was tested in naturally balding stump-tailed macaques. Nine of eleven animals responded. Terminal hairs in previously bald regions increased by 50 to 220 hairs/cm² in responders, with an average 109% increase in terminal hair count in bald regions. Both males and females responded, and much of the improvement remained six months after treatment ended.

HMI-115 subsequently produced a statistically significant mean increase of about 14 non-vellus hairs/cm² after 24 weeks in 12 men with AGA in an open-label Phase Ib study.

ABS-201 is a different PRLR antibody. In androgen-sensitive human frontotemporal scalp tissue ex vivo, it has been reported to prolong anagen, inhibit catagen, increase hair-matrix proliferation, increase IGF-1 and FGF7, decrease TGF-β2 and protect/expand K15+ stem cells and CD34+ progenitors. Interestingly, it produced effects even without added prolactin, consistent with blockade of prolactin being produced inside the follicle itself.

ABS-201 is now in a placebo-controlled Phase 1/2a study designed for up to 227 participants, with hair count, hair width and pigmentation among the efficacy measurements. Human efficacy remains the critical unanswered question.

Is PRLR actually more fundamental than DHT?

I would not say that yet.

The evidence that DHT is causally involved in male pattern baldness remains extremely strong. But PRLR could potentially sit downstream of DHT, amplify androgen signaling, or represent a parallel pathway that converges on the same follicular regression machinery.

There is already evidence outside hair biology that PRLR-associated STAT5 and androgen receptor signaling can strongly cooperate. Active STAT5 can increase AR transcriptional activity, while activated AR can reciprocally increase STAT5 activity.

That creates a potentially very different model:

DHT → AR → PRLR/STAT5 interaction → catagen and miniaturization

rather than simply:

DHT → miniaturization.

If PRLR blockade prevents DHT from producing the normal pathological follicular phenotype, PRLR could turn out to be an essential downstream component of androgen-driven hair loss.

Local DHT may also matter more than serum DHT

There is an interesting parallel between prolactin and DHT.

Hair follicles have substantial local steroid metabolism. Human dermal papillae have particularly high 5α-reductase activity and locally accumulate DHT.

Finasteride reduces DHT within balding scalp, and topical finasteride can produce substantial scalp DHT suppression with considerably less serum DHT suppression at lower topical doses.

So perhaps both systems need to be thought about locally:

serum prolactin ≠ follicular prolactin exposure

and potentially:

serum DHT ≠ intrafollicular DHT signaling.

This might help explain why anecdotal experiences with high circulating or exogenous DHT do not always resemble what one might expect from the conventional AGA model. That does not establish that exogenous DHT is harmless to hair, but it makes local intracrine DHT production worth studying independently.

Could PRLR also unify male and female pattern hair loss?

This may be one of the most interesting possibilities.

Male and female pattern hair loss look different and have different relationships with androgen biology, yet both ultimately involve progressive follicular miniaturization and shortened anagen.

The macaque PRLR experiment produced substantial regrowth in both males and females, despite their different endocrine environments.

That raises the possibility that male and female pattern hair loss have different upstream drivers but converge on common follicular machinery involving PRLR.

In men, DHT/AR might provide a particularly strong upstream signal.

In women, estrogen balance, androgens, local prolactin regulation, thyroid-related signals and other sexually dimorphic factors might feed into the same receptor system differently.

PRLR would then not necessarily be “the cause” of either condition. It could instead be a shared bottleneck through which different hormonal environments push susceptible follicles toward regression.

There is also a potentially druggable local prolactin target

Human extrapituitary prolactin can be transcribed using a different upstream promoter and an additional noncoding exon, exon 1a, while still producing the same final prolactin protein as the pituitary.

We do not yet have good evidence proving that scalp follicles specifically use exon 1a, and that should be established first.

But if they do, an intriguing treatment strategy becomes possible:

selectively knock down the extrapituitary PRL transcript in scalp follicles while leaving pituitary prolactin alone.

An exon-1a-specific ASO or siRNA delivered into follicles could theoretically accomplish something that cabergoline cannot.

Alternatively, the transcriptional machinery controlling follicular PRL could be screened against existing drugs. The fact that dopamine fails to suppress follicular PRL while IFN-γ and TNF-α alter it proves that the local system has distinct pharmacological regulation.

The experiments I would most like to see

If PRLR blockade proves strongly effective in humans, I think the next step should be an aggressive mechanistic program using human follicles and appropriate animal models:

  • PRLR blockade + exogenous high testosterone
  • PRLR blockade + exogenous high DHT
  • PRLR blockade + experimentally increased follicular 5α-reductase
  • dutasteride + exogenous high testosterone
  • dutasteride + exogenous high testosterone + exogenous DHT to bypass the 5AR blockade
  • each of those conditions with and without PRLR blockade
  • direct local AR blockade/degradation versus PRLR blockade
  • PRL neutralization versus PRLR blockade
  • GH neutralization versus PRLR blockade
  • combined PRL + GH neutralization versus PRLR blockade
  • matched frontal/vertex and occipital follicles
  • male versus female follicles under matched hormonal conditions

The extreme androgen conditions make far more sense initially in follicle cultures and animal models than in people.

Crucially, these experiments should measure actual intrafollicular testosterone/DHT, AR transcriptional activity, PRLR/STAT5 signaling, anagen/catagen, follicle diameter, pigmentation, IGF-1, FGF7, TGF-β2 and stem/progenitor populations, rather than simply counting hairs.

One result would be particularly transformative:

very high DHT + intact AR signaling + PRLR blockade = no miniaturization.

If that happened reproducibly, it would strongly suggest that DHT cannot execute much of its pathological effect without PRLR-associated machinery.

If DHT still caused substantial miniaturization, but PRLR blockade independently improved growth, then the pathways are more likely parallel.

If dutasteride and PRLR blockade were strongly additive, that would also argue for partly independent mechanisms.

What about the huge prolactin rise caused by PRLR blockade?

Some PRLR antibodies produce compensatory hyperprolactinemia because blocking PRLR disrupts the normal feedback regulation of prolactin.

There is currently no evidence that prolactin itself directly antagonizes androgen receptors. However, PRLR/STAT5 and AR signaling can interact, so removing PRLR signaling could potentially reduce some androgen transcriptional effects without changing testosterone or DHT concentrations.

That should be directly tested.

It would also be useful to measure DHT, testosterone, LH, FSH, estradiol, IGF-1, prolactin and androgenic features during PRLR treatment. Proper male sexual-function measurements would be valuable too. So far, there is no clear signal that PRLR antibodies produce finasteride-like sexual effects, but libido and erectile function have not been rigorously characterized in the hair-loss trials.

Why this matters

If PRLR blockade genuinely works in humans, I think its greatest scientific value may be that it gives us a completely new lever for dissecting hair-loss biology.

For decades, the major way to protect male scalp hair hormonally has been to reduce DHT production or interfere with androgen signaling.

The ideal outcome would be very different:

leave testosterone intact
leave systemic androgen signaling intact
leave the physiological functions of DHT intact
but prevent genetically susceptible scalp follicles from responding by miniaturizing.

In other words, men might no longer have to choose between maximizing androgenic physiology and protecting their hair.

Whether PRLR blockade can actually achieve that remains completely unproven. But if the upcoming human results are strong, the experiments above could tell us more about the true hormonal architecture of pattern hair loss than almost anything done in the field so far.

A final note: Male sexual side effects from 5AR drugs do bother me a lot. To me it is a cruel joke for men to have to choose between libido and hair. While I don’t appear to have hair loss, I can see how hair loss would be incredibly devastating due to how it impacts how people perceive you and thus your self-perception.

I’m looking forward to when we have solutions that enable men and women to alleviate hair loss simply and easily without risking serious side effects. And if this works out to be more effective than 5AR inhibitors we can sidestep the emotionally charged debate between both camps :joy:

Why reverse gray hair? I remember that people who go gray early seem less likely to get cancer. Plus, gray hair is cool now, and a lot of young people are dyeing their hair white.

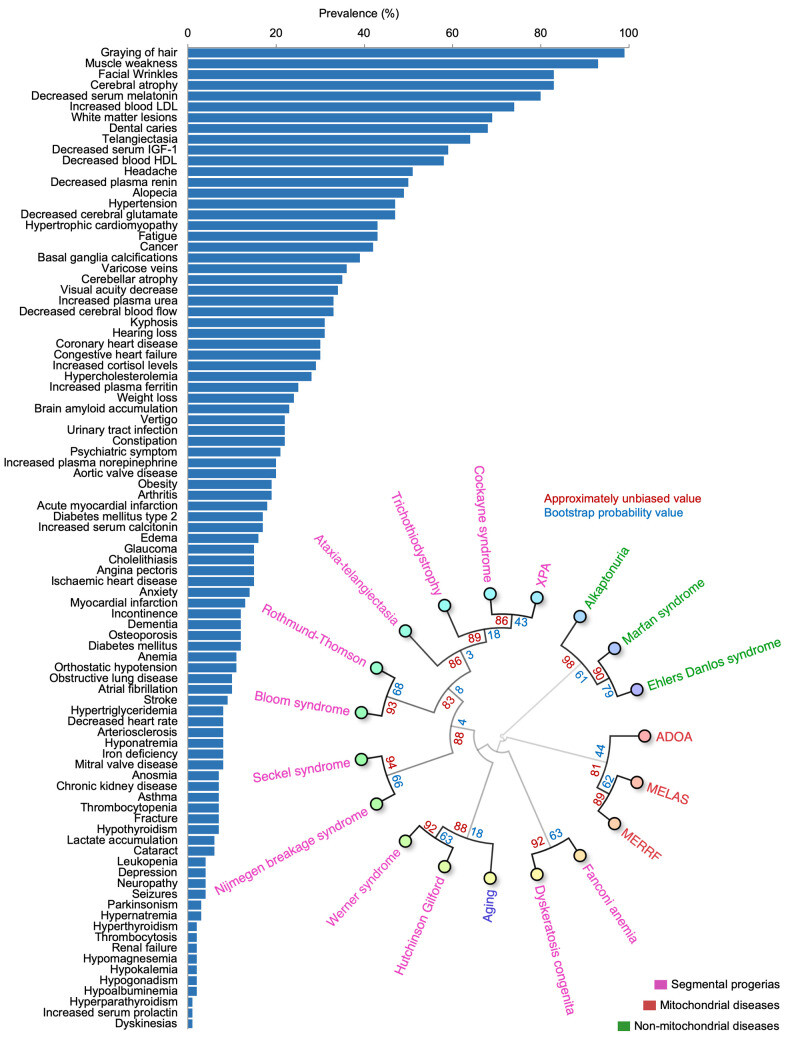
Because it is the number 1 phenotype of aging


Source: A defined human aging phenome - PMC

That’s the tail wagging the dog. People who go grey early possibly staved off cancer by going through the graying process by sacrificing damaged melanocyte cells.

https://www.nature.com/articles/s41556-025-01769-9

If people want to make the decision to dye their hair that is their choice. Some people think bald guys look tough and cool, if nature cursed them with balding they suddenly don’t like this choice being foisted upon them. I think it is the same with this trend of dyeing hair grey/white.

1 Like