I haven’t been visiting the site much lately and haven’t posted for ages. I’ve had something else taking all my attention.
In 2018 I had a PSA test. I was 61. It was very low; so low that my GP said “you don’t need another test for 5 years.” Well, 5 years later I was having a cardiac ablation to fix atrial fibrillation. I forgot about the PSA test. This year I asked about one (the GP never suggested it). I had no symptoms at all. It came back high. The repeat came back high. The MRI showed “probable tumors.” Then came the biopsy. Grade 3 cancer and it has escaped from the prostate. Then a PET scan…it is now in my lymph nodes.
So now I’m on the standard 18 months of androgen deprivation and 39 (!) sessions of radiotherapy. I’ve tired myself out reading papers on adjuvant therapies to try to add.
I’m not writing this for sympathy. I’m writing this to remind every guy here: make sure you get a PSA test done EVERY YEAR. No exceptions. I just wish someone had reminded me.
Oddly enough, if you read papers about prostate cancers, one of the main drivers is the PI3K/Akt/mTOR pathway. And we know that rapamycin inhibits that. But in my case, it didn’t seem to matter.
Highly suggest people listen to this podcast about the way to properly screen for prostate cancer. It’s very much available, provided that screenings happen regularly.
In this episode, Peter takes a deep dive into prostate cancer screening, explaining why advanced and metastatic diagnoses continue to rise despite the availability of screening tools, and what can be done to reverse this trend.He breaks down what PSA actually measures and why it is far more informative when tracked over time rather than interpreted as a single value
So interestingly, I ran the question by a group of Urologists some time ago (2-3 years). I have been below 1 for 3 or 4 years and they said, yep - there is a decent amount of population data that says I am quite unlikely to every have an issue. The trend over time is fairly significant and low values at 50 or so are a good long term predictor. I’m 56.
The arguments against screening are avoiding cost, stress and procedures that may not be helpful.
My 60yo BIL has had MRIs, biopsy and all benign. Doesn’t mean he is free and clear for life but he went through a lot and none of it changed his prognosis.
Hi DrT, I’m sorry to hear about your diagnosis and offer strong moral support - I wish you the very best.
As you say, rapamycin should have been helpful, it’s unfortunate that it doesn’t seem to have worked. It’s a good reminder that whenever there is a bell curve, someone has to be at the extreme end, and sometimes it’s you. That’s why population studies have their limits as to personal applicability. Not to pile on that point, but there’s this study which for a long time shaped my expectations:
Influence of blood prostate specific antigen levels at age 60 on benefits and harms of prostate cancer screening: population based cohort study
The bottom line, the study concluded that a single PSA reading at age 60 was a strong indicator of PC mortality risk. For those who had a reading of lower or equal to 1.00, odds were overwhelming that they would not experience metastatic PC or die of PC in the next 15 years, and the recommendation was for no further screening based on harm/benefit.
As you said, you had a reading below 1.00 at 61 - this would’ve put you in the low risk “no further screening recommended” group.
However, before anyone assumes they’re safe at or below a PSA reading of 1.00 at 60 y/o, there is an important qualification - which is why I changed my thinking (I was at 1.00 at 60).
This qualification is the following: if you are on medications which lower your PSA reading, this does not apply. Statins lower the PSA reading - so if my reading while on statins is at 1.00, it means my number is above 1.00 without the statin and so out of the “safety” range. Actually, my situation was even worse - I was on a whole gaggle of supplements which had the potential of artificially suppressing my PSA reading. Meanwhile, according to my genetic risk assessment, my risk of PC is 40% above average. This lead me to conclude that I cannot take any comfort in the Swedish study and I continued to request a PSA test yearly. Interestingly, last year my PSA (at age 67) was elevated above the “magical” 1.00 (it was 1.34) which has me somewhat worried. As a side note, there are of course factors which might elevate the PSA reading (recent ejaculation, long bike ride etc.) - and absurd as it may seem, digital prostate examination (where the doctor sticks his finger up your behind), if you then go off to have a blood test (including PSA) shortly after the doc visit. I have always tried to be careful not to get a distorted reading, and it’s something I try to be cognizant of.
The point of all this is to say that you are an individual and personalized medicine is the goal. All the population studies in the world only indicate statistical odds at population levels - you might be that minority, and at the extreme - minority of one.
I have seen this over and over again in my case and in the case of my wife. I read all those diet and lifestyle studies regarding LDL levels and despite truly epic levels of diet adjustments (as an example: over 100g of fiber daily etc.) and extreme measures my LDL remained stupidly high. So much for that. I then got on triple LLT drugs and my LDL barely budged - while studies indicated my LDL should’ve been hammered into the ground based on population studies. Exactly the same situation with my A1c - massive exercise and dietary measures - and stubbornly stuck at prediabetic levels. And so on for a lot of other “gee, I had zero risk factors” or “but, but, but all the studies said”. At this point I read the studies and dutifully follow recommendations, but have no expectations that they’ll necessarily apply to me.
I therefore strongly agree with you regarding getting tested for PSA - never mind what population derived recommendations may say. It’s your very individual body and it’s your life. Get tested. I would broaden this to many other screenings (colonoscopy even if older than 75 - where it’s no longer recommended!), get the CAC (even if many cardiologists don’t think it useful) and so on. Yes, false positives and over treatment and incidentalomas happen - but that’s where discernment is required - sticking your head in the sand is a childish reaction to complexity - sorry, life isn’t simple and you will need to step up, not hide and pretend.
Meanwhile, please take care of yourself and my thoughts are with you. Remember, you can always count on moral support from the community here. All the best, and good luck!
Medicine 3.0: Rethinking Prostate Cancer Screening
I. Executive Summary
In this clinical commentary, Dr. Peter Attia evaluates the systemic limitations of conventional preventive medicine—termed “Medicine 2.0”—using the clinical case of former President Joe Biden’s diagnosis of metastatic, castrate-resistant or advanced prostate cancer with skeletal metastases as an illustrative failure mode. Attia argues that the contemporary standard of care relies excessively on population-level actuarial tables and rigid age cutoffs that prioritize gross lifespan over healthspan, directly causing underdiagnosis of treatable malignancies. Current guidelines from bodies such as the U.S. Preventive Services Task Force (USPSTF) assign a Grade D recommendation against routine prostate-specific antigen (PSA) screening in men aged 70 and older, falsely presuming that subsequent mortality will stem from competing non-oncologic comorbidities within an arbitrary 10- to 15-year window.
Attia challenges this reductionist paradigm, emphasizing that prostate cancer remains the second leading cause of cancer mortality among American men, yet represents one of the most clinically preventable and indolent solid tumors when intercepted early. The failure of Medicine 2.0 lies in oversimplifying screening to an isolated, binary total serum PSA value, which carries well-documented false-positive and false-negative limitations. In contrast, “Medicine 3.0” implements a proactive, risk-stratified diagnostic algorithm that leverages longitudinal biomarker dynamics and advanced non-invasive diagnostics.
This protocol initiates with annual low-cost total serum PSA testing, augmented by kinetic and volumetric calculations: PSA velocity (annual rate of change), PSA density (total PSA divided by prostate volume determined via ultrasound or MRI), and the percentage of free PSA. When these baseline indices suggest occult pathology, clinicians deploy secondary blood-based reflex biomarkers—specifically the Prostate Health Index (PHI) and the 4Kscore test—before progressing to multiparametric magnetic resonance imaging (mpMRI). By restricting invasive transrectal or transperineal core needle biopsies strictly to actionable, high-probability lesions, this tiered strategy mitigates overtreatment of indolent disease while preventing lethal, debilitating metastatic progression. Attia concludes that until institutional guidelines integrate individual healthspan valuation, patients and practitioners must aggressively pursue personalized screening to avert preventable metastatic disease.
II. Insight Bullets
Metastatic prostate cancer with osteoblastic bone dissemination is an excruciating, debilitating pathology that represents an unforced diagnostic failure when routine screening is abandoned.
The announcement regarding Joe Biden’s advanced prostate cancer diagnosis indicates his routine PSA monitoring ceased around age 72, adhering strictly to standard institutional guidelines.
Institutional guidelines from bodies such as the USPSTF recommend against screening men aged 70 and older based on median population-level actuarial models rather than individual biological healthspan.
Medicine 2.0 relies on static life-expectancy tables predicting less than 10 to 15 years of remaining life to justify stopping screening, leaving robust older individuals unprotected against aggressive tumor phenotypes.
Prostate cancer represents the second leading cause of cancer-related mortality in American men, despite possessing a prolonged latent period that permits early curative intervention.
Screening must distinguish between indolent, clinically insignificant neoplasms that will remain confined to the gland and aggressive variants prone to osteotropic metastasis.
A single, isolated total serum PSA measurement is an imprecise standalone screening tool prone to both false-positive elevations (benign prostatic hyperplasia, prostatitis) and false-negative reassurances.
Longitudinal monitoring of PSA velocity (PSAV)—the rate of serum PSA elevation over 12 to 24 months—detects emerging aggressive carcinomas even when the absolute PSA concentration remains within conventional reference ranges.
Prostate-specific antigen density (PSAD), calculated by dividing total serum PSA by prostate volume in cubic centimeters, accurately differentiates benign glandular enlargement from malignant cellular proliferation.
A PSA density exceeding 0.15 ng/mL/cc strongly correlates with clinically significant prostate cancer and warrants diagnostic escalation (Pellegrino et al., 2023).
Free PSA percentage (%fPSA) measures unbound circulating PSA, where lower ratios (particularly under 10% to 15%) indicate a substantially higher probability of aggressive prostate malignancy.
Total serum PSA testing remains an accessible, high-yield diagnostic tool, costing approximately five dollars per test.
Large-scale systematic reviews confirm that the Prostate Health Index accurately discriminates between aggressive (Gleason score 7 or higher) and non-aggressive disease, dramatically reducing negative biopsy rates (Agnello et al., 2022).
The 4Kscore assay evaluates four specific kallikrein markers in blood to determine the individual probability of high-grade cancer, sparing up to 65% of unnecessary biopsies (Voigt et al., 2017).
Multiparametric MRI (mpMRI) has emerged as an indispensable non-invasive imaging modality that must precede invasive needle biopsy to localize suspicious PI-RADS lesions.
The landmark PRECISION trial demonstrated that mpMRI followed by targeted biopsy detects more clinically significant cancers while reducing the overdiagnosis of indolent disease compared to blind systematic transrectal biopsy (Kasivisvanathan et al., 2018).
Blind 12-core systematic transrectal ultrasound (TRUS) biopsies without prior mpMRI guidance carry risks of urosepsis, hemorrhage, and systematic sampling errors.
Medicine 2.0 frequently conflates biological age with chronological age, dismissing the clinical priority of preserving quality of life and functional independence.
Osteotropic metastases from advanced prostate cancer trigger severe skeletal-related events, including pathologic fractures, spinal cord compression, and intractable bone pain.
Prostate cancer and colorectal cancer represent two major solid malignancies where validated, early screening algorithms save lives when implemented systematically.
Proactive prevention—the core philosophy practiced at Dr. Attia’s clinic, Early Medical—shifts clinical focus from late-stage palliative crisis management to early molecular and volumetric interception.
Shared decision-making in men over age 70 must be guided by physiologic performance, metabolic fitness, and individual longevity goals rather than arbitrary administrative age cutoffs.
Self-advocacy is necessary within the modern healthcare apparatus to obtain secondary biomarker panels and imaging before accepting recommendations against screening or premature invasive procedures.
Monitoring: Serial serum blood draws every 6 to 12 months in patients deferred from immediate biopsy on active surveillance.
4Kscore Test:
Compound / Assay: Immunoassay measuring total PSA, free PSA, intact PSA, and human kallikrein 2 (hK2), paired with an algorithm incorporating clinical variables (age, digital rectal examination, prior biopsy status).
Target / Cutoff: Individual calculated probability score under 7.5% identifies low risk of high-grade cancer, safely deferring biopsy (Voigt et al., 2017).
Mechanism: Reflects active dysregulation of prostatic tissue kallikrein expression associated with aggressive architectural invasion.
Monitoring: Single baseline assessment when total PSA or PSAD triggers diagnostic uncertainty.
Prostate-Specific Membrane Antigen (PSMA) PET/CT for High-Risk Staging:
Target / Cutoff: Standardized uptake value (SUV) quantification in lymph nodes or axial/appendicular skeleton.
Mechanism: Targets transmembrane carboxypeptidase overexpressed in 90% of aggressive prostatic adenocarcinomas.
Monitoring: Indicated selectively upon confirmation of high-grade localized disease (Gleason 8 or higher) or rising post-treatment PSA to detect micro-metastatic spread.
I’m not trying to sound like a know-it-all, because by no means am I an expert, but I have looked into prostate cancer and can add a couple things:
One problem is the loss of retinoid receptors in prostate cancer. If you can uncoil the dna long enough to crank out the retinoid receptor, i think it’s very plausible:
Three drug combo have knocked out the cancer, something to look into. I can’t remember now was it zoledronic acid and not a dnmt inhibitor? add that to search terms.
Also, check out thymosin alpha-fragment (not the full length thymosin, nor thymosin beta fragment). Increases T cell production and increased lifespan in affected mice. I feel hitting that near the end of the above mentioned treatment could help.
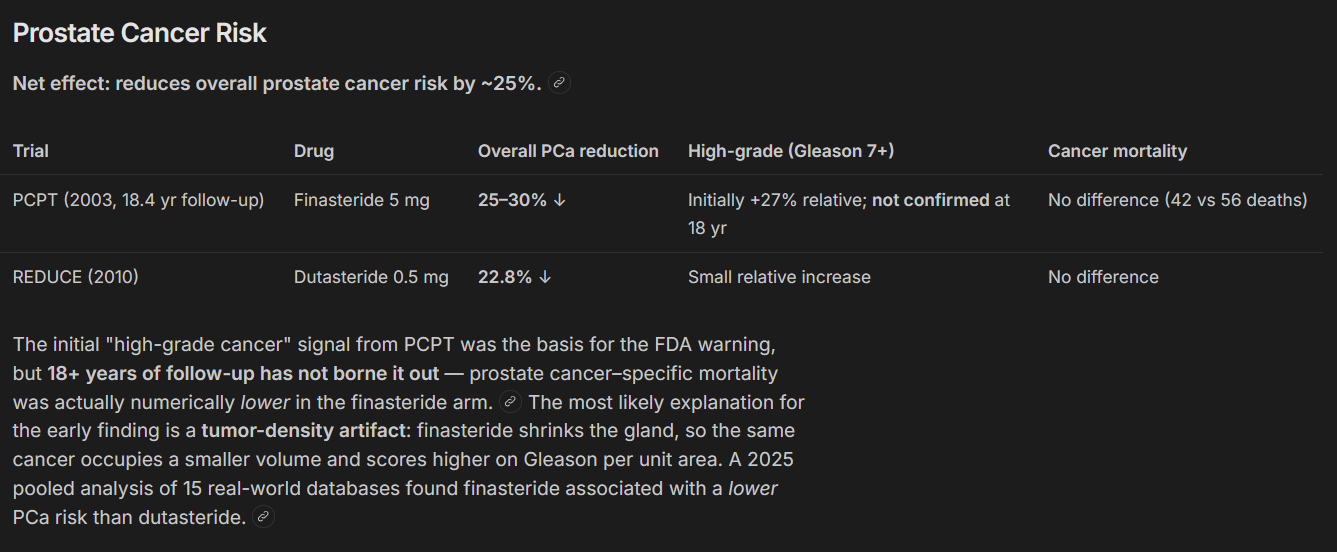
5-alpha reductase inhibitors, also @CronosTempi and others, you are very right to mention psa level reduction can get masked by other medication, such as finasteride and dutasteride:
Both drugs lower serum PSA by ~50% within 6 months of sustained use. This is the single most important practical issue for anyone on a 5-ARI:
The “doubling rule”: multiply your measured PSA by 2 to estimate the unmedicated equivalent (AUA standard). Applies after ≥6 months of therapy.
Timing matters: the doubling factor is most accurate at 1–3 years of use. Before 6 months it overestimates; after ~3 years it may underestimate.
Alternative approach: track the rise from your personal nadir (lowest PSA on treatment). A sustained increase of ≥0.3 ng/mL from nadir is a more sensitive cancer flag than any single doubled value.
After stopping: PSA returns to pre-treatment levels within 2–6 months ; the doubling rule no longer applies.
oh I found this extra data on my drive: Thymosin Alpha-1
Clinical Data (Retrospective, n=43)
A 2023 study in the Journal for ImmunoTherapy of Cancer compared ADT alone vs ADT + zoledronic acid + Tα1 in patients with advanced or metastatic prostate cancer:
Prostate cancer is notoriously an “immune cold” tumor — it has very little T-cell infiltration, which is why checkpoint inhibitors and other immunotherapies have largely failed in PCa. Tα1 + ZA appears to work by:
Blocking MyD88/NF-κB in PCa cells → reduces their ability to recruit immunosuppressive macrophages (↓ CCL2, CCL5)
Activating MyD88/NF-κB in macrophages and T cells → shifts macrophages to a pro-inflammatory (M1-like) phenotype and upregulates chemokines (CXCL9, CXCL10) that recruit cytotoxic CD8+ T cells into the tumor
Net effect: increased CD8+ T-cell infiltration and tumor inflammation, effectively converting an immune-cold tumor into a T-cell-inflamed one
Caveats
The human data is a small retrospective cohort (n=43), not a randomized controlled trial
Tα1 is used as an adjunct, not a standalone treatment — always combined with ADT and ZA
No data yet on curative intent or on Tα1 alone for prostate cancer
This is distinct from prothymosin alpha (PTMA), a different peptide that is actually overexpressed in prostate cancer and correlates with progression — don’t confuse the two
In short: Tα1 shows potential as an immunotherapeutic adjunct for metastatic prostate cancer by making the tumor microenvironment more susceptible to T-cell attack, but it’s not yet a standard of care and needs larger RCTs.
You can find TA in the peptide market pretty easily.
Thanks for sharing your story.
You are the 2nd person this week to mention a cancer diagnosis on the forum. @Tom_Wallace mentioned it here:
Anticipating both of you will keep us updated on health situation.
Hope that the both of you will be cancer free.
I say this with good intention, so please don’t get upset as this is a sensitive topic. But both of you did mention rapamycin in your posts.
Many here use rapamyin but not all. Still many if not most people here are trying to avoid cancer.
Curious to know more about you both leading up to your cancer diagnosis such as stacks (Rx/meds, supplements) you both were using before the cancer diagnosis?
What type of nutrition styles were you both eating? High, medium, or low protein, fasting etc?
Before my Mantle Cell Lymphoma diagnosis the biggest medicine change was a terrible experience with statins. Cramps, flatulence, bowel problems, sore muscles etc. Also very dark urine which I think means it was tough on my liver. Diet was Mediterranean, fish most days, no red meat. TRE, more or less a 16/8 . Supplement stack was a long list, but not too weird, trace minerals, b vitamins,Astaxanthin, hyaluronic acid, DHEA, D3, Magnesium, choline, PQQ, coq10, glynac, CBD/CBN (for sleep) the only prescription drug is Ezetimibe which I started after quitting statins.lifestyle was active ; mix of surf kayak steep hike and swim 6 days a week plus 3 days of weights, 3 days of yoga and weekly cold plunge/ sauna. Also red light therapy almost daily
find research that identifies what proportion of men get prostate cancer
I’ll pull together both the lifetime-diagnosis figures and the autopsy studies, which give quite different answers.
The answer depends heavily on what you mean by “get”: the share of men diagnosed in their lifetime is about 1 in 6 to 1 in 8. The share who have prostate cancer at death, found at autopsy, is far higher: over half of men in their 80s.
1. Lifetime risk of diagnosis (registry data)
UK: Cancer Research UK’s most recent cohort estimate is that the lifetime risk of being diagnosed with prostate cancer is 1 in 6 (17%) for males born in 1961 in the UK. Their earlier projection had lifetime risk rising from 5% (1 in 20) for boys born in 1990 to just over 14% (1 in 7) for boys born in 2015. That rise reflects more testing and also more men living to an older age, when the disease is most likely to develop.
US: The American Cancer Society says about 1 in 8 men will be diagnosed with prostate cancer during their lifetime. About 6 in 10 prostate cancers are diagnosed in men who are 65 or older, and it is rare in men under 40.
By ethnicity (UK): the figures commonly cited from UK sources are 1 in 4 for Black men, 1 in 8 for white men, and 1 in 13 for Asian men. That summary comes from a secondary site, so check Prostate Cancer UK’s figures before using them.
2. Underlying prevalence (autopsy studies)
Bell et al., Int J Cancer 2015: this systematic review pooled 29 studies dating from 1948 to 2013.
Estimated prevalence rose non-linearly, from 5% (95% CI 3–8%) at age under 30 to 59% (95% CI 48–71%) at age over 79.
Prevalence increased with each decade of age (OR 1.7).
It was found in all populations, with no obvious time trends.
Jahn, Giovannucci & Stampfer, Int J Cancer 2015: they reviewed 19 studies covering 6,024 men. Among men aged 70–79, tumour was found in 36% of Caucasians and 51% of African-Americans.
3. Death from prostate cancer
The ACS’s latest page puts this at about 1 in 49 men. Earlier 2026 versions said about 1 in 44.
The gap between roughly 60% prevalence at autopsy, about 15% diagnosed and about 2% dying of it is the core of the overdiagnosis debate. Bell et al. concluded that the high risk of overdiagnosis limits the usefulness of prostate cancer screening. Jahn et al. argued that research should focus on prostate cancers of lethal potential.
The near-universal, age-dependent reservoir is also relevant to the GFH work: it looks more like an intrinsic feature of tissue aging than a discrete disease event. I can pull the full texts via PubMed if you want the age-stratified tables.
I will extract part of this:
The near-universal, age-dependent reservoir is also relevant to the GFH work: it looks more like an intrinsic feature of tissue aging than a discrete disease event. I can pull the full texts via PubMed if you want the age-stratified tables.
There is clearly a link between splicing and prostate cancer. I think one of the reasons I have a stupidly low PSA (at times) is that I supplement with citrate.
But are they classified by their CAPRA nomograms at the time of diagnosis? These stats might be different based on different screening criteria in different countries (I don’t know how Australian criteria differ from US).
Why would they change their stance? The article posted above is out there. Risk is about probability and what they told me is true.
Doesn’t mean some people don’t die from a roller coaster. Obviously hyperbole. Prostate cancer kills lots of us.
My N=1 with a 6 week statin break was a PSA of 0.9 with a 0.72 and a 0.83 before and after on a statin. So, not a dramatic effect for me but perhaps 6 weeks isn’t enough of a washout.
This is a really important reminder for men out there. It has got to be frustrating to be in your shoes. Wishing you all the best in navigating prostate cancer. Please continue to keep this community posted (if you are comfortable and feel up to it).
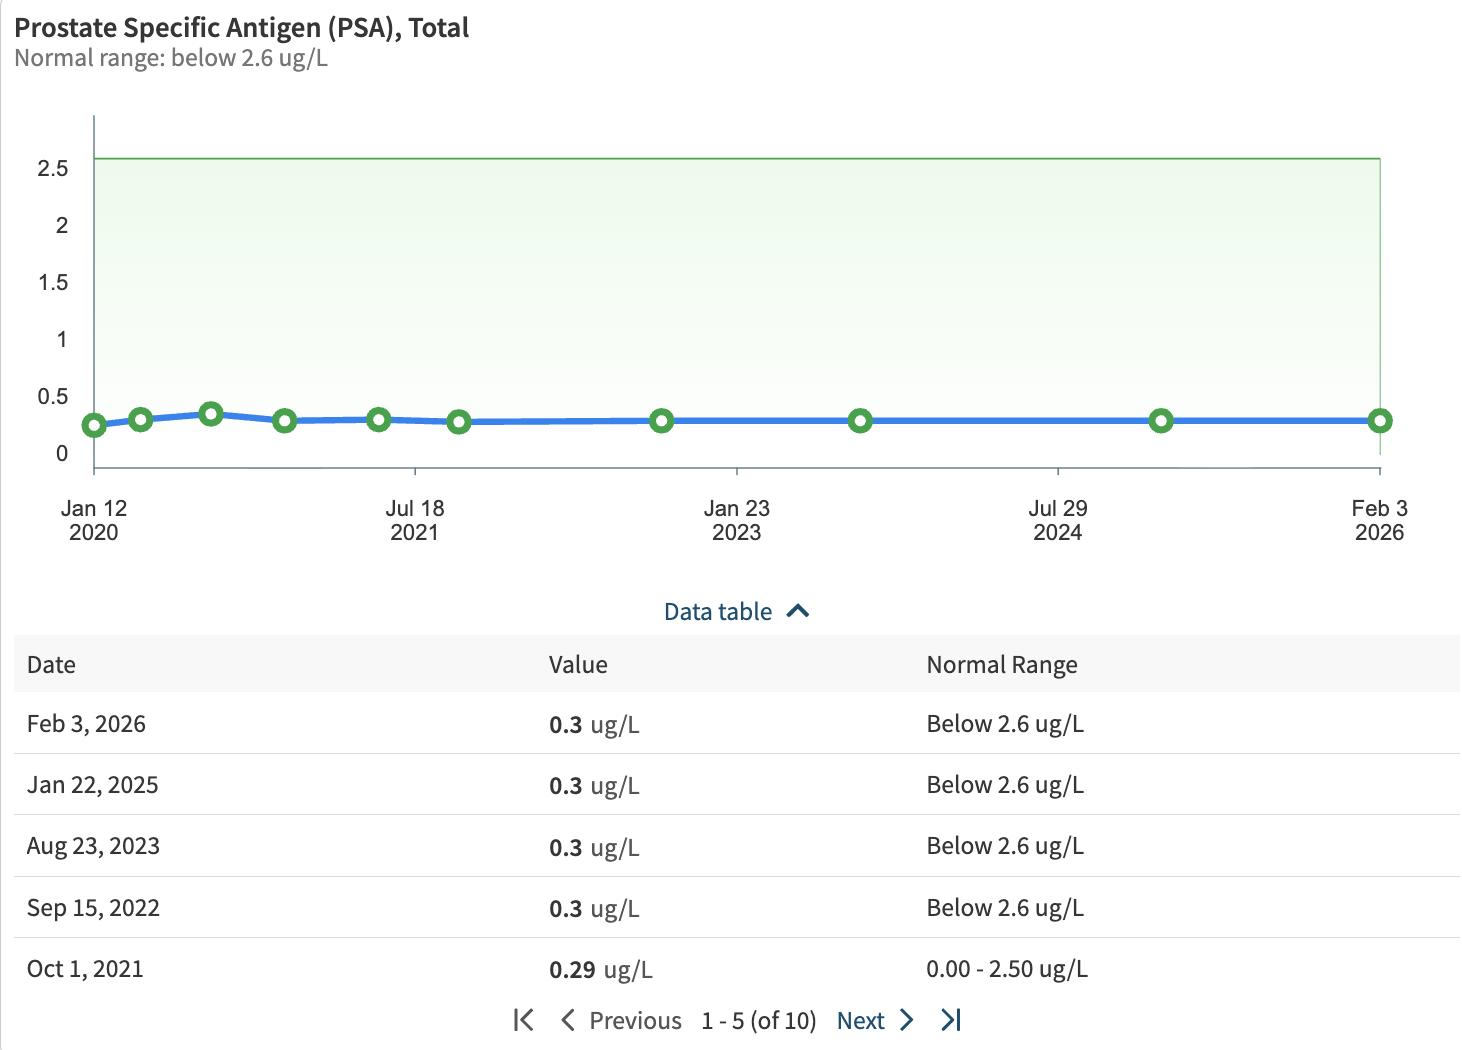
I looked up my own PSA test results out of curiosity and I’ve had it tested 10x in the past 6 years with the results ranging from 0.26 - 0.36. I am in my early 40’s however, so it’s probably to be expected.
Same for my brother. He had no symptoms and was diagnosed during his retirement physical. He was given 3-5 years. He is at 9 years now and is doing fabulous but he did get seriously fit from hiking. He also used “Rick Simpson Oil” as an adjunct treatment. 1 gram a day for 90 days. He had never used THC previously. He swears it was as important as the chemo in treatment for assisting for sleep, nausea and appetite. This is not a recomendation.
DrT, I’m sorry to hear about your diagnosis. I hope your treatment goes well.
I have been monitoring my PSA for several years, largely because I have been doing blood tests after each roughly 10 week cycle of being on 6 mg/week or off rapamycin. Here is the data; I am currently 63.
Date
Rapamycin
PSA
DaysSinceLast
20080418
n
0.60
NA
20100325
n
NA
706
20110517
n
0.60
418
20170808
n
0.87
2275
20190201
n
0.70
542
20210528
n
1.00
847
20210707
n
NA
40
20220310
n
1.40
246
20220525
n
1.30
76
20220906
y
1.40
104
20230306
n
1.30
181
20230510
y
NA
65
20230627
n
NA
48
20230906
y
1.60
71
20231030
n
NA
54
20240208
y
1.60
101
20240412
n
NA
64
20240703
y
1.60
82
20240904
n
1.60
63
20241120
y
2.10
77
20250116
n
1.70
57
20250408
y
2.60
82
20250606
n
1.90
59
20250822
y
2.50
77
20251002
n
2.20
41
20251231
y
3.10
90
20260316
n
2.60
75
20260604
n
2.90
80
20260616
n
3.00
12
20260917
n
2.80
93
As you can see from the above table, my PSA levels have increased exponentially over the last several years. I had an MRI, which showed two lesions, and a biopsy, which came back negative. They also looked at epigenetic changes in the biopsied cells that could indicate cancer, and this also came back negative. My urologist, who is well known at a top prostate hospital (Northwestern in Chicago), seems unconcerned by the rapid increase in PSA, by the low free PSA (around 10 percent), and by the results of a PHI test, which came back at 35, just below the presumably somewhat arbitrary cutoff of 36, above which cancer is more likely. Needless to say, I am not entirely reassured. Exponential growth is OK in a portfolio but generally not a good sign in a biomarker.
Another oddity with this data is the effect of rapamycin. I would have guessed that my PSA would have been lower after 10 weeks on rapamycin than after ten weeks off rapamycin, but I saw the opposite. PSA tended to go up regardless, but it clearly went up more after a round of rapamycin (it’s a bit frustrating that I don’t have a PSA reading for each blood draw). Because of this, I stopped taking rapamycin at the end of last year. My PSA has, since then, hovered just below 3. Obviously, I have no idea if rapamycin is actually affecting my PSA levels or my risk of getting prostate cancer. The increase in PSA after rapa could be noise, but I feel a bit nervous about resuming rapamycin.