Diet and Healthspan - Uncertain but High Value

Poultry, Nuts and a Glass of Wine: How an Algorithm Rewrote the Longevity Menu

Researchers in China used machine learning on dietary data from nearly 192,000 UK Biobank participants to build a 10-component “MYTH” diet score (Machine-learning YouTHful) optimized specifically to predict aging-related death rather than general disease. People in the top quartile of adherence had roughly 21 percent lower aging-related mortality in the UK cohort and about 32 percent lower in a separate US cohort, with the diet also linked to slower biological aging in the lungs, liver, pancreas, kidneys and arteries, and lower risk of 15 age-related diseases. The effects are real at population scale but statistically small per person, and because this is an observational study it shows association, not proof of cause.

For decades, dietary advice has been built by committees deciding which foods are “good” and which are “bad.” A team from China Medical University, Jilin University and Zhejiang University tried something different. They let an algorithm decide.

The idea, published in npj Science of Food, was to stop asking what prevents heart disease or cancer individually and instead ask a single question: which eating pattern best tracks with dying more slowly of aging itself. To answer it, the team pulled records from 191,689 middle-aged and older adults in the UK Biobank, screened 34 food groups against aging-related death, then fed the survivors of that screen into a gradient-boosting machine learning model that ranked each food by how much it helped predict who aged toward death and who did not.

The result is the MYTH diet, a simple 0 to 10 checklist. It rewards poultry, nuts and, surprisingly, refined grains. It penalizes processed meat, red meat, butter and sugary drinks. And it takes a notably grown-up stance on the middle ground, awarding points for moderate legumes, coffee and even moderate alcohol, whether beer or wine, while penalizing both zero and excessive intake. Several foods showed a U or J shaped relationship with mortality, meaning the lowest risk sat at a moderate intake, not at zero and not at maximum.

The payoff scaled with the score. People in the highest adherence quartile had about a fifth lower aging-related mortality than the lowest, and the pattern reproduced in an independent US cohort where it slightly outperformed three established diet indices. The team then went looking for why. Using blood proteins, metabolites and inflammation markers from tens of thousands of participants, they traced part of the benefit to lower inflammation, healthier fat metabolism and a specific immune protein called TNFRSF4. Higher scores were also tied to younger-looking organs, most strongly the lungs and liver.

The big idea is not any single food. It is the method: using population-scale data and machine learning to derive a diet aimed squarely at the biology of aging, then reverse-engineering the molecular machinery behind it. The caution is equally clear. Nobody was actually assigned to eat this way. The signal is a correlation in people who already chose their diets, so the true test, a randomized trial, has not yet been run.

Actionable Insights

The take-home foods are unglamorous and cheap: eat some poultry (about 80 grams a day or more), a small handful of nuts (20 grams or more), and keep legumes, coffee and, if you drink, alcohol to moderate amounts. Cut processed and red meat, butter and sugary drinks toward zero. None of this is exotic, and that is the point.

Now the honest part about magnitude. The headline “21 percent lower risk” describes relative risk, not your personal odds. In this study only about 7 in 100 people died of aging-related causes over roughly 12 years. Shaving that by a fifth moves the top-adherence group to somewhere near 5.5 to 6 in 100. In plain terms, that is on the order of one to two fewer deaths per hundred people over a decade, which is meaningful across a whole country but modest for one individual.

Translated into a standardized effect size (Cohen’s d, where 0.2 is considered small, 0.5 medium, 0.8 large), the top-versus-bottom quartile contrast works out to roughly d = 0.13 in the UK data and about d = 0.21 in the US data. These are small effects. That does not make the advice wrong; small, cheap, safe changes applied for decades add up. But it does mean you should not expect a dramatic personal transformation from a diet score, and you should weight it accordingly against interventions with larger evidence, such as not smoking or staying physically active.

Context and Source

  • Open Access Paper: A Machine Learning-Derived Dietary Pattern for Aging" (MYTH Diet)
  • Authors: Yating Miao, Zhirong Li, Xinyao Zhang, Zuyun Liu, Yanan Ma.
  • Institutions and country: China Medical University (Shenyang), Jilin University (Changchun) and Zhejiang University School of Medicine (Hangzhou), China. Data sources are the UK Biobank (United Kingdom) and NHANES (United States).
  • Journal: npj Science of Food (Nature Portfolio).
  • Impact evaluation: The impact score of this journal is 7.53 (2024 Journal Impact Factor; the newer 2025 JIF released June 2026 is 9.7, and its CiteScore is 7.6), evaluated against a typical high-end range of 0 to 60+ for top general science journals, therefore this is a Medium impact journal.

1 Like

Here’s a recording from Dr. Michael Greger’s webinar yesterday. This is basically the “big talk” that will go along with his speaking tour of his new book, How Not to Hurt, which will be released in about 2 months time.

3 Likes

I remember when reading his first big book (maybe it was how not to die), I quickly put on 5lbs from making an effort to eat everything he recommended! :slight_smile:

3 Likes

I’ve gotten through most of the webinar and here are a few big ideas (there are way more than I could possibly capture here):

  • The number of opioid prescriptions handed out in the US is shockingly high - almost one for each adult per year

  • The use of many common anti-inflammatory medications can result in acute pain becoming chronic pain

  • A huge number of pain related surgeries are not only unnecessary, but lead to serious adverse consequences

  • Current conventional medical treatments for back pain are largely inneffective

  • Specific food/spice items that are beneficial in better pain outcomes for a variety of conditions include cinnamon, ginger, turmeric, garlic, cocoa, green tea, berries, flax, and cruciferous vegetables

  • One doesn’t have to abandon traditional medical treatment, but should view these suggestions as complimentary and low-risk (or no-risk)

  • Reducing saturated fat intake reduces pain

  • A predominantly plant-based diet can stop migraines, osteoarthritis, and rheumatoid arthritis in the majority of patients

  • There is a fascinating relationship between arthritis and CVD

  • Every 12-18 months we replace the majority of cells in our bodies (99.5%) - these cells are replaced by air, water, and the food we consume

2 Likes

To piggyback

I started watching it too and took a screenshot of this to share:

Apparently ginger/cinnamon in double blind placebo controlled studies are shown to be as effective as NSAIDs.

He said if your particular ailment is not mentioned in the book with it’s own amounts to treat it, this is a general guide…

2 Likes

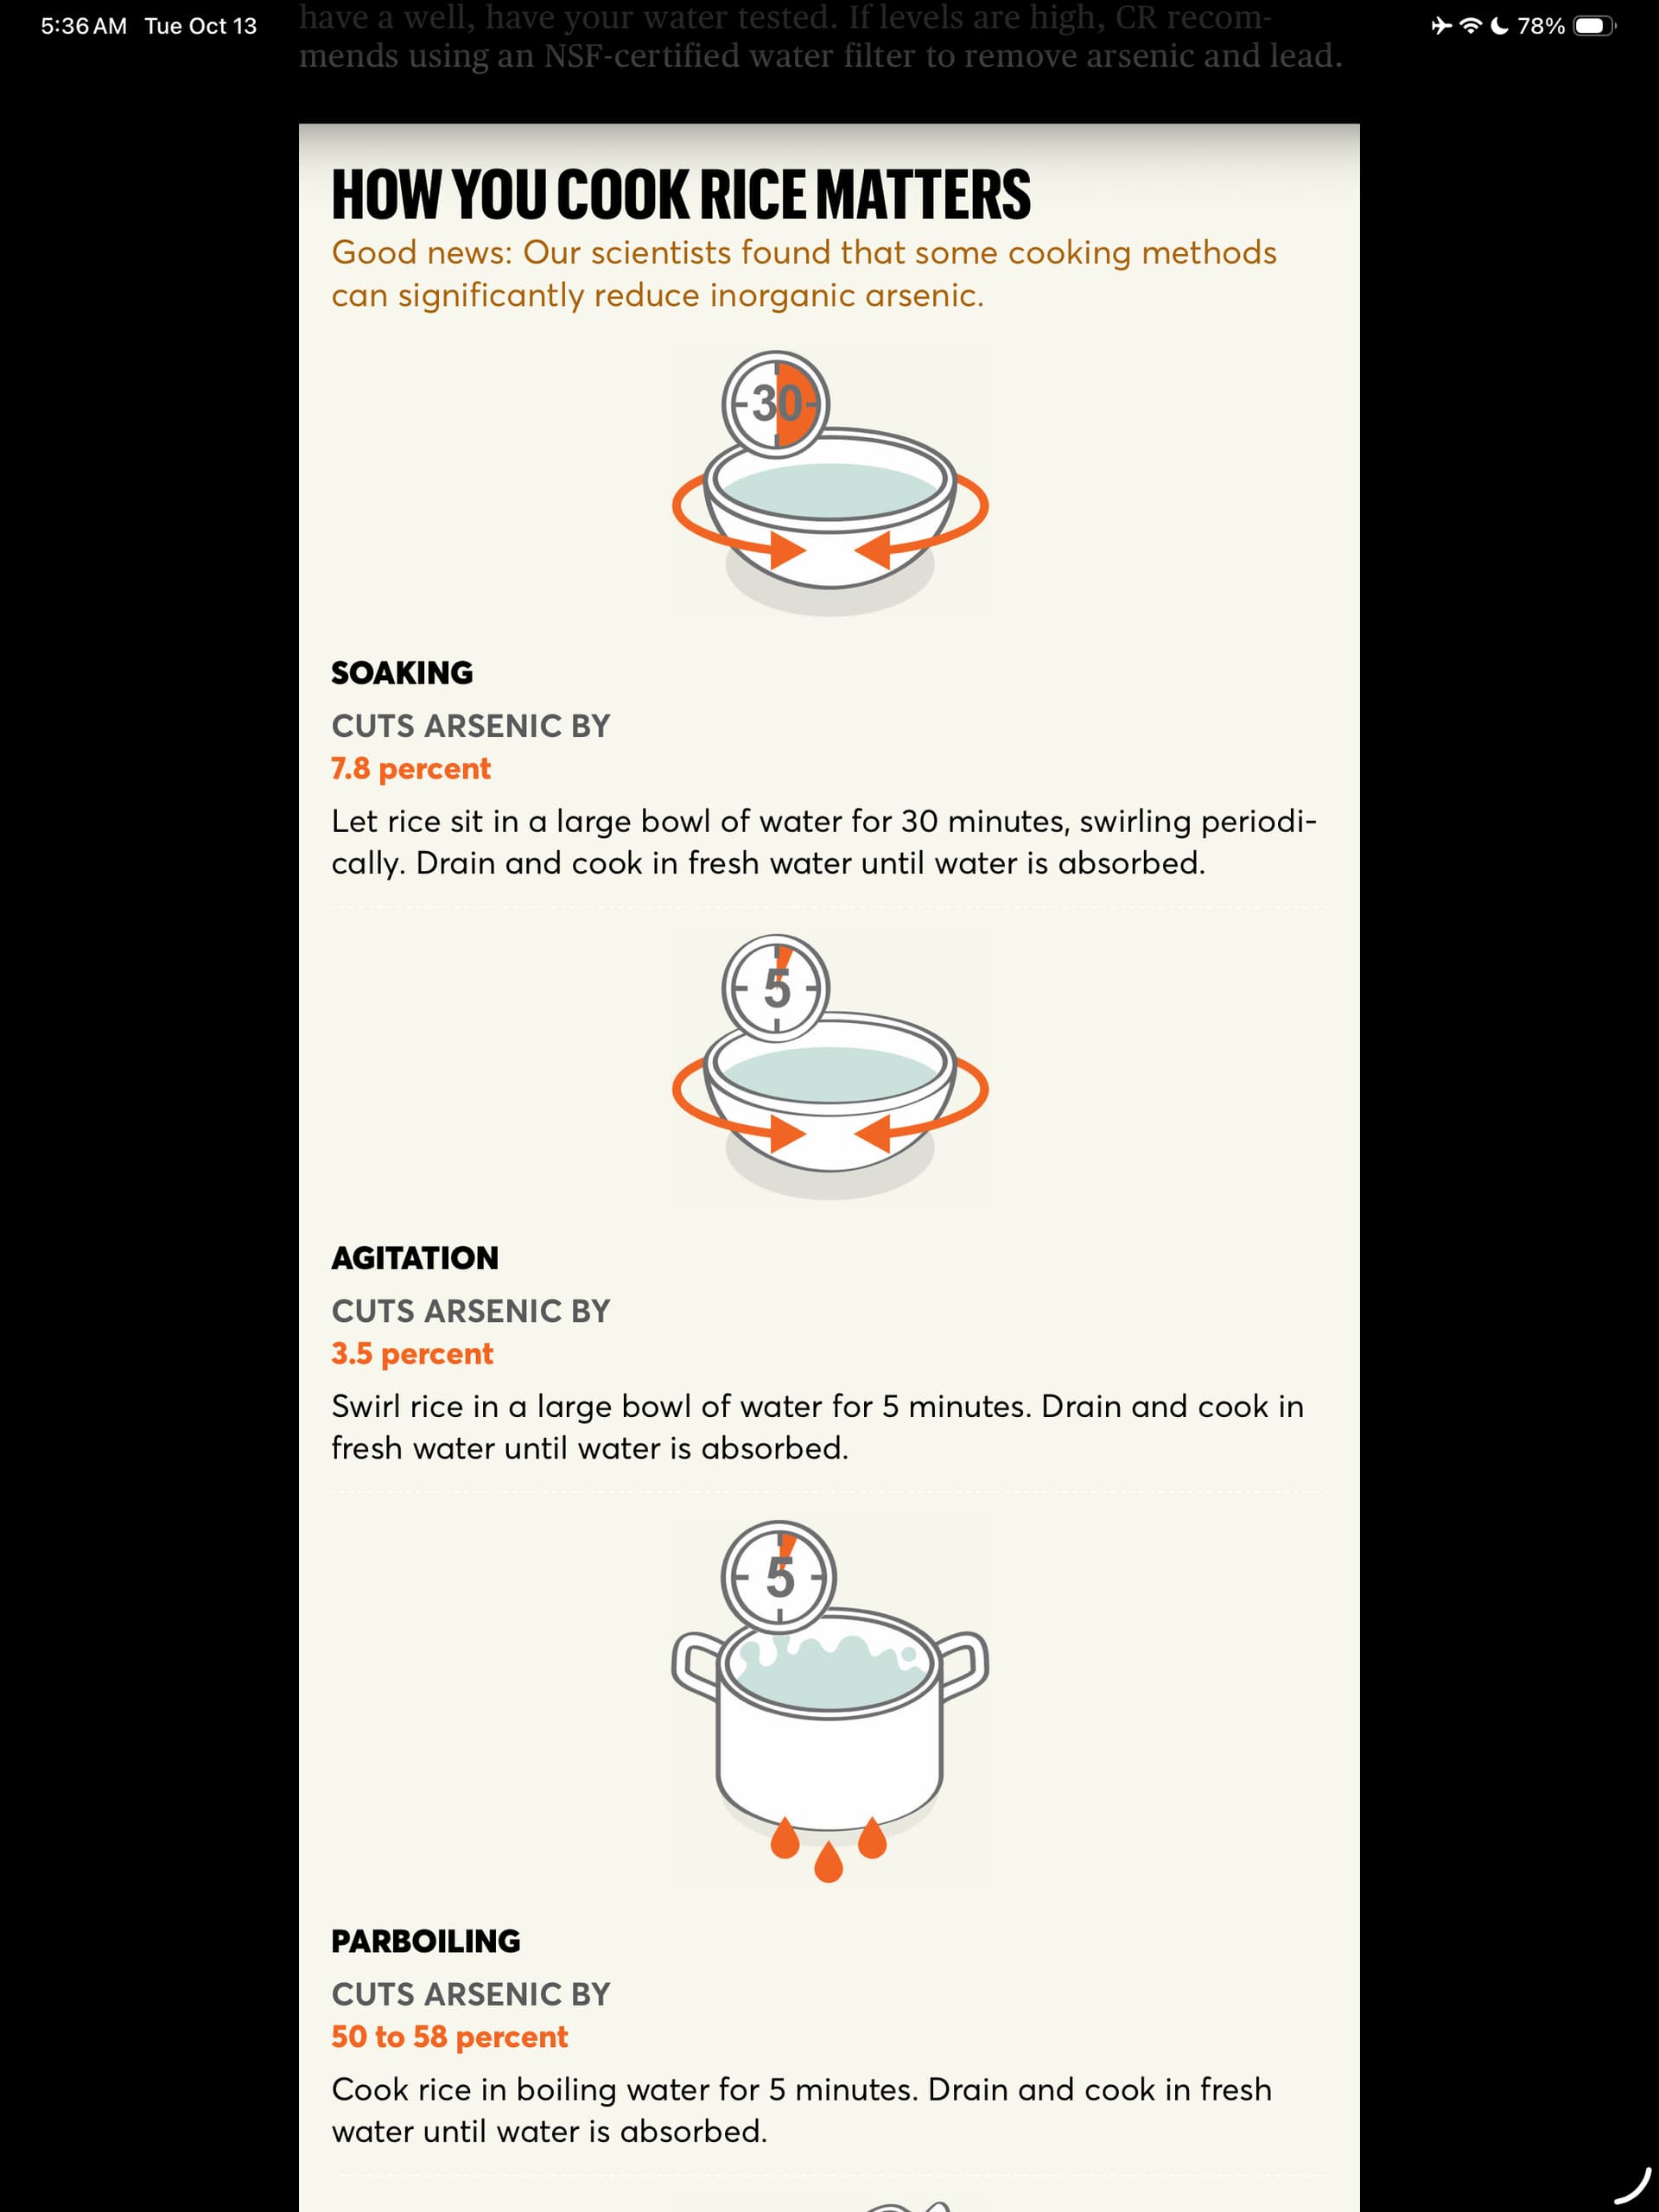
A Consumer Reports article hit Apple News Today on rice.
I don’t know how to share it for those of you who don’t subscribe.

Here are screen shots from it on how to reduce the arsenic load


2 Likes

Do a lot of people here consume rice as a regular part of their diet!? If so, I guess arsenic is one concern, and worth looking at means of reducing it - thanks!

1 Like

FWIW, I eat white rice a handful of times a year when I’m out.

In the spring (ish), there was discussion here on the health benefits of black/forbidden rice. So, since then, I started adding it to buddha bowls (I’ve probably only gone through 2-3 tiny bags).

@CronosTempi did I get anything wrong on the black rice thing?

Nope. I have it occasionally too. Mostly I’m limited by accessibility - my local Sprouts stopped carrying it, and I don’t trust the freshness in some of the ethnic stores. Rice contains fat which can become rancid. Black rice is fine, but not amazing, I wouldn’t make it a staple.

1 Like

I was even going to offer to send you some, but I see you can get some from iherb or other quality sources quite easily, incase you are interested:

https://www.iherb.com/pr/lundberg-organic-black-pearl-gourmet-rice-16-oz-454-g/108183

I go back and forth between Lindbergh organic and lotus organic from my local gourmet shop (tries to be a mini $$$ Erewhon, and after looking at iherb, I see I should be buying it there instead! )

1 Like

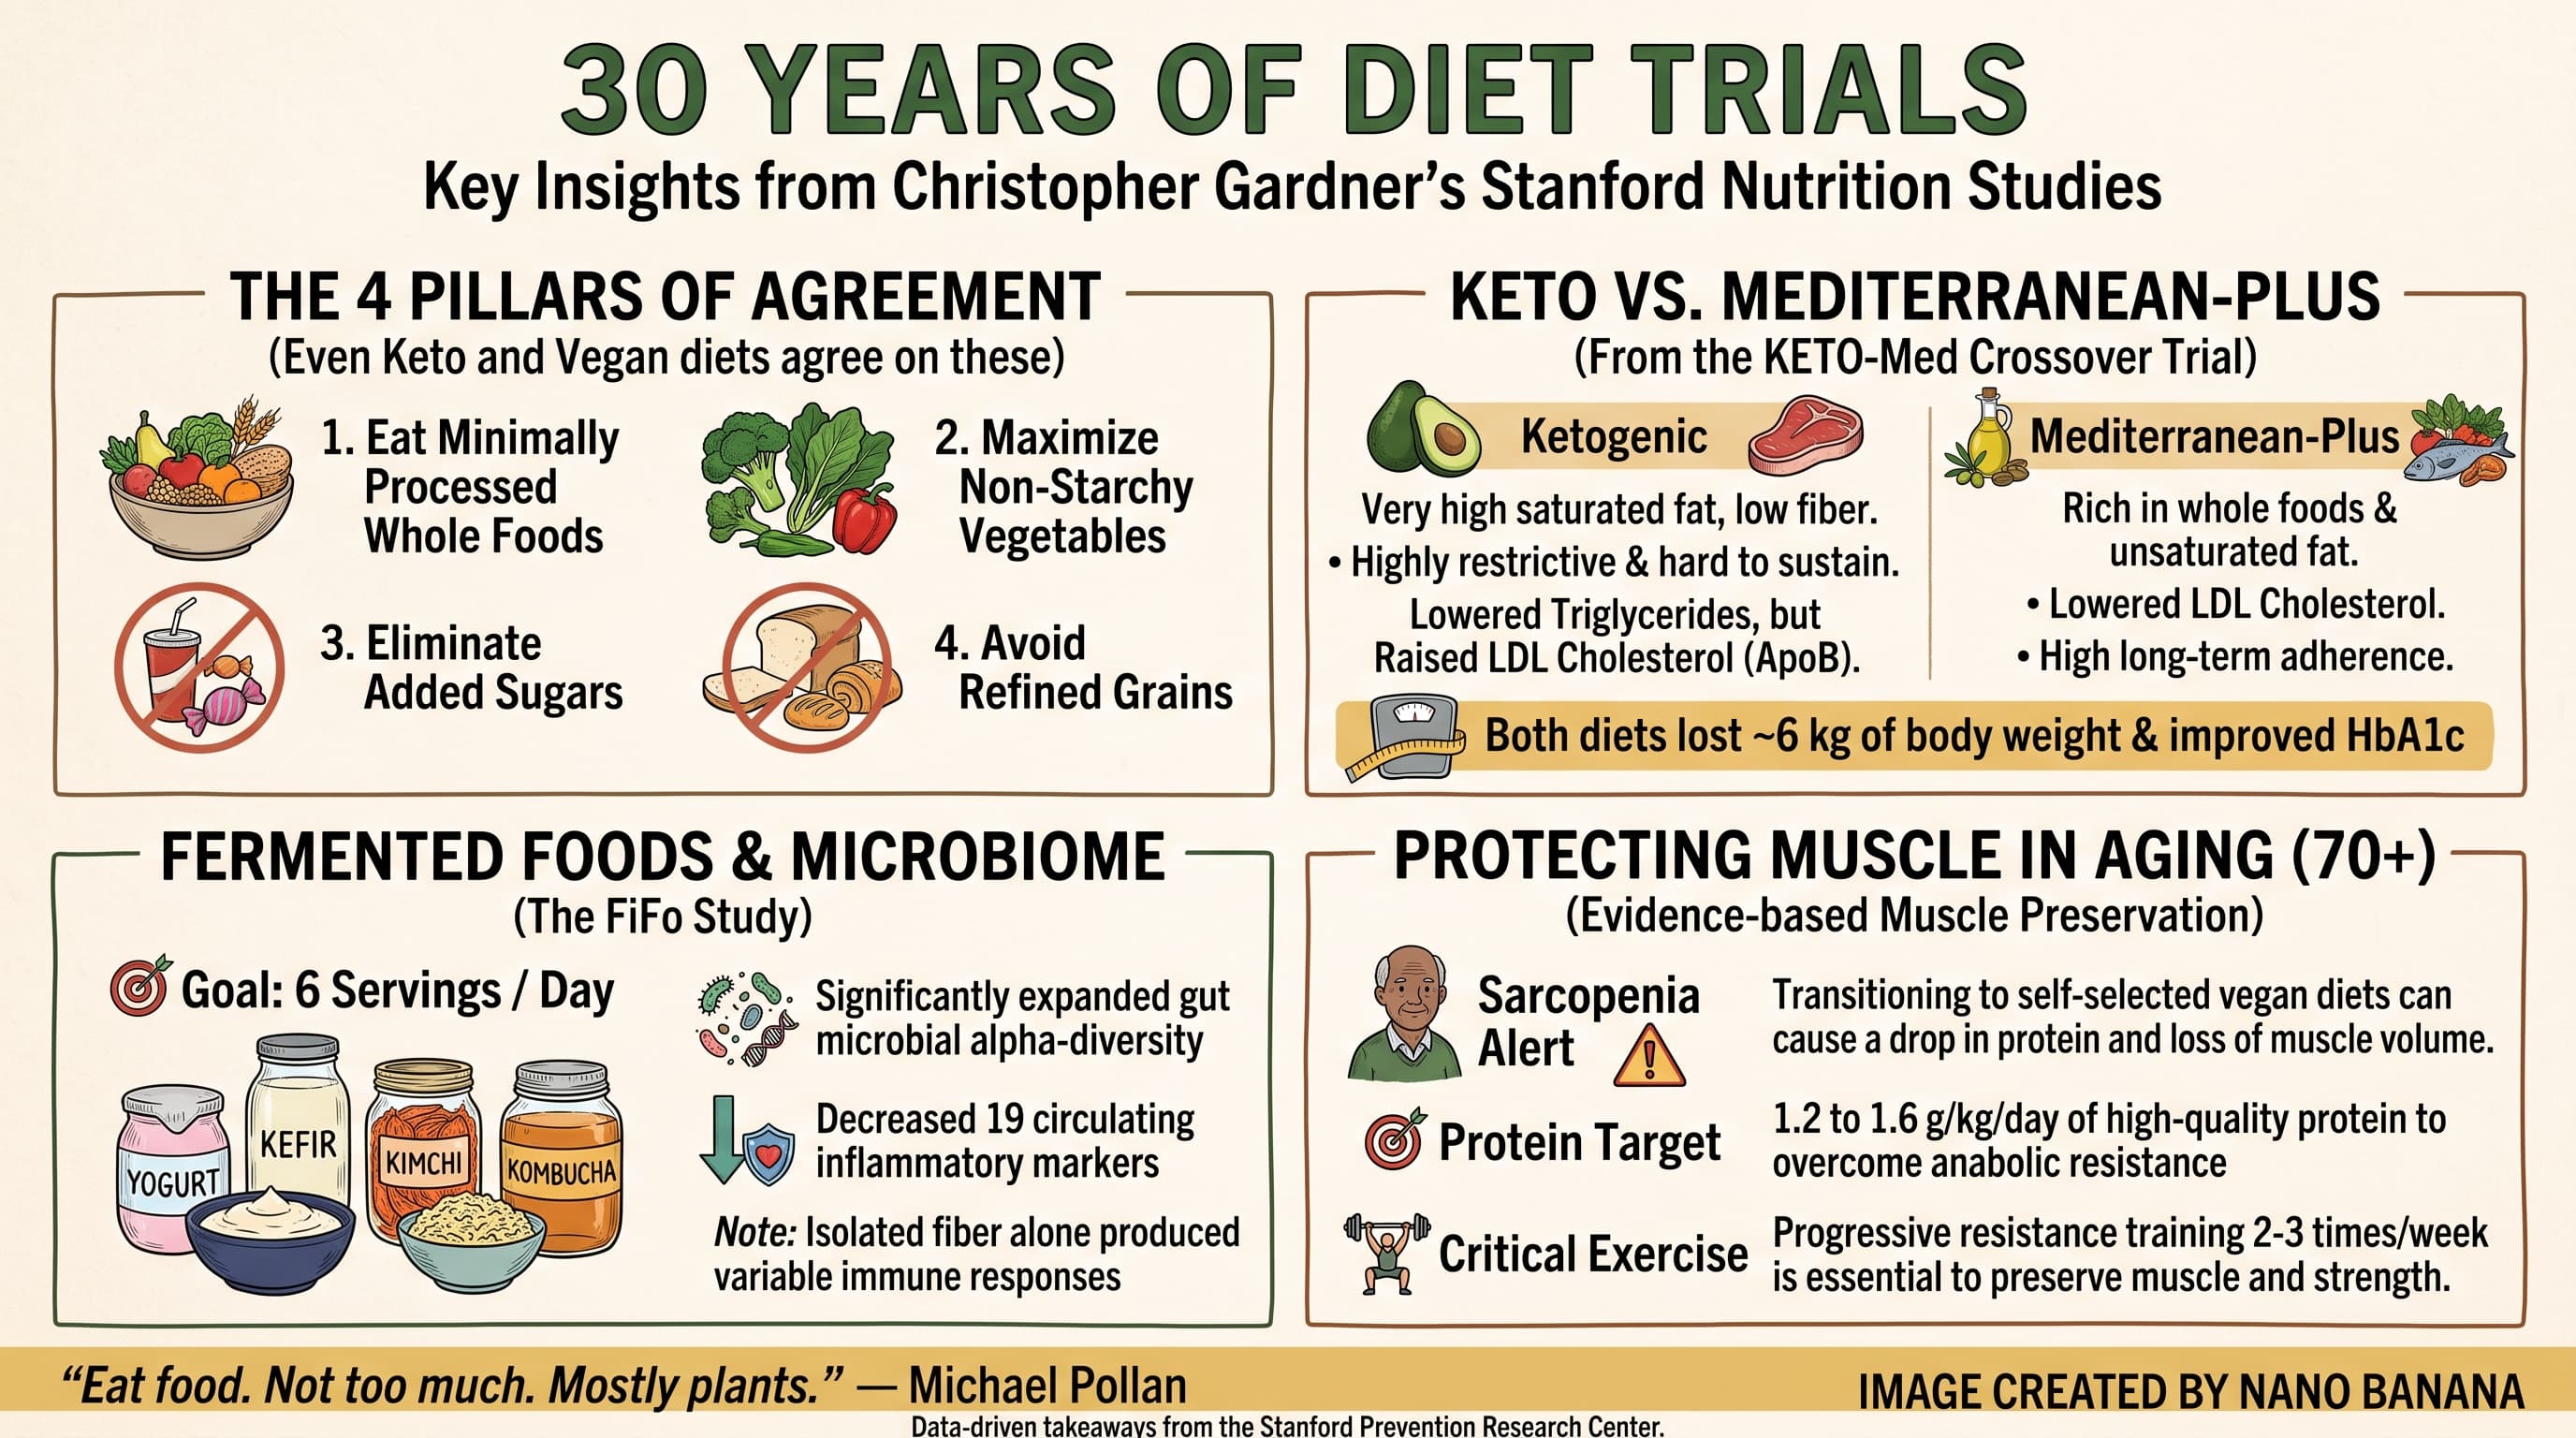
I’m a Christopher Gardner fan, so I’m sharing this because I can’t get enough of that gem!!

4 Likes

I. Executive Summary

Synthesizing thirty years of randomized controlled dietary interventions at Stanford University illuminates the fundamental epistemological tension between clinical trial rigor and real-world generalizability. Nutritional reductionism—attempting to isolate single bioactive molecules or micronutrients from whole foods—consistently fails to translate from preclinical models to clinical outcomes. This translational disconnect is exemplified by the landmark NIH-funded randomized trial by Gardner et al., 2007, which demonstrated that neither raw garlic nor enteric-coated or aged commercial garlic extracts yielded any statistically or clinically meaningful reductions in LDL-C or other lipid subfractions in moderately hypercholesterolemic adults, despite robust in vitro evidence of hepatic HMG-CoA reductase inhibition.

Dietary efficacy in free-living populations is primarily governed by behavioral adherence rather than theoretical metabolic perfection. Highly restrictive regimens—whether very-low-fat vegan or very-low-carbohydrate ketogenic diets—routinely suffer from compliance decay outside strictly controlled metabolic wards. In the randomized crossover KETO-Med trial (Gardner et al., 2022), well-formulated ketogenic and Mediterranean-Plus diets both eliminated refined carbohydrates and added sugars, driving equivalent improvements in glycated hemoglobin (HbA1c) and clinically significant weight loss (~6 kg) among individuals with prediabetes and type 2 diabetes. However, the ketogenic protocol provoked significant elevations in atherogenic LDL cholesterol and compromised micronutrient and fiber adequacy, whereas the Mediterranean dietary pattern lowered LDL cholesterol and demonstrated superior long-term behavioral sustainability. Furthermore, during active weight loss, catabolic states can mask diet-induced atherogenic lipid surges, as seen in trials evaluating severe caloric restriction and non-alcoholic hepatic steatosis.

In the gut microbiome and immune domain, the Stanford FiFo trial (Wastyk et al., 2021) established that escalating fermented food intake to six servings daily significantly expanded gut microbial alpha-diversity and decreased 19 distinct circulating inflammatory cytokines, whereas isolated dietary fiber increases produced divergent immune responses contingent upon baseline microbial richness. In geriatrics, protein source selection carries distinct physiological trade-offs: recent clinical trials from the Maastricht group (van Loon et al., 2026) demonstrate that older adults transitioning to self-selected vegan diets spontaneously dropped daily protein intake and lost thigh muscle volume over 12 weeks, an atrophy phenotype rescued exclusively through concurrent progressive resistance training. Ultimately, evaluating popular dietary patterns against the American Heart Association criteria (Gardner et al., 2023) demonstrates near-universal clinical consensus around four foundational pillars: prioritizing minimally processed whole foods, maximizing non-starchy vegetable consumption, eliminating added sugars, and heavily restricting refined carbohydrates.

II. Insight Bullets

  • Nutritional clinical trials exist along an unavoidable trade-off between strict biochemical rigor (metabolic ward feeding studies) and free-living ecological validity.
  • Attempting to isolate single nutrients from intact foods routinely fails to account for synergistic biological effects within the whole-food matrix.
  • A rigorous six-month randomized controlled trial demonstrated that neither raw garlic nor commercial garlic supplements lowered LDL cholesterol in hypercholesterolemic adults (Gardner et al., 2007).
  • In vitro findings demonstrating that garlic allicin inhibits hepatic HMG-CoA reductase failed to translate in vivo due to gastrointestinal degradation and bioavailability barriers.
  • Media reporting of null clinical trial findings frequently distorts narrow scientific conclusions into misleading public health generalizations.
  • The foundational public health dietary axiom remains Michael Pollan’s principle: “Eat food. Not too much. Mostly plants.”
  • Observational studies of ancestral and indigenous hunter-gatherer populations demonstrate low lifetime rates of cardiometabolic disease despite diverse macronutrient distributions.
  • Long-term randomized diet trials with clinical mortality endpoints are practically infeasible due to severe attrition and adherence decay over decades.
  • High adherence retention (~90%) in lifestyle clinical trials requires transparent participant screening and upfront expectation setting regarding randomization.
  • Pragmatic nutrition research must explicitly distinguish between prescribed dietary assignment and objective, measured participant compliance.
  • The Women’s Health Initiative calcium and vitamin D trial demonstrated that an intervention can fail as an intention-to-treat public health measure while remaining efficacious among adherent individuals (Jackson et al., 2006).
  • Mandating prospective trial registration on ClinicalTrials.gov serves as an essential regulatory guardrail against post-hoc data dredging and selective outcome reporting.
  • In the Stanford FiFo trial, consuming six daily servings of fermented foods increased gut microbial diversity and decreased 19 circulating inflammatory markers (Wastyk et al., 2021).
  • A high-fiber dietary intervention produced heterogeneous immune outcomes, where individuals with low baseline microbiome diversity failed to reduce inflammation.
  • Commercial probiotic and functional beverage claims frequently outpace validated human clinical trial evidence regarding microbial engraftment.
  • Industrial pasteurization of commercial fermented beverages eliminates native living microbes, requiring synthetic bacterial inoculation before distribution at bulk retailers like Costco.
  • The American Heart Association’s evaluation of popular dietary patterns ranked DASH, Mediterranean, pescatarian, and vegetarian approaches at the highest tier of cardiovascular alignment (Gardner et al., 2023).
  • Extremely restrictive diets, specifically ketogenic and strict carnivore regimens, ranked in the lowest tier of AHA alignment due to excessive saturated fat and severe fiber restrictions.
  • Every major dietary camp exhibits unanimous scientific agreement on four core principles: consume whole foods, maximize vegetables, eliminate added sugars, and restrict refined grains.
  • Legumes and pulses represent climate-resilient, nitrogen-fixing crops that provide high-density protein and fermentable prebiotic fiber without saturated fat.
  • Intact whole fruits do not confer the cardiometabolic harms of isolated fructose due to their physical fibrous cellular matrix and polyphenol content.
  • Unsaturated fats derived from intact nuts and seeds consistently associate with improved lipid profiles and reduced cardiovascular risk.
  • Dietary cholesterol from whole eggs demonstrates minimal systemic atherogenic impact in metabolically healthy individuals consuming low baseline saturated fat.
  • Cold-water fatty fish provide essential long-chain omega-3 fatty acids and high-biological-value protein that lower residual cardiovascular risk.
  • Fermented dairy, particularly unsweetened whole-food yogurt, confers metabolic benefits through lactic acid bacteria fermentation despite dairy lactose content.
  • In the KETO-Med randomized crossover trial, ketogenic and Mediterranean diets induced comparable improvements in HbA1c and body weight in prediabetic adults (Gardner et al., 2022).
  • The ketogenic diet significantly increased atherogenic LDL cholesterol and reduced essential micronutrient intake compared to the Mediterranean-Plus pattern.
  • The ketogenic dietary pattern demonstrated superior triglyceride lowering compared to the Mediterranean diet in prediabetic cohorts.
  • Active catabolism during significant weight loss (>10% body mass) transiently attenuates the circulating hypercholesterolemic response to high saturated fat diets.
  • Very-low-carbohydrate feeding drives rapid depletion of intrahepatic triglyceride content and remission of hepatic steatosis in obese individuals.
  • Digital dietary self-tracking apps exhibit steep drop-offs in long-term engagement, with only a small fraction of users logging intake consistently over one year.
  • In older adults over age 70, switching to a self-selected vegan diet led to a spontaneous decline in daily protein intake from ~100 g to ~70 g per day (van Loon et al., 2026).
  • Self-selected vegan diets in older adults induced a significant reduction in quadriceps muscle cross-sectional area over a 12-week intervention.
  • Progressive resistance training performed twice weekly rescued muscle protein synthesis and prevented lean mass loss in older adults on plant-based diets.
  • Advanced outpatient biomarker profiling platforms, such as Function Health, enable direct monitoring of functional metabolic markers including methylmalonic acid and phosphorylated tau.
  • Global food system reform requires shifting institutional procurement across universities, healthcare systems, and military dining facilities through initiatives like the Menus of Change University Research Collaborative.
  • Aligning food choices with external personal values—including planetary sustainability and animal welfare—enhances long-term behavioral dietary adherence beyond personal health metrics alone.

IV. Actionable Protocol (Prioritized)

High Confidence Tier (Level A/B Evidence)

Domain Clinical Action Dosing / Target Primary Endpoint
Cardiometabolic Alignment Adopt a Mediterranean or DASH dietary pattern rich in whole plant foods and unsaturated fats ≥5 servings/day non-starchy vegetables, ≥3 servings/day legumes/pulses, olive oil as primary lipid (Gardner et al., 2023; Estruch et al., 2018) Suppress ApoB/LDL-C, lower systolic blood pressure, and reduce major adverse cardiovascular events (MACE)
Refined Carbohydrate Elimination Restrict added sugars, sugar-sweetened beverages, and refined flour products Added sugars < 6% of total daily energy (<25–36 g/day) (Lichtenstein et al., 2021) Prevent postprandial glucose volatility, hepatic de novo lipogenesis, and hypertriglyceridemia
Muscle Preservation in Aging Perform progressive resistance training combined with adequate essential amino acid intake 2–3 sessions/week of compound resistance training; 1.2–1.6 g/kg/day total dietary protein (van Loon et al., 2026; Morton et al., 2018) Maintain myofibrillar protein synthesis, preserve quadriceps volume, and prevent sarcopenic frailty
Targeted Calcium / D3 Repletion Ensure adequate calcium and vitamin D balance exclusively in deficient or osteopenic cohorts 1,000–1,200 mg/day elemental calcium (diet + supplement) + 800–1,000 IU/day D3, emphasizing strict daily compliance (Jackson et al., 2006) Elevate bone mineral density and reduce total and osteoporotic hip fracture risk

Experimental Tier (Level C/D Evidence - High Safety Margin)

  • Fermented Food Ingestion Protocol: Systematically incorporate 4 to 6 servings daily of traditionally fermented living foods (e.g., unsweetened yogurt, kefir, kimchi, raw sauerkraut, unpasteurized kombucha). The underlying mechanism involves continuous seeding of diverse probiotic strains and biologically active postbiotics to reduce circulating inflammatory cytokines (such as IL-6) and enhance gut microbial alpha-diversity (Wastyk et al., 2021). Monitor for gastrointestinal tolerance and avoid high-sodium options in hypertensive patients.
  • Prebiotic Legume and Pulse Titration: Gradually increase whole pulses (lentils, chickpeas, black beans, split peas) to 1.5–2 cups daily. Fermentation of resistant starch and soluble oligosaccharides by colonic microbiota generates short-chain fatty acids (acetate, propionate, butyrate), which support mucosal barrier integrity and enhance satiety hormones. Monitor stool frequency and titrate slowly over 4 weeks to avoid transient flatulence.
  • Intrahepatic Lipid Depletion via Short-Term Carbohydrate Restriction: Implement an intensive, short-term (4–12 week) carbohydrate-restricted or ketogenic protocol exclusively in patients with documented non-alcoholic fatty liver disease (hepatic steatosis) and prediabetes. Restricting simple carbohydrates rapidly depletes hepatic glycogen and blunts de novo lipogenesis, accelerating intrahepatic triglyceride clearance (Gardner et al., 2022). Monitor serial hepatic ultrasound/fibroscan, fasting insulin, and ApoB to detect adverse lipid increases.

Red Flag Zone (Debunked, High-Risk, or Contraindicated)

Relying on Commercial Garlic Supplements to Treat Dyslipidemia: Ingesting raw garlic cloves, aged garlic extracts, or enteric-coated garlic tablets to lower elevated LDL cholesterol. Rigorous randomized controlled trials demonstrate zero clinically meaningful reduction in circulating LDL-C or ApoB (Gardner et al., 2007). Substituting garlic products for guideline-directed lipid-lowering therapy leaves atherogenic particle burdens untreated.

Unmonitored Long-Term Ketogenic Dieting in Patients with Hypercholesterolemia: Maintaining a high-saturated-fat ketogenic regimen in individuals predisposed to elevated ApoB. In clinical trials, ketogenic diets frequently provoke substantial elevations in circulating atherogenic LDL particles (Gardner et al., 2022), dramatically increasing lifetime area-under-the-curve exposure to arterial intimal retention and accelerated atherogenesis.

Unsupplemented Vegan Diets in Geriatric Populations Without Resistance Training: Transitioning adults over age 70 to strict plant-based diets without structured nutritional oversight or mechanical loading. In older individuals with age-associated anabolic resistance, spontaneous reductions in protein intake directly drive rapid loss of skeletal muscle volume and functional strength within 12 weeks (van Loon et al., 2026).

Produced by Gemini 2.5 Flash

3 Likes

Christopher Gardner is an S tier scientist and communicator. His concept about generalizability within populations. Learnt new things, The Great Conversation (wiki) is ongoing…

He doesn’t dismiss animal products instead believe other factors can play a part in decision making what to eat, unlike Greger’s noble lies.

Btw worth repeating. Adding a 50-50 sodium-potassium salt mix up to 1500 mg sodium a day can make home cooked for delicious. Reduce over time if wanted and improves health.

Americans consume far too much sodium — on average, over 3,100 milligrams daily. The American Heart Association recommends no more than 2,300 milligrams (mg) a day and an optimal goal of no more than 1,500 mg a day for most adults.

For most people, cutting back by 1,000 mg a day can improve blood pressure. This can help support heart, kidney and metabolic health (the way the body creates, stores and uses energy.)

Keep in mind that more than 70% of the sodium Americans eat comes from packaged, prepared and restaurant foods — not the saltshaker.

Most of us probably underestimate how much sodium we eat. Limiting sodium in our diet is part of an overall healthy eating pattern.

https://www.heart.org/en/healthy-living/healthy-eating/eat-smart/sodium/how-much-sodium-should-i-eat-per-day

3 Likes

In other news, have you heard that Ari Emanuel eats worms to help his gut bacteria?

This is a new one to me!

He’s on a quest to live forever.

Mr. Emanuel’s morning routine involves waking up at 4 a.m., stretching for 40 minutes and then doing breath work, sauna, meditation, an ice plunge and infrared light therapy before ingesting a protein shake and a cup of live worms to fight off “the bad bacteria in my gut.” He describes a recent lunch with his old CAA boss, Michael Ovitz. Mr. Emanuel writes: “He goes to the gym; he thinks that means he’s taking care of himself. But it doesn’t. I scold him. He hasn’t gotten his blood work done in years, he isn’t doing ice plunges, he isn’t doing daily breath work, he isn’t fasting. And he needs to be eating worms.”

1 Like