The difference is that people have been habituated to think of hsCRP as measuring only systemic inflammation - completely understandably - because that’s how that test has been typically used. Meanwhile, CRP is used for acute inflammation. Therefore taking “acute values” from the CRP test and thinking it means “that’s systemic inflammation” as typically measured by hsCRP is where people get confused. And here I’ve reached the limits of my explanatory skills  .
Basically it’s just a matter of scale:
AI Mode Conversation: Is the CRP and hsCRP the same blood test but with a different scale?
Is the CRP and hsCRP the same blood test but with a different scale?
Yes, CRP and hs-CRP tests measure the exact same protein in your blood (C-reactive protein), but they use different laboratory assays (measurement techniques) to capture different scales of precision [0.12]. [1, 2]
While a standard CRP test looks for large, obvious spikes in inflammation, an hs-CRP (high-sensitivity) test acts like a magnifying glass to detect very tiny, low-level changes in the bloodstream. [1, 2]
Direct Comparison: Standard CRP vs. hs-CRP
| Feature | Standard CRP Test | hs-CRP Test (High-Sensitivity) |
|---|---|---|
| What it measures | C-reactive protein | C-reactive protein (with higher resolution) |
| Measurement Range | Typically measures higher levels, usually between 10 to 1,000 mg/L. | Calibrated to measure tiny concentrations, usually between 0.1 to 10 mg/L. |
| Primary Clinical Purpose | Detecting acute (sudden, severe) inflammation. | Assessing chronic (long-term, low-grade) inflammation. |
| Common Uses | Monitoring severe infections, major injuries, or active autoimmune disease flare-ups (like lupus or rheumatoid arthritis) [0.10]. | Stratifying cardiovascular risk (heart disease and stroke risk) in otherwise healthy individuals. |
Why the Assay (Scale) Matters
The liver produces C-reactive protein in response to inflammation. However, the amount of protein generated varies wildly depending on the root cause: [1, 2, 3]
- The Standard CRP “Scale”: If you have a severe bacterial infection or a major trauma, your CRP levels shoot up drastically [0.10]. A standard lab test is perfectly designed to capture these massive numbers. However, it is not sensitive enough to accurately read the bottom end of the scale and may simply mark lower numbers as a vague “less than 10 mg/L” or “normal” [0.12]. [1, 2]
- The hs-CRP “Scale”: The plaque building up inside blood vessels causes a subtle, silent, low-grade inflammation [0.12]. This type of inflammation only raises CRP levels a tiny bit (fractions of a milligram). The hs-CRP test uses specialized chemical markers to precisely measure these minute amounts (e.g., distinguishing between 0.5 mg/L and 2.5 mg/L), which helps predict long-term heart risks. [1, 2, 3]
Because they are optimized for entirely different ranges, a doctor cannot simply substitute a standard CRP test when they are trying to evaluate your baseline cardiac risk. [1]
4 Likes
When I looked up the NHANES III measurement of CRP the minimum threshold was 2.1mg/L gradually tests have become more sensitive. I dont know of any labs in the UK that don’t beat 0.6 in sensitivity.
I looked that up because it is the data used for phenoage.
Below 0.1mg/L is probably just noise.
Yeah, same here. My hsCRP is below the minimum detectable at the hospital (lucky me).
So yes, it does break the Levine equation for sure. What I do is simply enter 0.6.
But hsCRP as a measurement is still super useful IMO - especially when you can see trends.
Whoa! That’s low, low hanging fruit of longevity to impove that. Ever had a CTCA, or even just a calcium score?
This is exactly right. All the cardiac guidelines are recommending hsCRP tests for evaluating CVD risk.
They’re not “low” but also not super high by any extent. I think around 2 is average in the population, for whatever tat’s worth. And again, not every single person is going to reliably follow this pattern. Some people with sky high hs/CRP never have a problem, and some people with low hsCRP have heart attacks anyway. But if I had to choose, I know which camp I’d rather be in from the statistical risk POV.
Hi Deborah, can you tell us more about what specific gene variant you have? LDL-C related? If you have high Lp(a) that’s also genetic.
But end of the day, we all have ~20,000 protein-coding genes and the interactions between them are far beyond our current understanding. So it’s very plausible you have crappy genetics in one aspect and they are offset by something else. For example, I have heterozygous familial hypercholesterolemia, with baseline LDL-C of around 220mg/dl, and my Lp(a) is about 80mg/dl - not good! However, I also fortunately have extremely low inflammation (hsCRP is always at the bottom of the test range) and I had a CT coronary angiogram and a carotid CT, and both are 100% clean. So I have one risk factor which maybe is offset somewhat by some other factors.
Well that’s the big question, and frankly we don’t really know (beyond the obvious like not eating a bunch of junk, sleeping well, avoiding chronic stress, moderate exercise, not being overweight etc etc). IMO, people also seem to have different baselines that are pretty stubborn to move.
1 Like
Just as an aside, traveling from Hong Kong to the USA (20+ hours of travel) tends to raise my hsCRP by 1 full point which then recedes over the next 10 days. It may recede more after that. I’ll have to do more testing.
2 Likes
Interstingly and perhaps a little sadly if NHANES III was trained at a minimum of 2.1 perhaps people should enter 2 for under 2.1 (or even 2.1). Personally I would go for it being a reasoned extrapolation to put the measured value of CRP even if below 2.1 (or below 0.6).
I have not found a lab that will give a measurement under 0.15 so far.
I wonder if that is caused by the higher radiation levels in the upper atmosphere ? If so, it might be a good prophylaxis to take 100mg melatonin every 4 hours while on longer intercontinental flights (assuming you are OK with being a bit sleepy), which should reduce the radiation hit by 30-50%.
1 Like
I’d say it’s more likely caused by sleep disruptions although radiation might play into it. It’s what I’ve noticed from my past 3 years of tests I’ve done in the USA.
1 Like
Yeah, almost certainly the massive sleep disruptions and having to re-jig your entire circadian rhythm.
Yeah maybe. Though I suspect that as you get too far outside of what the calculator expects, you break it. So I feel happy that my actual hsCRP is low, but if I put it into Levine I get a biological age of like 22, when I’m 40. While I believe I’m overall healthy, I feel the 18 year age gap is probably an exaggeration 
1 Like
relaxedmeatball: I am homozygous for the risk allele on two SNP’s on 9p21, the “heart attack gene”. My CAC score was 0.96 and the observation was that there was some plaque on the LAD. I just did the test that Gil Carvalho describes, comparing the systolic pressure on wrist to ankles and learned that I have a bit of arterial stiffness on the left leg, which also has persistent mild edema. Family history of stroke and heart attack. So all that combined with the inflammation in the 2’s – is what makes me anxious. My PCP had looked at my LDL and HDL for years and said I am fine. But once I did the genetics and showed them to him, and then asked for testing for Lp(a) – which came back at 40 --was what finally made him blink, and order imaging, and a referral to a cardiologist who specializes in lipids. So I am on repatha, ezetimibe and just added 1 mg pitavastatin. So, I am one of those types who looks healthy and is fit and yet harbors these genetic risks. If I had not done the genetics I would not have known. I wonder if one day getting a genetic profile will be part of everyone’s work-up.
1 Like
Morgan Levine’s formula is interesting as are the various other ones based upon biomarkers, but they have all quite a few complications.
On the other hand monitoring the individual biomarkers is quite complicated as we know from the various discussions on this forum. (such as the interplay between anaemia and glycation).
However, I think the biomarkers combined with functional tests is the way to go. At the moment I am puzzling about Cystatin C which is moving all over the place. I may try a second lab to see if that is the issue. OTOH all my other kidney markers are in a good place.
1 Like
I have dug a little deeper and my CRP tests have all been hs-CRP. My lowest was 0.7 in 2018. Crissman Loomis says daily walking is a great way to lower it.
1 Like
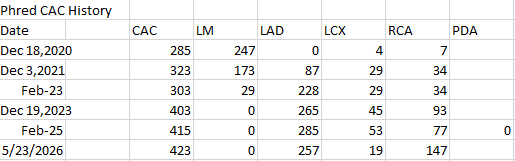
The last one was a CCTA. I do seem to have plateaued after possibly backing it up a little in 2022. I did keto and a huge amount of exercise back then, getting my 2 mile down to about 15 minutes. I think it made my CAC worse, don’t know about my ACM. I started having injuries and really can’t run like that any more. Recently got PRP for my labrum and should be better in a couple months.
The only explanation I have is hugely unpopular here. I tested high for lead and used every form of chelation I could find. High heavy metal load causes heart disease. I think it helped several of my issues and I may be on the mend now for good. My LDL has not moved in the entire time. Always between 160 and 130. I tried statins, Repatha, ezetimbe (I use it now off and on and it works some), and now Leqvio but will soon quit it because it doesn’t work at all. I know I could get the LDL down with drugs if I put my mind to it. I’m not sure it needs to be lower and defer to the judgement of my ancestral DNA.
it is the test that is high sensitivity not the CRP.
Although obicetrapib has no effect on hs CRP, it is today given marketing approval in the EU
NewAmsterdam Pharma and Menarini Group Receive European Commission Approval for Ubeslo® (Obicetrapib Monotherapy) and Evlarco® (Obicetrapib Plus Ezetimibe Fixed-Dose Combination) — NewAmsterdam Pharma
2 Likes
The European Commission approval follows the positive opinion adopted by the European Medicines Agency’s Committee for Medicinal Products for Human Use (CHMP) and is supported by data from NewAmsterdam’s comprehensive clinical development program evaluating obicetrapib, including the Phase 3 BROADWAY, BROOKLYN and TANDEM trials, which demonstrated statistically significant LDL-C reductions of up to 40% with obicetrapib monotherapy versus placebo and approximately 50% with obicetrapib combined with ezetimibe versus placebo, with a tolerability profile comparable to placebo. NewAmsterdam and Menarini continue to advance the clinical development of obicetrapib through multiple ongoing Phase 3 trials, including PREVAIL, a cardiovascular outcomes trial, as well as REMBRANDT and RUBENS.
3 Likes
I walk daily, averaging 9000 + steps, and my hsCRP is 0.2 - could be connected to staying active.
3 Likes
It appears that low levels of hsCRP and IL-6 are not meaningfully protective against MACE. It remains the case that higher levels are worse, but low levels are not protective.
1 Like