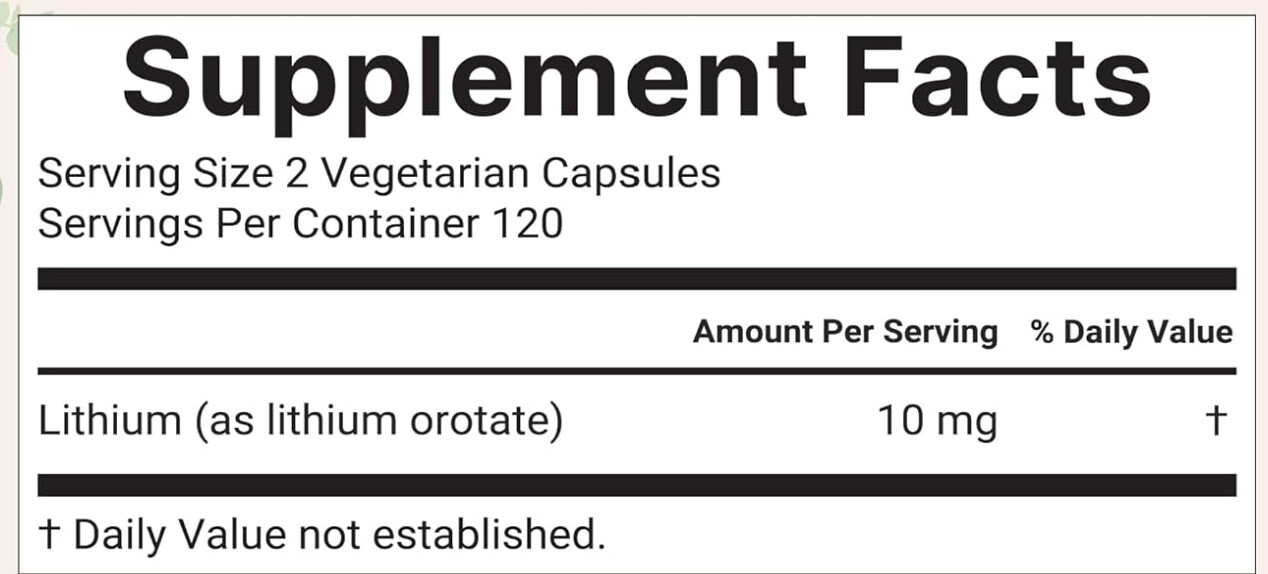
I was wondering why Matt K doubled it.
I don’t take much else other than tecta, protein pump inhibitor for heartburn. I do wonder if lower acid due to the PPI will affect absorption like it does for calcium.
I was wondering why Matt K doubled it.
I don’t take much else other than tecta, protein pump inhibitor for heartburn. I do wonder if lower acid due to the PPI will affect absorption like it does for calcium.
PPIs should not affect LiO absorption. But PPIs might discombobulate metal levels long term, magnesium etc., and there may be some interaction of all these, but nothing immediate.
Had been trying to figure out why I have had increasing edema in ankles and feet for the past few months. The inquiry led me to lithium orotate, which I had been taking, 5 mg per night. So I am cutting back the dose. But, the edema may also be exacerbated by standing, sometimes hours a day (easel), so I am monitoring that as well.
Rapamycin can cause edema
Yep… had that problem with higher dosing of rapamycin 12 mg weekly up.
Back to 6 mg weekly - no problem…
Its probably because mTOR is continually inhibited to some extent.
For folks in Canada:
Lithium Orotate is not available over the counter. It is not available on amazon.ca. However, it is available on amazon.com in the states and they will deliver over the border.
Mine just arrived today.
My conservative estimate is much closer to 1 mg daily, based on animal data and exposure levels in epidemiological studies.
I’m taking 1 mg. I didn’t feel any changes when I took it. However, at some point I stopped (finished my stock, didn’t refill, thought it might be useless) and after a couple of days I realized (or rather my wife did…) that I was reacting way more to small daily “stress”. I restarted it and went back to “stress-free” (not the correct term, but I don’t know how to describe it) after a couple of days.
Low-dose lithium was linked to lower dementia incidence vs valproate.
The HR for dementia was 0.39 (95% CI, 0.21-0.70; P=.001), favoring lithium.
Sensitivity analyses with a 90-day exposure lag confirmed findings.
Hospitalization and mortality also trended lower with lithium.
Probably higher than 1mg for those of us taking an SGLT2
Yes possibly. It’s not something I have looked into though so I can’t say if the effect of SGLT2s is large enough to be of concern here.
I’m on an SGLT2I and I take 10 mg daily. It’s great. I’ve been taking it for years.
I can’t quite recall, but my impression was also that 1mg is better.
Nah, IMO, for real benefits in mental health and life extension, you need at least 10 mg daily. I have been taking at least 10 mg for decades, and I now take 20 mg daily. It has had a dramatic impact on lowering cortisol spikes. I.e, road rage, etc.
Other than rapamycin, there is nothing on my supplement list that I like better that lithium.
It keeps me mellow and slow to anger. I think my lithium supplementation benefits those around me. 
Stress Hormones: Cortisol and adrenaline (epinephrine) spike significantly during acute anger episodes.
Blood Levels Matter for effective treatments. One size doesn’t fit all.
A 35-year-old woman struggling with 18 months of post-COVID depression, exhaustion, recurrent fevers, and persistent skin infections found relief with lithium treatment. But here’s what made the difference: monitoring her blood levels.
At a serum level of 1.14 mmol/L symptoms improved significantly. When the level dropped to 0.8 mmol/L symptoms returned
" Lithium dramatically improved patient’s mood from a “3” out of 10 best [with 7 being considered euthymic] to “7–8” at a serum level of 1.14 mmol/L. Her excessive daytime fatigue decreased from “severe and life altering” to “mild-to-moderate”. When we attempted to lower the lithium dose to achieve a serum level of 0.8 mmol/L, patient’s mood declined from “7–8” to “3–6”, and when dose was again increased to a serum level of ≥ 1.0, mood again returned to “7–8”."
This case illustrates a critical principle in personalized medicine: the same dose doesn’t work for everyone. Genetic differences, metabolism, and individual physiology mean that therapeutic monitoring—not just the drug itself—is what drives real outcomes.
Lithium’s potential for post-COVID and neuroinflammation is promising, but low-dose approaches alone haven’t shown broad benefits in trials. Higher doses with closer monitoring might be the key for some patients.
The reason for this is:
Optimal Longevity Dosing: To replicate the highest tiers of natural environmental exposure without entering the pharmacological range, longevity and biohacking communities typically utilize 1 to 5 mg of elemental lithium daily. (Note: elemental lithium is only a fraction of the compound’s total weight; for example, roughly 120 mg of lithium orotate yields about 5 mg of elemental lithium).
You have to be very careful to read the supplement ingredients. some like including Life Extension lithium orotate, which provides a clear answer to how much elemental lithium their supplement contains.
Life Extension clearly states that you get 1,000 mcg (1 mg) of actual lithium. So one capsule of this would be the actual minimum dose for lithium orotate’s benefits.

Some like this brand say:
Has anyone noticed an increased prevalence of muscle cramps when taking lithium?
Normally, I never get them, but I started getting calf cramps in the morning every few days after adding 5 mg of lithium orotate. I wonder if this is related.
For context, I also take 20 mg of Telmisartan and 12.5 mg of Empagliflozin. I am unsure of the net effect of this combination on my lithium levels.
Don’t know if your leg cramps are caused by the lithium, but a remedy that works well for me is magnesium foam – you can find it on Amazon. It’s called Theraworxx. I use it every night and no more cramps. (also take magnesium glycinate).
To confirm the AI-discussion of the LATTICE trial:
Peter Attia and Michael Rae have an equivalent essay about the shortcomings:
Key points:
Admission of patients was not based on any biomarker or measure of Alzheimer’s. AD markers were noted, but any MCI qualified for inclusion (i.e. prior strokes, vascular dementia, Parkinson’s, Huntingtons etc.). Eventually only about 25% of patients turned out to progress with AD - 75% had other causes of MCI. Prior studies essentially screened in an AD-specific patient population.
Although not planned from the outset, the Lithium dose actually delivered throughout the trial was substantially lower (less than half) of the predecessor trials of Forlenza et. al. - dosing was adjusted down to eliminate any potential chance of side effects.
Especially 1. implies, that the trial was actually vastly under-powered to find any statistically significant effects for AD specifically.