https://www.nature.com/articles/s41586-026-10940-7
chatGPT(5.6maxpaid)
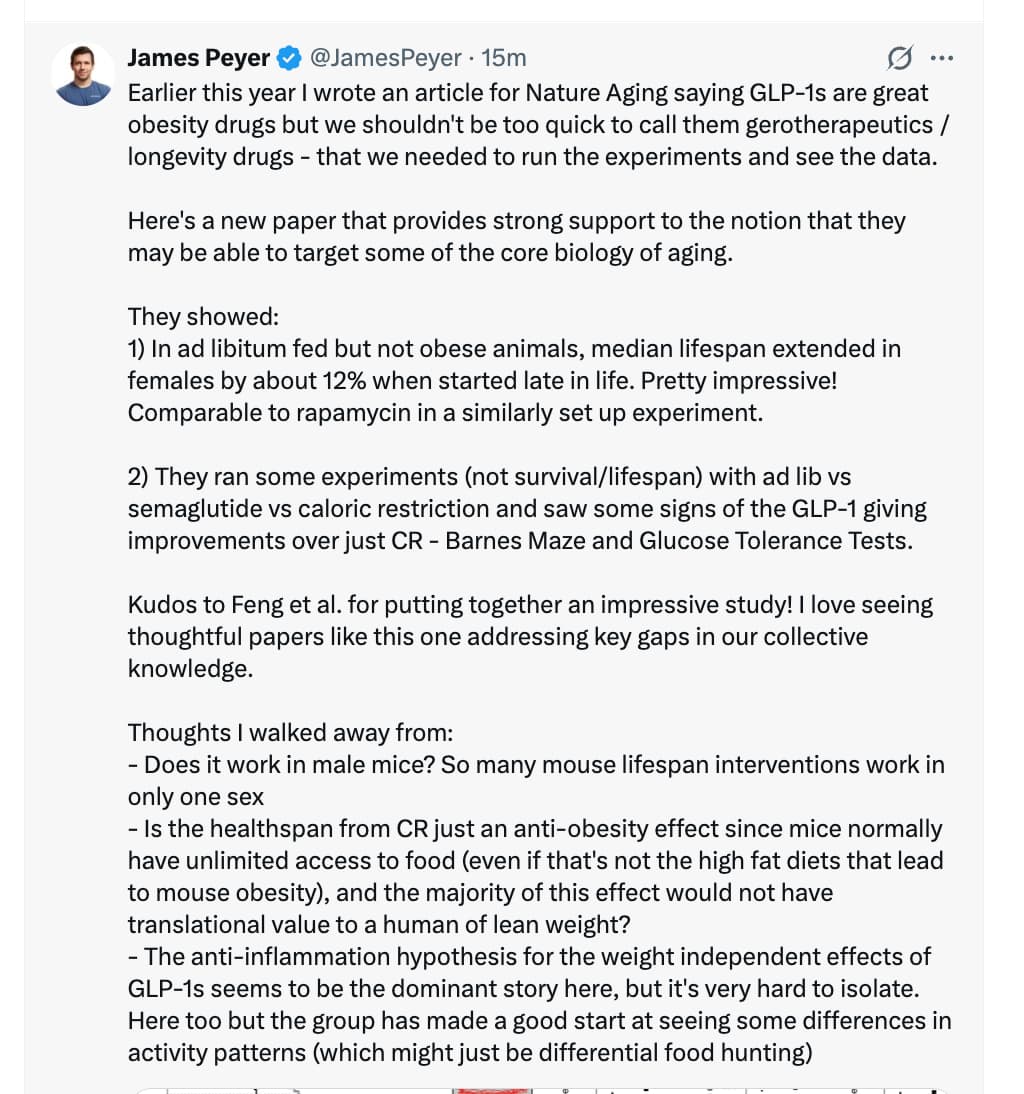
Feng et al.’s Late-life semaglutide treatment slows ageing and extends lifespan in female mice, published in Nature (2026), reports a 12.4% increase in median lifespan when treatment begins in old age.
The survival result is substantial. The main uncertainty is how much of that benefit comes from eating less, and whether the measured molecular changes actually explain the longer lifespan.
The researchers used naturally aged, 20-month-old female C57BL/6 mice eating standard laboratory chow. Semaglutide was given by daily subcutaneous injection at 10 nmol/kg.
Three separate experiments need to be distinguished:
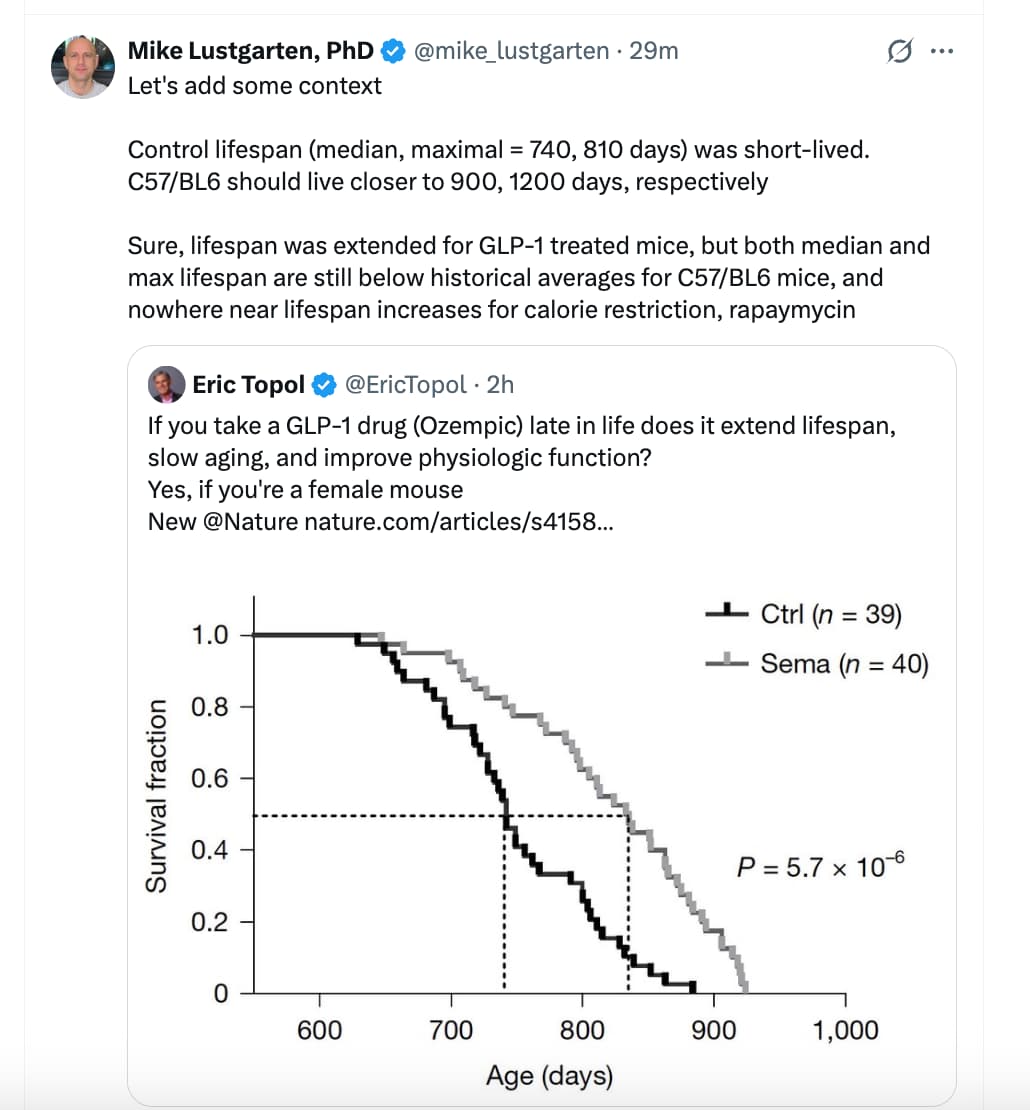
- Lifespan: 40 semaglutide-treated mice and 39 controls, with treatment continuing until death.
- Functional and biological measurements: separate animals treated for three months.
- Comparison with calorie restriction: 10 mice per group receiving semaglutide, a 24% calorie-restricted diet, or control treatment. This was a five-month experiment, with functional assessments at baseline, two months and four months.
Thus, the paper does not demonstrate that a three-month course alone extends lifespan.
The principal findings were:
| Area | What the study found |
|---|---|
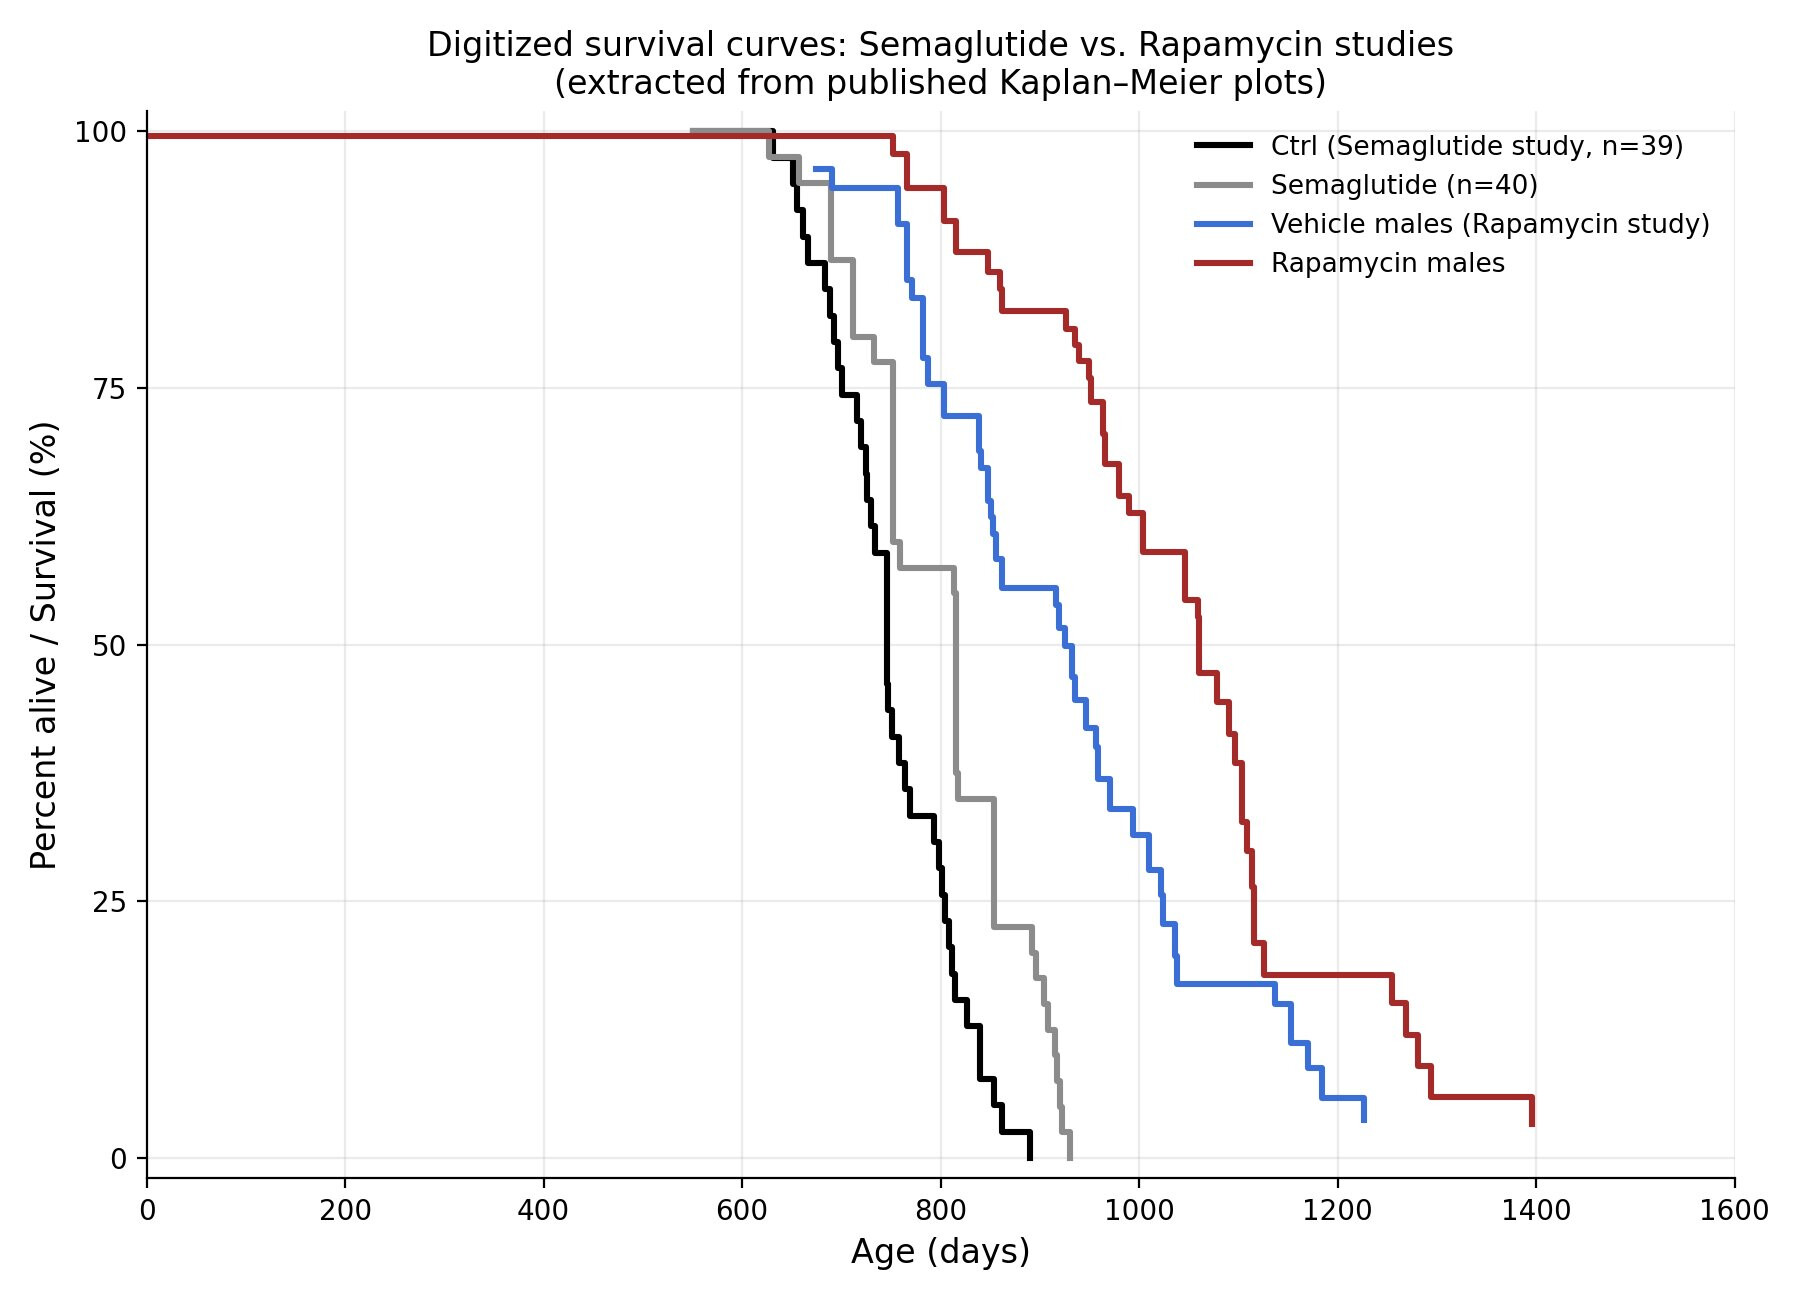
| Survival | Median lifespan increased from 742 to 834 days: an additional 92 days, with a log-rank P = 5.7 × 10⁻⁶. |
| Food intake and body composition | Food intake fell by approximately 24%. Body weight and fat mass declined; lean mass increased as a percentage of body weight. |
| Physical function | Better performance in tests of coordination, hanging endurance and treadmill endurance. |
| Behaviour and cognition | Increased exploration and better performance in the Barnes spatial-memory maze. |
| Blood-forming stem cells | Less myeloid-biased differentiation and larger colonies in culture, although colony numbers were lower. |
| Hippocampus | More BrdU-positive proliferating cells and DCX-positive immature neurons, supporting increased neurogenesis. |
| Inflammation and cellular stress | Lower inflammatory signals, senescence-associated markers, γ-H2AX staining and several protein-stress-response markers. |
| Metabolic and longevity-associated pathways | Higher muscle ATP, higher NAD⁺ in liver and muscle, increased expression of selected sirtuins and Oser1, and lower circulating IGF1. |
Liver RNA sequencing also showed reduced inflammatory gene expression and changes overlapping with previously published ageing and calorie-restriction datasets.
In the direct comparison, both semaglutide and calorie restriction preserved several physical functions as controls deteriorated. Semaglutide produced more favourable trajectories in exploration, spatial memory and glucose tolerance, including improvements above pretreatment baseline.
The paper’s clearest novelty is the actual lifespan experiment following treatment initiated late in life. Earlier work had already reported molecular and physical improvements in ageing male mice treated with exenatide, including at doses with little effect on food intake or weight; that study did not establish lifespan extension. Consequently, the general idea that GLP-1 receptor agonists influence ageing biology was already established as a research hypothesis. Huang et al., Cell Metabolism, 2025.
Two further advances are useful:
- The longitudinal calorie-restriction comparison: it distinguishes preservation of existing function from improvement above baseline.
- The combination of survival, functional and cellular findings in very old animals: particularly the blood-forming stem-cell and hippocampal results.
The experimental strengths include randomisation, substantial blinding, no reported data exclusions, and a clear survival difference. The authors also adjusted rotarod and hanging-test results for body weight, addressing an obvious alternative explanation for better performance.
My main criticisms are:
-
The lifespan experiment lacks the crucial calorie-restricted control.
Semaglutide reduced food intake by 24%, but the calorie-restricted animals were studied for functional outcomes rather than survival. The study therefore cannot establish whether semaglutide extends lifespan more than an equivalent reduction in food intake.
Calling semaglutide a calorie-restriction mimetic is reasonable as a description of overlapping effects, but part of its action here is to produce actual calorie restriction. The relative contributions of reduced intake and other drug effects remain unresolved.
-
The calorie-restriction comparison matches food quantity imperfectly and does not match feeding patterns.
Restricted mice ate their allocation quickly and then fasted for a prolonged period. Semaglutide-treated mice ate more gradually. The restriction level was based on the average semaglutide-associated reduction and was not continually adjusted.
These groups therefore differed in fasting duration, hunger and metabolic rhythms. Superior performance with semaglutide supports benefits beyond this particular restriction regimen, but does not isolate a direct cellular mechanism independent of feeding behaviour.
-
Changes in longevity-associated pathways do not establish the mechanism of lifespan extension.
Higher NAD⁺, increased sirtuin expression, lower IGF1 and increased Oser1 are biologically plausible findings. However, none was shown to be necessary for the survival benefit.
There were no experiments blocking these pathways to determine whether semaglutide then lost its effect, nor tissue-specific GLP-1 receptor experiments identifying where the relevant signal originates. The molecular results provide candidate explanations rather than a demonstrated causal chain.
-
Several “hallmarks of ageing” claims rely on indirect measurements.
Lower p16, p21 and SA-β-gal are consistent with reduced senescence-associated changes; they do not demonstrate selective removal of senescent cells. Lower γ-H2AX indicates less DNA-damage signalling, without establishing reduced mutation burden.
Similarly, larger blood-cell colonies do not establish restored long-term stem-cell function; competitive transplantation would be more informative. BrdU and DCX support neurogenesis, but do not prove that the new neurons integrate normally or cause the memory improvement.
Better glucose tolerance is also an expected pharmacological effect of semaglutide. Improvement above baseline does not, by itself, establish reversal of biological ageing.
-
The muscle findings need more careful interpretation than the lean-mass percentages suggest.
Extended Data Fig. 2 shows that absolute gastrocnemius and tibialis anterior muscle weights were lower in treated mice, even though the lean-mass percentage increased.
A larger lean-mass percentage can result from losing proportionally more fat. The functional improvements are encouraging, including after weight adjustment for two tests, but the study does not establish preservation of all muscle tissue. Absolute muscle measurements and direct muscle-force testing would strengthen the translational case.
-
The numerous small experiments warrant caution about individual positive findings.
Many cellular measurements used approximately 3–6 mice per group, and behavioural experiments generally used 10. No formal prospective sample-size calculation was reported.
The authors used multiple-comparison adjustments in several analyses, but these do not comprehensively address the large number of different outcomes examined. RNA sequencing used five animals per group and an adjusted-P threshold of 0.1. Comparisons with external ageing and calorie-restriction datasets also introduce differences in experimental conditions and tissue composition.
These issues matter more for isolated mechanistic findings than for the strongly separated survival curves.
-
Generalisability remains limited.
The study examines one sex, one strain and one dosing regimen in one laboratory. Survival includes both spontaneous deaths and standard humane endpoints; the endpoint categories are not a detailed pathological explanation of why animals lived longer. A formal maximum-lifespan analysis is also absent.
The authors disclose a University of California patent application covering GLP-1 receptor agonists for healthy ageing. Independent replication would be particularly valuable.
The discussion of potential human neuroprotection also needs context. The large evoke and evoke+ trials found that oral semaglutide did not slow clinical progression in early Alzheimer’s disease. Those trials do not settle whether earlier treatment could prevent disease or extend healthy lifespan, but they demonstrate the limits of extrapolating favourable mouse brain findings to clinical benefit. Cummings et al., The Lancet, 2026.
For the mitochondrial–epigenetic interpretation, the paper supplies useful observations but leaves the central mechanism open. It did not measure mitochondrial membrane potential, mtDNA mutation or deletion burden, mitophagy flux, citrate export, nuclear acetyl-CoA, histone acetylation or splicing fidelity. Higher ATP and altered mitochondrial gene expression are compatible with improved metabolism, but do not establish mitochondrial repair as the initiating event. Increased sirtuin expression also cannot determine the net direction of histone acetylation.
The most decisive follow-up would compare semaglutide with controls matched for both food quantity and feeding schedule throughout the remaining lifespan, across both sexes and genetically diverse mice. Combining that experiment with pathway-blocking studies, direct mitochondrial measurements and absolute muscle-function assessments would resolve the most consequential uncertainties.
If helpful, I can flag future studies that independently test this lifespan result.